



F42.2 Diagnosis Code in ICD-10: Definition, Criteria, and Documentation
The International Classification of Diseases, Tenth Revision, Clinical Modification (ICD-10-CM) provides specific alphanumeric designations for documenting psychiatric conditions. Medical coders and healthcare providers rely on this system to translate clinical diagnoses into standardized data for health records and insurance claims. Within this framework, the F42 category identifies patients experiencing obsessive-compulsive disorder.
The specific code F42.2 designates mixed obsessional thoughts and acts. This classification requires documented evidence of both cognitive and behavioral symptoms occurring simultaneously. Clinical research from the National Institute of Mental Health indicates this mixed presentation affects more than 70 percent of individuals diagnosed with the disorder. Accurate application of this code dictates treatment plans, influences pharmacy benefits, and determines insurance coverage for specialized psychiatric care.
The Structure of F42 Classification
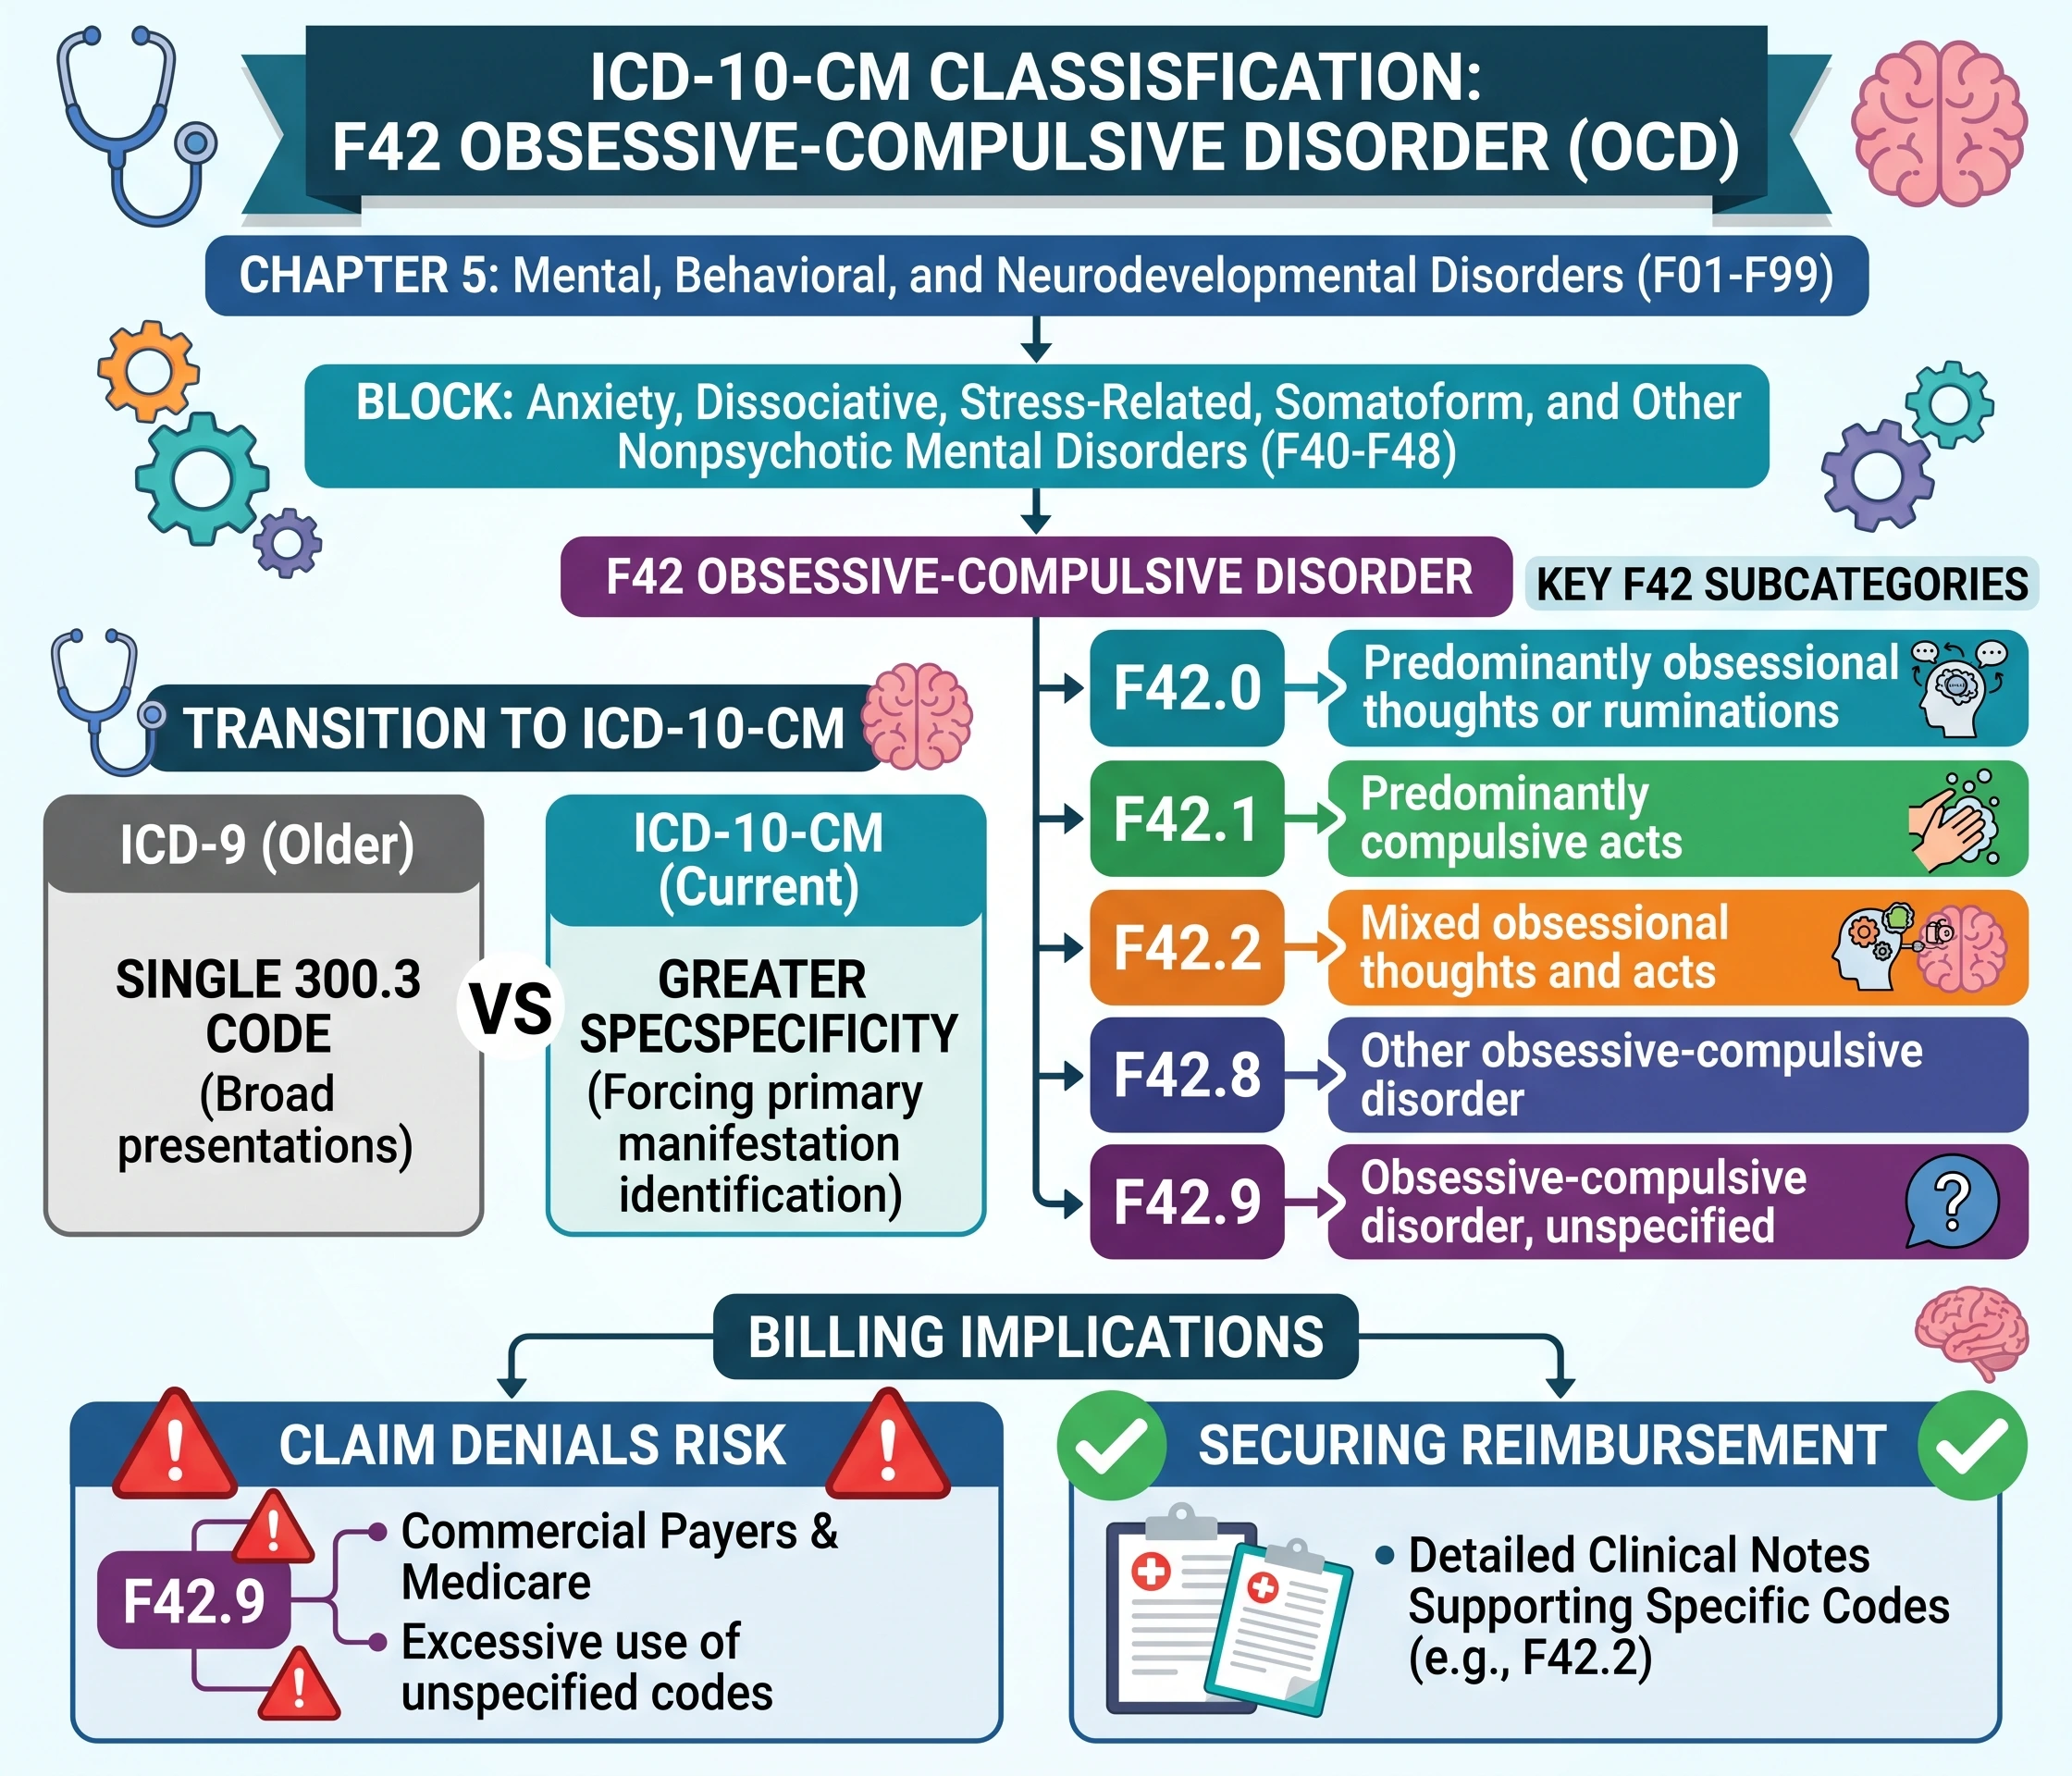
To understand the application of F42.2, medical billers must examine the surrounding diagnostic hierarchy. The F42 family falls under the broader Chapter 5 heading (F01-F99), which covers mental, behavioral, and neurodevelopmental disorders. Specifically, it resides in the F40-F48 block, categorized as anxiety, dissociative, stress-related, somatoform, and other nonpsychotic mental disorders.
The transition from the older ICD-9 system to ICD-10-CM introduced greater specificity for mental health charting. Previously, all presentations were grouped under a single 300.3 code. The current system forces providers to identify the primary manifestation of the illness.
The subcategories include:
- F42.0: Predominantly obsessional thoughts or ruminations.
- F42.1: Predominantly compulsive acts.
- F42.2: Mixed obsessional thoughts and acts.
- F42.8: Other obsessive-compulsive disorder.
- F42.9: Obsessive-compulsive disorder, unspecified.
Coders default to F42.9 when physician notes lack sufficient detail. However, excessive use of unspecified codes frequently triggers claim denials from commercial payers and Medicare. Securing reimbursement requires detailed clinical notes supporting the more specific F42.2 designation.
Clinical Criteria for Obsessional Thoughts
Validating an F42.2 diagnosis requires the explicit charting of obsessional thoughts. These present as recurrent, persistent ideas, urges, or mental images. The patient experiences these internal events as intrusive and unwanted.
These thoughts typically center around specific themes. Common clinical presentations include severe fears of contamination, aggressive impulses toward self or others, intense requirements for symmetry, or persistent unwanted sexual imagery. The patient recognizes these thoughts are products of their own mind, differentiating the condition from psychotic disorders like schizophrenia where patients may believe thoughts are inserted by external forces.
Individuals almost always attempt to ignore, suppress, or neutralize these thoughts. These cognitive intrusions generate acute anxiety. The distress must be severe enough to disrupt normal occupational functioning or social relationships.
Clinical Criteria for Compulsive Acts
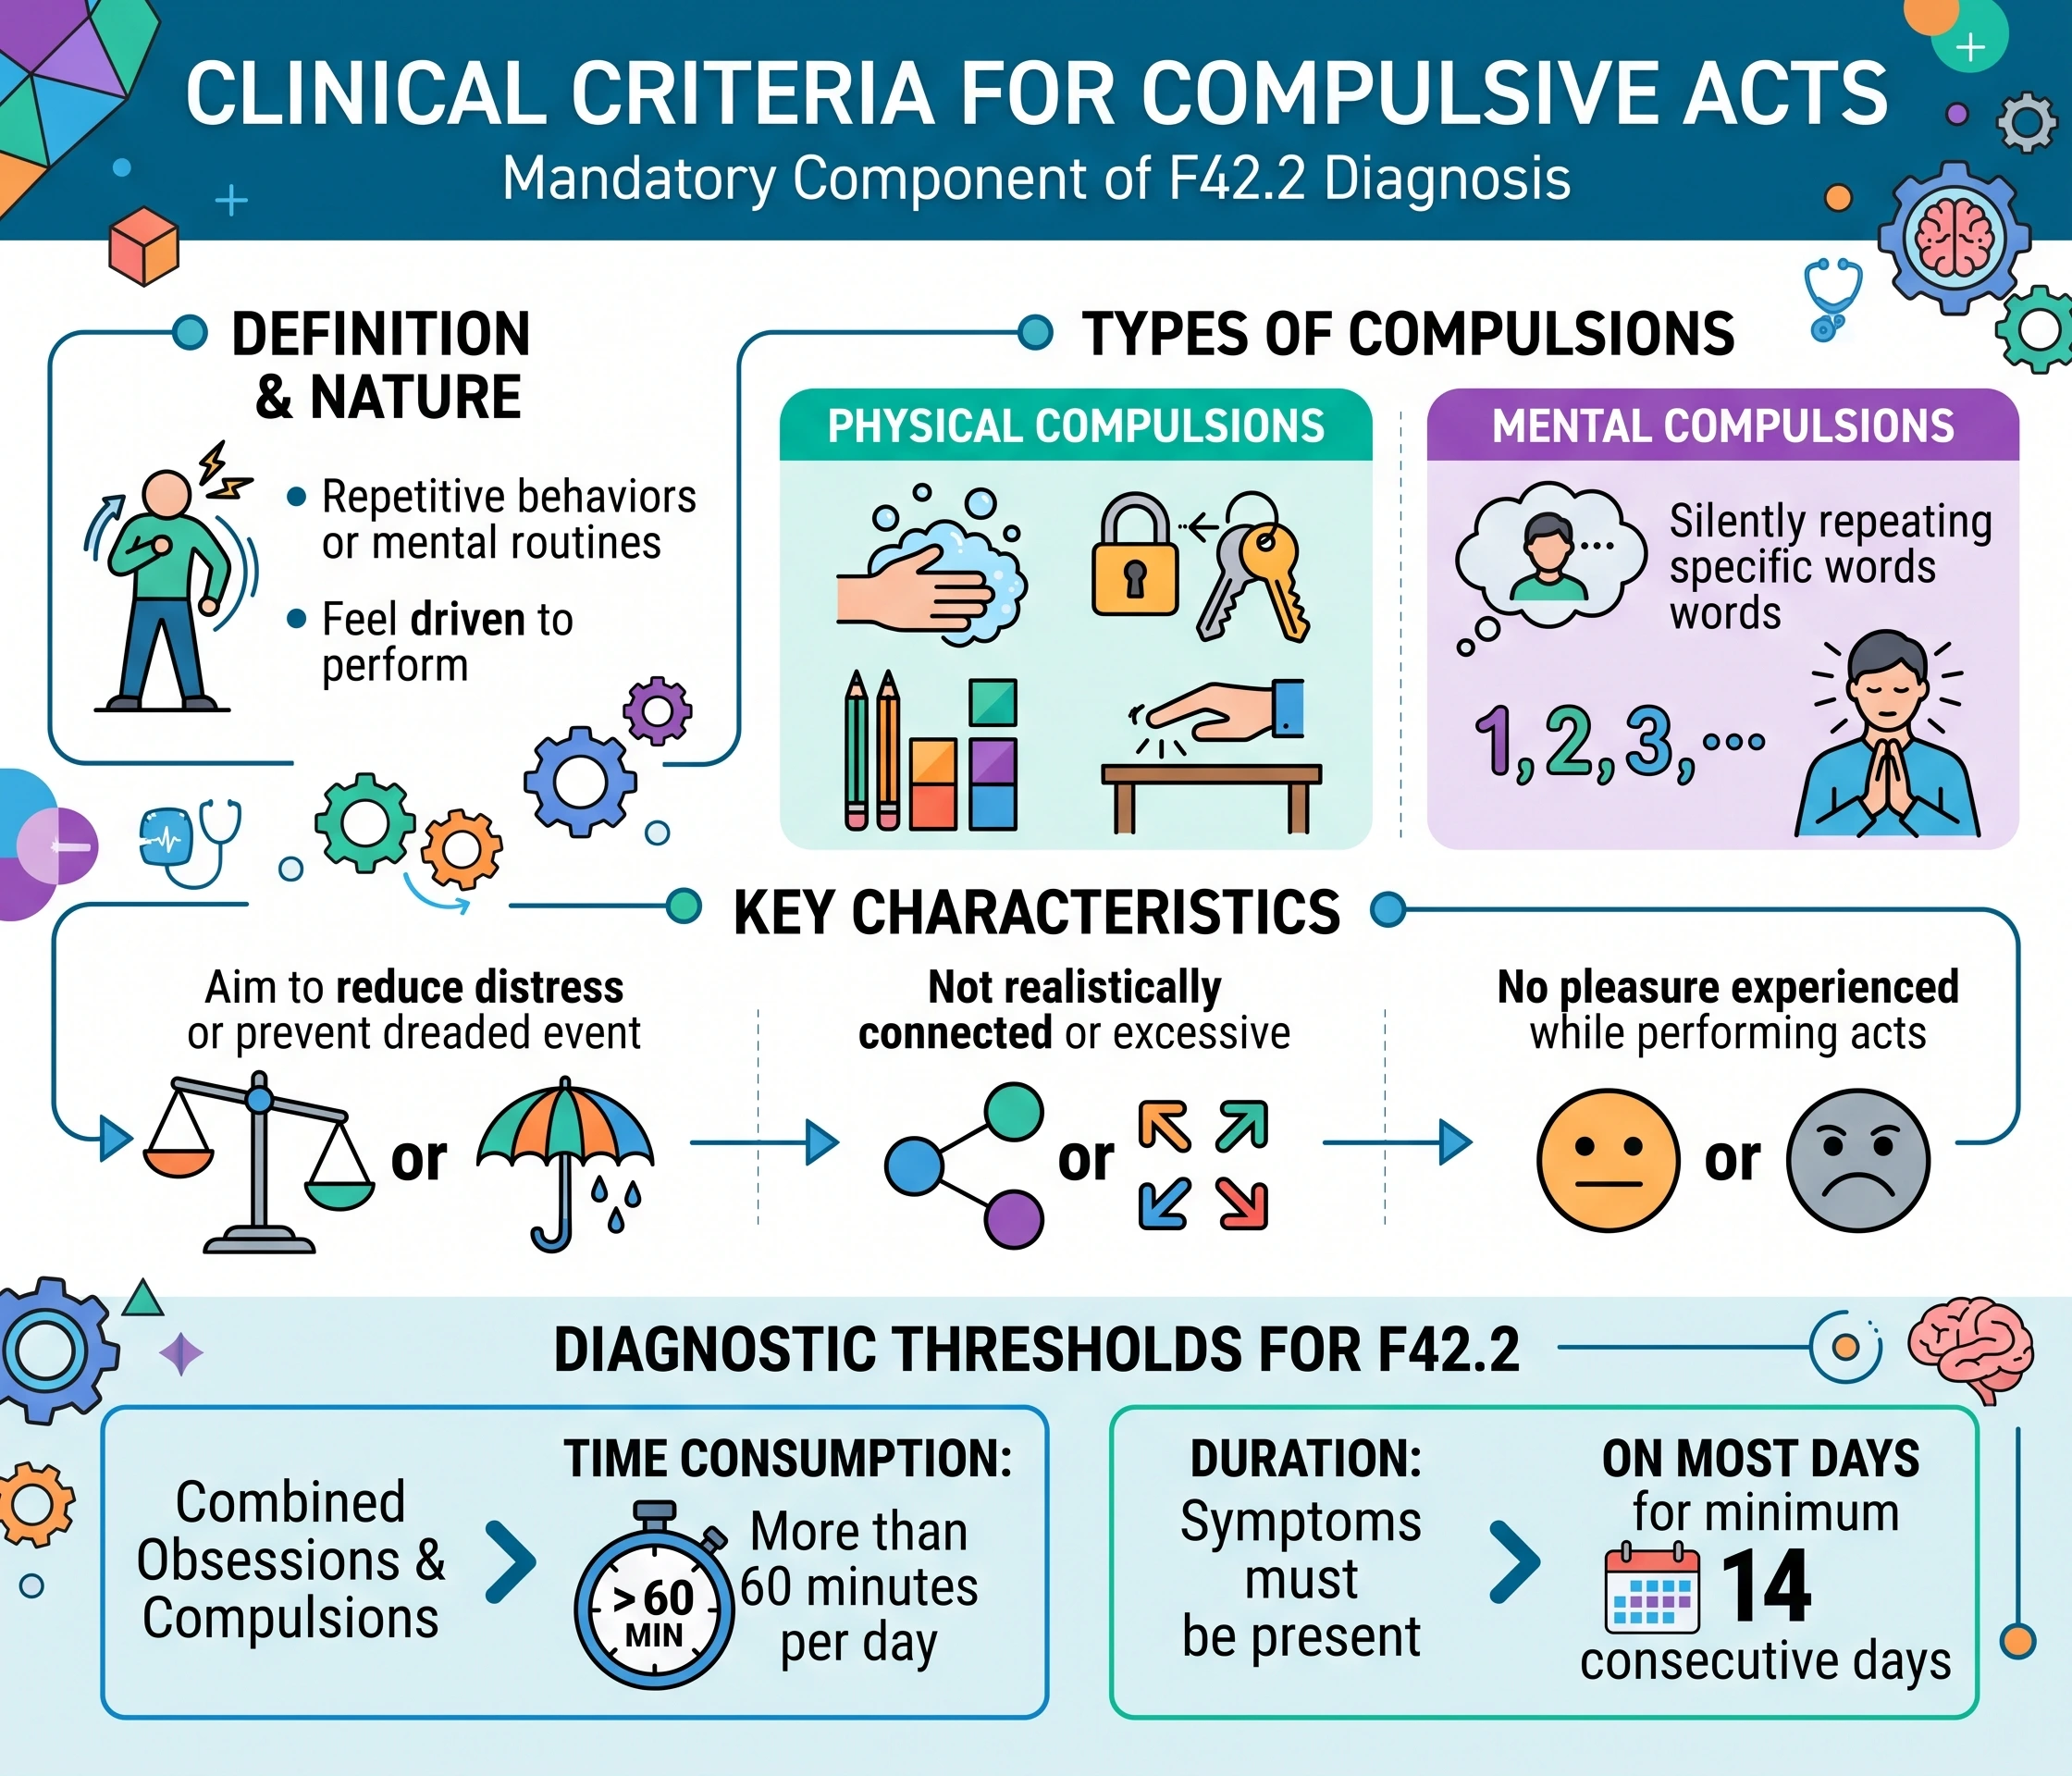
The second mandatory component for an F42.2 diagnosis involves compulsive acts. These are repetitive behaviors or mental routines that the individual feels driven to perform.
Physical compulsions frequently manifest as excessive hand washing, repeatedly checking locks, arranging objects in precise orders, or repetitive tapping. Mental compulsions might involve silently repeating specific words, counting, or praying in a highly structured manner.
Patients perform these rituals in direct response to an obsession or according to rigid self-imposed rules. The actions aim to reduce distress or prevent a dreaded event. However, these behaviors are not connected in a realistic way to the events they are designed to prevent, or they are clearly excessive. The patient does not experience pleasure while performing these acts.
To meet the diagnostic threshold for F42.2, the combined obsessions and compulsions must consume more than 60 minutes of the patient’s day. The symptoms must also be present on most days for a minimum of 14 consecutive days.
Demographic Data and Onset Patterns
Epidemiological studies place the global prevalence of this condition between 1 and 3.5 percent. Symptom onset follows a distinct bimodal distribution based on age and gender.
The initial peak occurs in childhood, typically between the ages of seven and twelve. This early onset predominantly affects young males. Nearly 25 percent of male patients develop clinical symptoms before reaching age ten. A second peak emerges near age 21, which occurs more frequently in females. Adult women receive this diagnosis 1.6 times more often than adult men.
Across all demographic groups, the mean age for the initial presentation of symptoms is 19.5 years. Recognizing these patterns helps providers screen vulnerable populations during routine primary care visits.
Comorbidity and Excludes2 Guidelines
Patients presenting with mixed obsessional thoughts and acts frequently suffer from secondary psychiatric conditions. Medical coders must navigate ICD-10-CM exclusion guidelines to accurately report multiple diagnoses.
The F42 category carries specific Excludes2 notes. In the coding manual, an Excludes2 note indicates that the listed condition is not part of the primary diagnosis, but a patient may exhibit both conditions simultaneously. When clinical documentation supports it, coders can report the primary code and the excluded code on the same claim.
The Excludes2 directives for F42 include:
- Obsessive-compulsive personality disorder (F60.5)
- Obsessive-compulsive symptoms occurring in depression (F32.-, F33.-)
- Obsessive-compulsive symptoms occurring in schizophrenia (F20.-)
Clinical data shows severe major depressive disorder co-occurs with this condition in 53 to 67 percent of cases. Additionally, up to 76 percent of these patients will meet the diagnostic criteria for a secondary anxiety disorder, such as panic disorder or social phobia, during their lifetime. Accurately capturing these comorbid conditions through secondary ICD-10 codes affects the risk adjustment factor for Medicare Advantage patients.
Differentiating from Personality Disorders
Medical billers frequently encounter confusion between F42.2 and F60.5 (Obsessive-compulsive personality disorder). These are distinct clinical entities requiring careful documentation.
F42.2 involves ego-dystonic symptoms. The patient finds the obsessions and compulsions distressing, irrational, and inconsistent with their self-image. They generally want the symptoms to stop.
Conversely, F60.5 represents an ego-syntonic condition. Patients with this personality disorder exhibit a pervasive preoccupation with orderliness, perfectionism, and mental control. They view their rigid behaviors and need for control as logical, correct, and beneficial. They do not experience the intrusive, distressing obsessions characteristic of F42.2. Providers must clearly document the patient’s attitude toward their symptoms to ensure accurate code selection.
Standardized Assessment Instruments
Psychiatric professionals utilize validated measurement scales to confirm the criteria required for this specific diagnosis. Charting the results of these assessments provides coders with concrete data to justify the F42.2 code.
The Yale-Brown Obsessive-Compulsive Scale serves as the primary measurement standard. This 10-item clinician-administered rating scale assesses the severity of both obsessions and compulsions over the previous seven days. It measures time spent, degree of interference, distress levels, resistance, and the patient’s degree of control over the symptoms. A score between 16 and 23 indicates moderate severity, while scores above 24 indicate severe to extreme illness.
Diagnostic interviews, including the Structured Clinical Interview for DSM-5 and the Mini-International Neuropsychiatric Interview, map directly to the criteria needed for F42.2. For pediatric populations, specialists rely on the Child Behavior Checklist-Obsessive Compulsive Subscale to quantify symptom severity before assigning a permanent diagnostic code.
Impact on Therapy Authorization and Billing
Precise application of F42.2 directly impacts treatment approvals from health insurance carriers. The mixed presentation designation validates the medical necessity of intensive, dual-focus treatment protocols.
Exposure and Response Prevention therapy serves as the first-line behavioral intervention. This specialized form of cognitive behavioral therapy requires the patient to confront the triggers that induce obsessional thoughts (exposure) while actively refraining from performing the corresponding physical rituals (response prevention). Insurance utilization reviewers look for the F42.2 code to justify the prolonged, high-frequency therapy sessions required for this treatment model. Using a generic F42.9 code often results in requests for additional clinical information or outright denial of extended therapy benefits.
The code also influences pharmacological management. Patients requiring medication typically receive selective serotonin reuptake inhibitors. The FDA has approved specific medications for this condition, including fluoxetine, fluvoxamine, paroxetine, and sertraline. Clinical guidelines state that patients often require much higher dosages of these medications to achieve symptom reduction compared to the dosages used for major depressive disorder. When pharmacies or insurance plans flag these high dosages for review, the presence of the exact F42.2 code expedites the prior authorization process.
Chart Audits and Documentation Standards
Healthcare organizations face financial risks if clinical documentation does not support the submitted ICD-10-CM codes. During routine chart audits, insurance companies evaluate provider notes to ensure the assigned codes match the clinical narrative.
To protect against recoupments, provider documentation must contain specific elements. Notes must describe the exact nature of the intrusive thoughts. They must outline the specific physical or mental rituals the patient performs. The chart must state how much time these symptoms consume daily. Finally, the provider must document the specific functional impairment caused by the condition.
Consider a poor documentation scenario: “Patient presents with severe anxiety and repetitive behaviors. Diagnosed with OCD. Prescribed sertraline.” A medical coder cannot legally extract F42.2 from this note. They must use the unspecified F42.9 code, which increases the likelihood of claim rejection.
A compliant documentation scenario provides the necessary detail: “Patient reports intrusive, unwanted thoughts regarding bacterial contamination, causing severe anxiety. Patient responds by engaging in ritualistic hand washing, occurring 15 to 20 times daily. These concurrent obsessions and compulsions consume roughly three hours per day and prevent the patient from leaving the house. Diagnosis: Mixed obsessional thoughts and acts.” This narrative explicitly supports the selection of F42.2.
The exactness of the medical record determines the accuracy of the billing cycle. Healthcare providers who understand the specific requirements of the ICD-10-CM manual can prevent administrative delays. Documenting the concurrent nature of both cognitive intrusions and behavioral rituals ensures patients receive authorization for appropriate clinical interventions while maintaining compliance with medical billing standards.