



Understanding the 96130 CPT Code Fee Schedule and Payment Rates (2026)
Medical practices face high levels of financial scrutiny when billing for behavioral health assessments. The American Medical Association (AMA) established CPT code 96130 specifically to compensate clinical providers for the cognitive work of evaluating psychological tests. Because this code reimburses the physician for their analytical time rather than the physical act of handing a diagnostic questionnaire to a patient, insurance companies monitor its application heavily.
Correct reimbursement requires a thorough understanding of exact time thresholds, the 2026 payment scales, and the specific clinical narratives auditors expect to find in patient charts.
Defining the Scope of CPT Code 96130
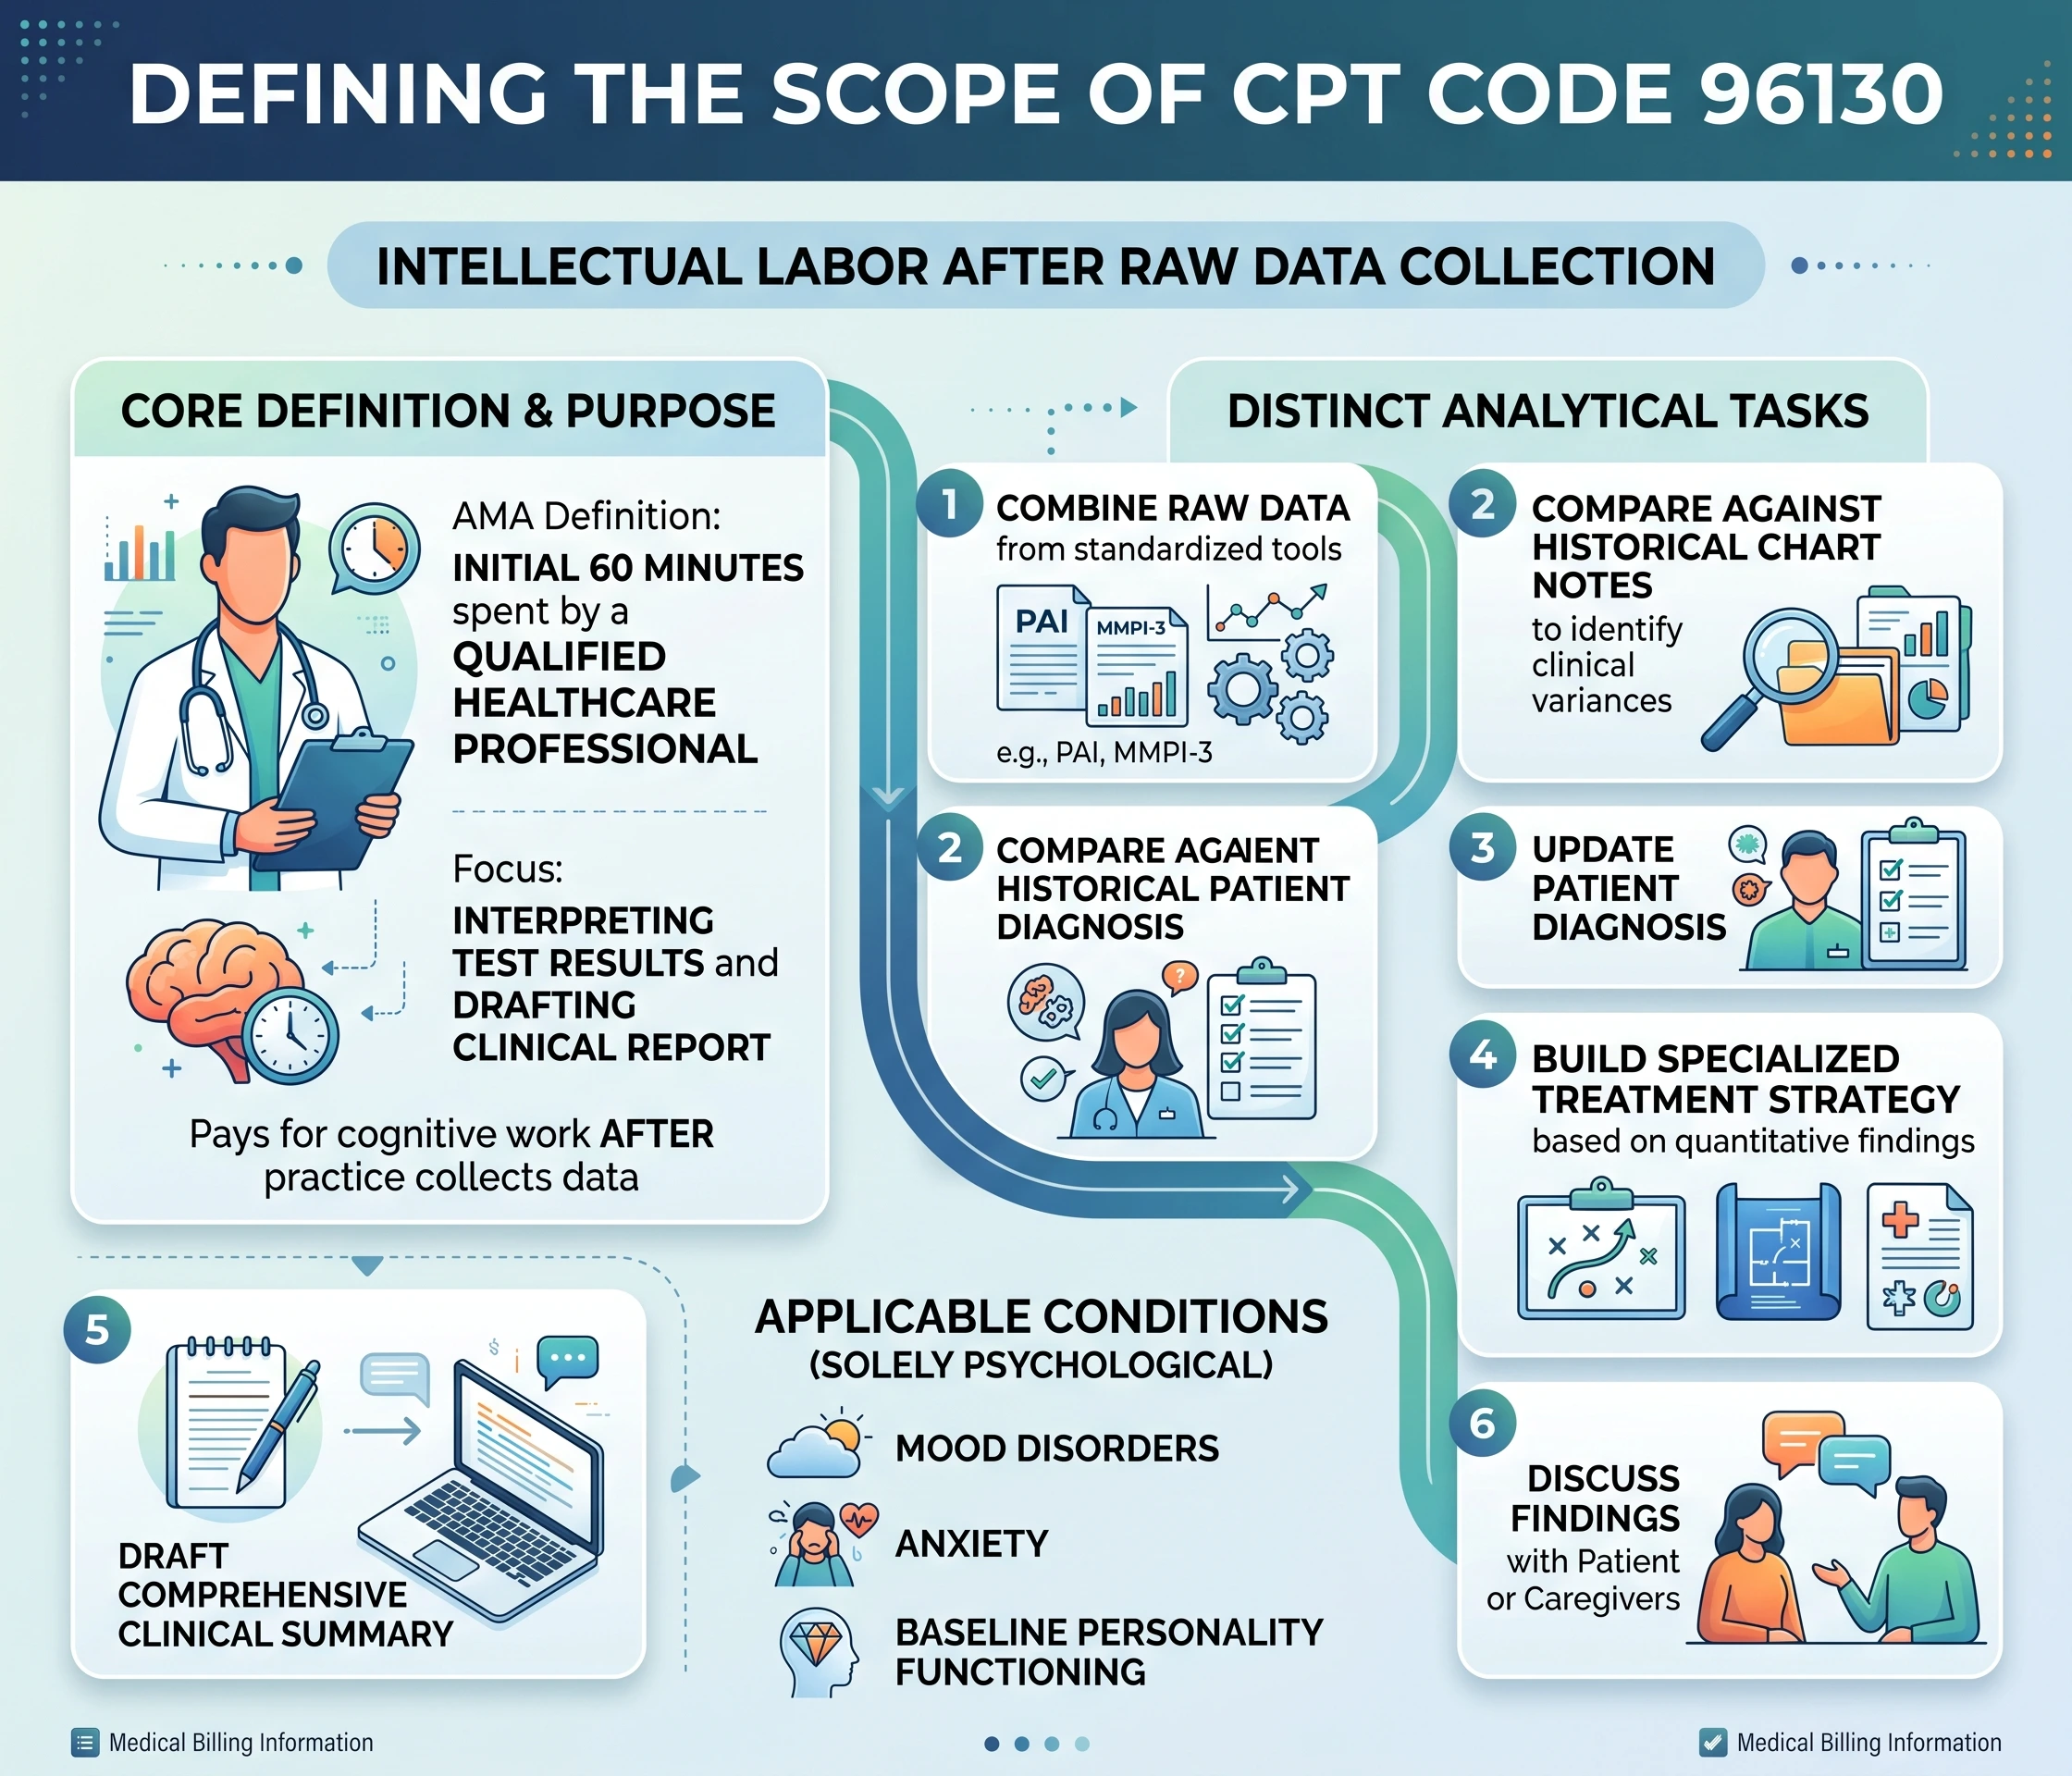
The AMA defines 96130 as the initial 60 minutes a qualified healthcare professional spends interpreting psychological test results and drafting the corresponding clinical report. It pays exclusively for the intellectual labor that occurs after the practice collects the raw testing data.
A clinician billing this code is performing several distinct analytical tasks. They combine raw data from standardized psychiatric tools, such as the Personality Assessment Inventory (PAI) or the Minnesota Multiphasic Personality Inventory (MMPI-3). They compare the new testing data against historical chart notes to identify clinical variances. Following this analysis, the provider updates the patient’s diagnosis and builds a specialized treatment strategy based on the quantitative findings. Finally, the clinician drafts a comprehensive clinical summary and discusses the findings directly with the patient or their assigned caregivers.
This code applies solely to psychological conditions, including mood disorders, anxiety, and baseline personality functioning.
Separating Evaluation from Administration and Scoring
A primary reason health plans deny 96130 claims is the conflation of test administration with test evaluation. Code 96130 does not pay a practice to administer a test.
If a physician or a clinical technician simply gives a patient a test to fill out and scores the results, the practice must bill the administration codes. CPT 96136 designates the first 30 minutes of test administration and scoring performed by a physician or qualified healthcare professional. CPT 96138 designates the first 30 minutes of administration performed by a clinical technician.
Furthermore, automated testing carries its own designation. If a patient completes a computerized assessment that generates an automated results report without requiring independent human analysis, the practice must bill CPT 96146. A provider cannot bill 96130 simply for reading a computer-generated testing summary. The medical record must prove the physician applied independent clinical judgment to the data.
The 2026 Medicare Physician Fee Schedule and RVU Calculation

The Resource-Based Relative Value Scale (RBRVS) dictates how much Medicare pays for specific medical services across the United States. The Centers for Medicare & Medicaid Services (CMS) assigns Relative Value Units (RVUs) to measure the clinical effort, office overhead, and liability risk tied to every procedure code.
For 2026, the non-facility RVU breakdown for 96130 heavily weighs the provider’s cognitive effort.
2026 RVU Components for CPT 96130 (Non-Facility Setting)
RVU Component | Assigned Value | Function |
Provider Work RVU | 2.20 | Compensates the clinician’s direct analytical effort. |
Practice Expense RVU | 1.60 | Covers administrative overhead and office space. |
Malpractice RVU | 0.09 | Accounts for the liability risk of the evaluation. |
Total Non-Facility RVU | 3.89 | The combined value for an office-based procedure. |
To calculate the final payment, billers multiply the total RVU by the annual CMS conversion factor. Applying the published 2026 CMS conversion factor (approximately $32.07), the national unadjusted Medicare payment rate sits at $124.75 for the first hour of psychological testing evaluation.
Comparing Medicare Baselines with Commercial Payer Rates
Private health insurance networks generally reimburse at higher thresholds than traditional Medicare. Contract data published for major commercial insurers in 2026 indicates a median allowable payment of $147.00 for the primary evaluation hour.
Highly localized regional networks and specialized behavioral health carve-out plans often negotiate rates reaching up to $178.00 per unit. Conversely, Medicaid managed care organizations vary strictly by state legislation. Medicaid plans typically reimburse providers at 60 to 80 percent of the standard Medicare baseline rate. Medical billers must verify exact contracted rates with each payer annually, as fee schedules often adjust at the start of the calendar year.
Navigating Time-Based Billing Rules and the Midpoint Threshold
Because 96130 relies on specific time intervals, it follows standard AMA time-based billing regulations. A provider must cross the halfway mark of the stated hour to claim the primary code. A clinician needs at least 31 documented minutes of qualifying analytical work to justify the claim.
This time does not have to occur face-to-face with the patient. The 31-minute threshold applies to the entire professional evaluation process. Time spent analyzing scoring sheets in a private office, calling another treating physician to verify medical history, and drafting the final written report all add to the total allowable time.
If the entire evaluation process takes 30 minutes or less, the provider cannot legally bill 96130. They must transition to a standard Evaluation and Management (E/M) code or a brief emotional assessment code (such as 96127) that matches the shorter duration.
Practices also frequently conduct evaluations across multiple days. A psychologist might review records for 20 minutes on a Tuesday, interpret the data for 30 minutes on a Wednesday, and write the report for 20 minutes on a Thursday. According to CMS billing guidelines, the practice aggregates the total time (70 minutes) and submits the claim using the date the evaluation was completed and the final report was signed.
Documenting Extended Clinical Time with CPT 96131
Complex psychological assessments rarely conclude within a single hour. When the clinical analysis requires time beyond the primary hour, medical coders use CPT 96131 to report the extra labor.
Code 96131 covers each additional hour of psychological testing evaluation. It functions exclusively as an add-on code. Insurance clearinghouses and payer algorithms automatically reject any claim that lists 96131 without 96130 attached to the primary service line.
Time Accounting for Psychological Testing Evaluation
Total Documented Time | Required CPT Code Application |
1 to 30 minutes | Bill an appropriate E/M code instead. |
31 to 90 minutes | Bill one unit of 96130. |
91 to 150 minutes | Bill one unit of 96130 plus one unit of 96131. |
151 to 210 minutes | Bill one unit of 96130 plus two units of 96131. |
Clinicians must complete the entire initial 60 minutes of the first hour before they can start assigning time to the 96131 add-on code. Billing an add-on code prematurely is a common trigger for post-payment audits.
Provider Eligibility and the Incident-To Regulations
The AMA limits the use of 96130 to physicians and qualified healthcare professionals. Eligible providers typically include psychiatrists (Medical Doctors and Doctors of Osteopathic Medicine) and licensed clinical psychologists (PhDs and PsyDs). Most major insurance networks also permit advanced practice nurses, specifically Psychiatric-Mental Health Nurse Practitioners, to bill the code independently.
Master’s-level therapists face strict regulatory barriers regarding evaluation codes. CMS guidelines outlined in the Medicare Benefit Policy Manual generally prevent licensed professional counselors and licensed clinical social workers from billing 96130 independently.
While some private commercial insurers make specific exceptions based on state scope-of-practice laws, master’s-level clinicians treating Medicare patients typically must bill “incident-to” a supervising physician. Incident-to billing requires a doctoral-level provider to establish the initial treatment plan, remain actively involved in the patient’s care, and provide direct in-office supervision while the therapist performs the evaluation tasks.
Differentiating Psychological from Neuropsychological Codes
Insurance auditors frequently penalize medical practices for substituting psychological billing codes for neuropsychological assessments.
Code 96130 exists strictly for psychological evaluations. If a physician evaluates a patient for central nervous system damage, such as a traumatic brain injury, stroke-related cognitive deficits, or Alzheimer’s disease, they must bill CPT 96132 (Neuropsychological testing evaluation services). Billing a psychological code for an organic neurological disorder violates coding standards and often guarantees a recoupment demand upon audit.
Overcoming NCCI Edits When Billing Same-Day E/M Services
Psychiatrists often conduct a standard office visit on the exact same day they evaluate psychological testing data. The National Correct Coding Initiative (NCCI) flags this specific combination.
Medicare claims processing algorithms automatically bundle 96130 into standard office visits (codes 99202 through 99215). The software assumes the physician’s analytical time is already compensated by the medical decision-making component of the E/M payment.
Practices must prove the testing evaluation was a distinct, separate procedure to secure reimbursement for both services. Medical coders achieve this using specific modifiers.
First, they append Modifier 25 to the primary office visit code (for example, 99214-25). This indicates a significant, separately identifiable evaluation and management service. Second, they append Modifier 59 to code 96130 to mark the testing evaluation as a distinct procedural service.
Certain regional Medicare Administrative Contractors (MACs), such as Novitas Solutions or First Coast Service Options, may require specific X Modifiers (XE, XS, XP, or XU) instead of Modifier 59 to provide exact details regarding why the service was distinct. Assigning different ICD-10 diagnosis codes to each line further prevents automated denials. A clinician might attach a generalized anxiety disorder diagnosis to the E/M code while linking the testing evaluation code to a separate suspected behavioral condition.
Formulating Audit-Proof Medical Records
When health plans request records to audit a 96130 claim, they look for specific documentation standards established by the American Psychological Association. A printed list of raw test scores will fail an audit. The patient’s chart must contain a custom, formally drafted clinical summary.
A compliant medical note must include an exact declaration of the time spent. The provider should write a specific statement, such as “Total professional time spent integrating data, interpreting results, and writing this report equaled 55 minutes.”
The chart must also state the exact clinical rationale for the testing, replacing generic symptoms with specific medical requirements. The provider must write a narrative paragraph detailing how the new testing scores interact with the patient’s known medical history. Finally, the report requires a section outlining concrete adjustments to the patient’s care plan, such as a change in medication dosage or a shift in the formal diagnosis.
Addressing Medical Necessity Denials and Prior Authorization
Medicare Advantage networks and commercial health maintenance organizations (HMOs) actively enforce prior authorization requirements for testing evaluations.
The most common claim rejection for 96130 is a lack of medical necessity. Payers frequently deny claims if they suspect the testing was administered for routine academic placement, court-ordered legal requirements, or school-based educational accommodations rather than a specific medical intervention.
To overturn a medical necessity denial, billing departments must submit the initial clinical intake notes alongside the final testing report. These preliminary notes must prove the provider required the testing data to resolve a diagnostic ambiguity that was actively preventing safe and effective medical treatment.
Accurate reimbursement for CPT 96130 requires precise time tracking, exact add-on code sequencing, and highly specific clinical narratives. By aligning internal chart documentation with the strict time rules published by the AMA and the medical necessity criteria enforced by regional payers, medical practices can effectively capture revenue for the specialized time they spend evaluating psychological data.