



Accurate medical coding ensures appropriate patient care and predictable reimbursement cycles. Healthcare providers use the F10.20 ICD-10 code to classify alcohol dependence, uncomplicated. This specific alphanumeric string belongs to Chapter 5 of the International Classification of Diseases, Tenth Revision, Clinical Modification (ICD-10-CM), which covers mental, behavioral, and neurodevelopmental disorders.
The World Health Organization (WHO) originally published the base ICD-10 system in 1992. The United States developed the Clinical Modification (CM) to add diagnostic detail for billing purposes, officially adopting the system on October 1, 2015. The transition required greater clinical specificity from physicians. Under the current framework, assigning this diagnosis requires documented evidence of a patient's physiological reliance on alcohol.
The structure of the classification provides immediate clinical context. The letter F dictates a psychiatric or behavioral condition. The number 10 isolates the substance involved as alcohol. The decimal extension .20 specifies dependence without current physiological complications. Medical billers transmit this exact sequence to commercial health insurance payers, Medicare, and Medicaid. It communicates the exact nature of the patient's physiological state without requiring payers to review the full clinical narrative.
Clinical criteria and DSM-5 mapping

The American Psychiatric Association published the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) in 2013. The publication merged the historically separate diagnoses of alcohol abuse and alcohol dependence. The DSM-5 now evaluates Alcohol Use Disorder (AUD) on a single continuum of mild, moderate, or severe. However, the ICD-10-CM system still requires coders to distinguish between abuse and dependence.
To bridge this diagnostic gap, the Centers for Medicare and Medicaid Services (CMS) maintains crosswalk guidelines. According to these clinical mapping standards, a DSM-5 diagnosis of moderate or severe AUD corresponds directly to alcohol dependence in the ICD-10-CM manual. Mild AUD maps to alcohol abuse.
A physician utilizing the DSM-5 criteria must document at least four distinct symptoms of AUD within a 12-month period to justify the moderate or severe classification necessary for the F10.20 ICD-10 code.
Diagnostic symptoms of alcohol dependence
Physicians often utilize standardized screening tools, such as the Alcohol Use Disorders Identification Test (AUDIT), to quantify patient symptoms. To support a dependence diagnosis, the medical record must demonstrate an established pattern of impaired control. Patients exhibit a strong desire or urge to consume alcohol. They frequently report unsuccessful attempts to cut down or regulate their drinking habits.
Physiological tolerance serves as a primary diagnostic indicator. Tolerance occurs when a patient requires markedly increased amounts of alcohol to achieve intoxication or the desired effect. The clinical record may also reflect a diminished physical response when the patient consumes their usual amount of alcohol.
Social and occupational impairments provide further clinical evidence. Patients diagnosed with this condition routinely spend a significant amount of time obtaining alcohol, drinking, or recovering from its effects. They often abandon occupational, social, or recreational activities in favor of alcohol consumption. Despite knowing they have a persistent physical or psychological problem exacerbated by drinking, they continue to consume alcohol. The treating physician must detail these behavioral patterns in the assessment and plan portion of the clinical note.
The medical definition of uncomplicated
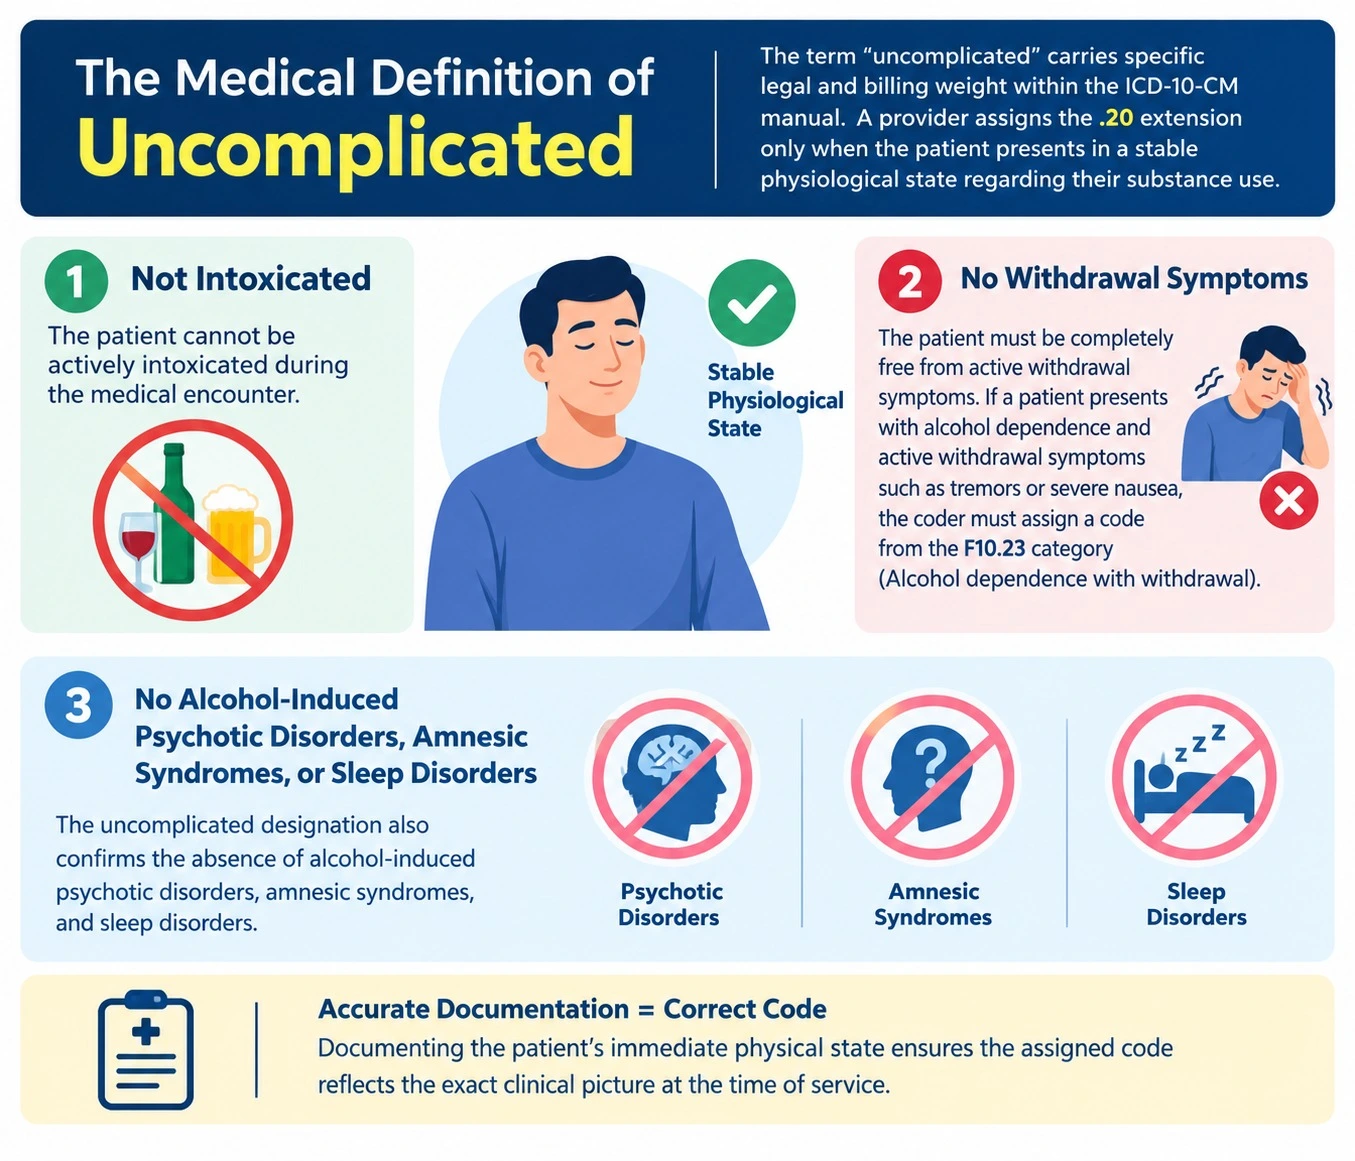
The term "uncomplicated" carries specific legal and billing weight within the ICD-10-CM manual. A provider assigns the .20 extension only when the patient presents in a stable physiological state regarding their substance use. The patient cannot be actively intoxicated during the medical encounter.
Furthermore, the patient must be completely free from active withdrawal symptoms. If a patient presents with alcohol dependence and active withdrawal symptoms such as tremors or severe nausea, the coder must assign a code from the F10.23 category (Alcohol dependence with withdrawal).
The uncomplicated designation also confirms the absence of alcohol-induced psychotic disorders, amnesic syndromes, and sleep disorders. Documenting the patient's immediate physical state ensures the assigned code reflects the exact clinical picture at the time of service.
Medical billing guidelines for the F10.20 ICD-10 code
Medical coders navigate strict hierarchy rules published annually in the ICD-10-CM Official Guidelines for Coding and Reporting. Section I.C.5.b of the official guidelines details the hierarchy for substance use, abuse, and dependence. When a provider's documentation mentions both alcohol use and alcohol abuse, the coder reports only the code for abuse.
When the provider documents both alcohol abuse and alcohol dependence, the coder reports only the code for dependence. A clinical note listing a history of heavy alcohol use, current alcohol abuse, and established alcohol dependence requires a single F10.20 code. This hierarchy prevents redundant billing and establishes the highest severity level of the patient's condition.
Understanding Excludes1 and Excludes2 notes
Medical billers must strictly adhere to the instructional notes within the ICD-10-CM tabular list to prevent immediate claim denials. The F10 category includes specific Excludes instructions. An Excludes1 note dictates that a coder cannot bill two mutually exclusive conditions together.
The F10.20 ICD-10 code carries a strict Excludes1 note for F10.10 (Alcohol abuse, uncomplicated). Reporting uncomplicated alcohol abuse alongside uncomplicated dependence on the same claim will trigger an automatic denial from the clearinghouse or payer. A patient cannot medically have both abuse and dependence as separate, codable conditions during the same encounter.
An Excludes2 note functions differently. It indicates that a separate condition is not included in the primary code, but a patient may possess both conditions simultaneously. If a patient has alcohol dependence and a secondary physical condition caused by alcohol, such as alcoholic gastritis (K29.20), the coder reports both codes. The sequencing of these codes on the CMS-1500 claim form depends entirely on the primary reason for the patient's visit. If the patient presents primarily for stomach pain, the gastritis code sequences first.
Required clinical documentation for compliance
Payer audits frequently target behavioral health claims for insufficient medical documentation. To support this specific diagnosis, the attending physician or qualified healthcare professional must write the exact word "dependence" in the formal medical record. Medical coders are strictly prohibited from assuming a dependence diagnosis based on external factors.
For example, a coder cannot assign this code simply because a laboratory test reveals an elevated Blood Alcohol Concentration (BAC) or high liver enzymes. Similarly, the presence of a prescription for Food and Drug Administration (FDA) approved addiction medications, such as naltrexone or acamprosate, does not automatically justify a dependence code. The provider's narrative must explicitly connect the patient's clinical presentation to physiological dependence.
If the documentation states "chronic alcohol use" or "heavy drinking" without specifying dependence, the coder must default to F10.90 (Alcohol use, unspecified, uncomplicated). Defaulting to an unspecified code frequently results in lower reimbursement rates or requests for additional medical records from the insurance company. Specificity in the physician's documentation guarantees coding accuracy and secures proper reimbursement.
Impact on treatment planning and medical necessity
The presence of the F10.20 ICD-10 code directly impacts financial coverage for ongoing addiction treatment. Health insurance providers, including commercial plans and government programs, require a precise primary diagnosis code to establish medical necessity for specialized services. This specific code justifies billing for outpatient behavioral counseling, group therapy sessions, and psychiatric evaluations.
Providers often use the American Society of Addiction Medicine (ASAM) criteria in conjunction with the F10.20 code to determine the appropriate level of care. ASAM dimensions evaluate withdrawal potential, biomedical conditions, and the patient's recovery environment. Matching the F10.20 diagnosis with the correct ASAM level ensures insurance authorization for residential or outpatient facilities.
For intensive outpatient programs (IOP) or partial hospitalization programs (PHP), a dependence diagnosis verifies that the patient requires a structured, multi-day treatment approach. Claims submitted with only an unspecified "use" code face higher scrutiny or outright denial for these higher levels of care. Health plans recognize through actuarial data that physiological dependence requires extended, structured medical intervention compared to episodic use.
Accurate application of this diagnostic code allows public health organizations to track addiction prevalence accurately. The Centers for Disease Control and Prevention (CDC) utilizes aggregated ICD-10-CM data from hospital discharges and outpatient claims to monitor substance use disorder trends across different demographics. Precise coding at the individual provider level directly feeds into these national epidemiological statistics.
Medical facilities rely on the exact application of the F10.20 ICD-10 code to allocate healthcare resources and facilitate accurate provider reimbursement. Clinical documentation must verify the patient's physiological reliance on alcohol and confirm the complete absence of acute intoxication or withdrawal during the specific encounter. By adhering to the official hierarchy rules and tabular list instructions published by the Centers for Medicare and Medicaid Services, coding professionals ensure claims pass payer edits without delay. Clear, specific communication between the diagnosing physician and the medical billing staff remains the primary mechanism for maintaining regulatory compliance and securing funding for necessary addiction treatment programs.