



The ICD-10-CM code F43.0 designates an acute stress reaction. Medical coders and healthcare providers frequently encounter this diagnosis in emergency departments, primary care clinics, and outpatient psychiatric facilities. Accurate application of this code requires strict adherence to specific timeframes and clinical thresholds.
Billing for mental health conditions requires more than matching a symptom to a code. Health insurance payers deny claims when clinical documentation fails to support the specific definitions outlined in both the ICD-10-CM manual and the psychiatric diagnostic guidelines. F43.0 operates under a strict chronological window, and medical records must explicitly prove that the patient falls within that specific timeframe.
Diagnostic criteria established by the DSM-5-TR
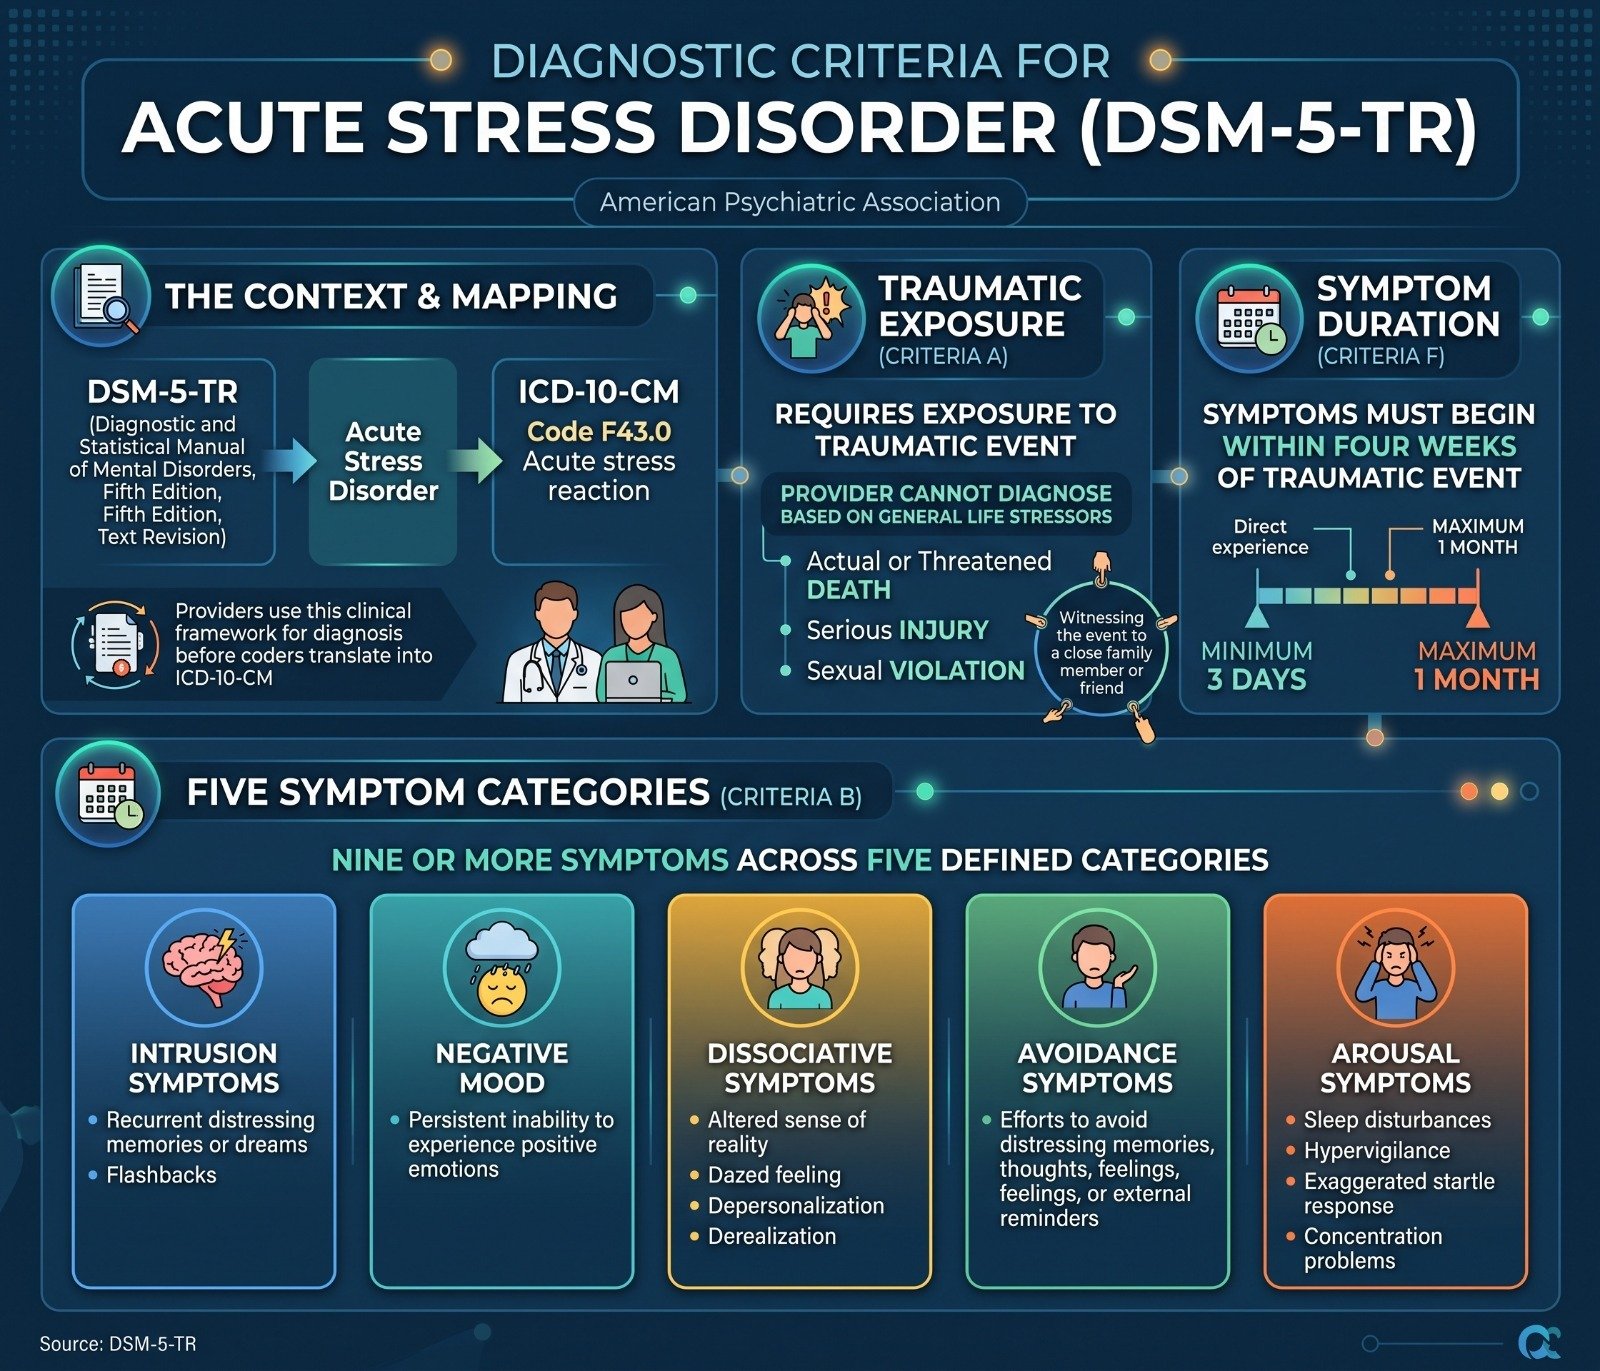
The American Psychiatric Association publishes the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR). This manual provides the clinical framework that providers use to diagnose mental health conditions before coders translate those diagnoses into ICD-10-CM codes. The DSM-5-TR classifies this condition as Acute Stress Disorder. The ICD-10-CM index maps this diagnosis directly to F43.0 Acute stress reaction.
A provider cannot diagnose an acute stress reaction based on general life stressors. The manual states the patient must experience exposure to actual or threatened death, serious injury, or sexual violation. The exposure can occur through direct experience, witnessing the event in person, learning that the event occurred to a close family member, or experiencing repeated exposure to aversive details of a traumatic event.
Symptom duration separates an acute stress reaction from other psychiatric conditions. The DSM-5-TR requires the symptoms to begin within four weeks of the traumatic event. The condition must last for a minimum of three days and a maximum of one month.
Within Four Weeks
The symptoms must begin within four weeks of the traumatic event.
Three Days to One Month
The condition must last for a minimum of three days and a maximum of one month.
Patients must exhibit nine or more symptoms from any of five defined categories. These categories include intrusion symptoms (recurrent distressing memories or dreams), negative mood, dissociative symptoms (altered sense of reality), avoidance symptoms (efforts to avoid external reminders), and arousal symptoms (sleep disturbances or hypervigilance).
Translating clinical notes into F43.0
Medical billers and coders rely entirely on the provider's written documentation. If a provider writes "severe anxiety following a car accident," a coder cannot legally report F43.0. The documentation must establish the severity of the trauma, the exact date the trauma occurred, and the date the symptoms began.
Insurance auditors look for specific data points in the clinical note. The subjective portion of the documentation must state the date of the triggering event. A note stating that a patient witnessed a violent crime on October 1 supports the use of F43.0 for visits occurring between October 4 and October 31.
Payers frequently reject claims when the medical record lacks this chronological data. A provider must write a clear history of present illness (HPI) that connects the current symptoms directly to the documented trauma. Coders must query the provider if the timeline remains ambiguous.
Trauma Date
The documentation must establish the exact date the traumatic event occurred.
Symptom Onset
The record must document when the psychiatric symptoms began.
Trauma Severity
The documentation must establish the severity and qualifying nature of the trauma.
HPI Connection
The HPI must connect the patient's current symptoms directly to the documented trauma.
Comparing F43.0 to similar psychiatric codes
Providers often confuse acute stress reaction with adjustment disorders or post-traumatic stress disorder (PTSD). Each condition carries distinct coding rules based on the nature of the stressor and the duration of the symptoms.
| ICD-10-CM Code | Condition Name | Stressor Type | Timeframe Requirement |
|---|---|---|---|
| F43.0 | Acute stress reaction | Life-threatening trauma | 3 days to 1 month post-trauma |
| F43.10 | Post-traumatic stress disorder, unspecified | Life-threatening trauma | Symptoms persisting beyond 1 month |
| F43.20 | Adjustment disorder, unspecified | Non-life-threatening stressor | Symptoms occurring within 3 months of stressor |
An adjustment disorder (F43.20) occurs following events such as a divorce, job loss, or a geographic move. While these events cause significant distress, they do not meet the DSM-5-TR criteria for life-threatening trauma required for F43.0 or F43.10.
Coders must monitor patient problem lists for expired codes. If a patient returns for follow-up care six weeks after the traumatic event and continues to experience symptoms, the provider must update the diagnosis. The coder must transition the claim from F43.0 to the appropriate PTSD code (F43.1-). Keeping F43.0 on a claim beyond the one-month limit results in a direct violation of coding guidelines.
Selecting evaluation and management (E/M) codes
Providers typically bill outpatient visits for acute stress reaction using standard Evaluation and Management (E/M) codes (99202-99215) or psychiatric diagnostic evaluation codes (90791, 90792). The American Medical Association (AMA) updated CPT coding guidelines for outpatient E/M visits in 2021, shifting the requirement away from history and physical exam elements. Providers now select E/M levels based on either total time spent on the date of encounter or the level of medical decision making (MDM).
99202–99215
Standard outpatient Evaluation and Management (E/M) codes.
90791
Psychiatric diagnostic evaluation.
90792
Psychiatric diagnostic evaluation with medical services.
When coding based on time, the provider must document the exact number of minutes spent engaged in patient care activities on that calendar date. This includes face-to-face time, chart review, and care coordination. A 45-minute visit for a new patient experiencing an acute stress reaction maps to CPT code 99204.
When coding based on MDM, acute stress reaction typically qualifies as an acute, uncomplicated illness or injury (low complexity) or an acute illness with systemic symptoms (moderate complexity), depending on the severity of the psychiatric presentation.
Prescription management heavily influences the MDM calculation. According to the AMA MDM table, prescription drug management qualifies as a moderate risk of morbidity. If a physician evaluates a patient for F43.0 and prescribes a short-acting sleep medication to manage the arousal symptoms, the risk category elevates to moderate. This often supports billing a 99214 for an established patient, provided the number and complexity of problems addressed also meet the necessary thresholds.
Psychotherapy add-on codes
Behavioral health specialists often provide psychotherapy during the same visit as the medical evaluation. Coders use add-on CPT codes (90833, 90836, 90838) to capture this additional work.
To use a psychotherapy add-on code with an E/M service, the provider must separate the documentation. The note must clearly delineate the time spent on medical management from the time spent on psychotherapy. The provider cannot use the same minutes to justify both the E/M code (if billing by time) and the psychotherapy code.
"Spent 15 minutes performing medical evaluation and medication management. Spent an additional 30 minutes providing cognitive behavioral therapy focusing on trauma processing and grounding techniques." The coder would then bill the appropriate E/M code based on MDM, alongside CPT code 90833 (Psychotherapy, 30 minutes with patient).
Audit risks associated with behavioral health coding
The Department of Health and Human Services Office of Inspector General (OIG) monitors Medicare and Medicaid claims for billing anomalies. Behavioral health services frequently appear on the OIG Work Plan due to historically high improper payment rates.
Medicare Administrative Contractors (MACs) use automated system edits to flag illogical coding combinations. Claims featuring F43.0 are highly susceptible to these automated reviews. If an audit reveals that a practice continuously bills F43.0 for patients over periods extending for several months, the MAC will initiate recoupment processes. The payer will demand the return of funds paid for those non-compliant claims.
Monitor the Diagnosis Timeline
Auditors also look for the "copy and paste" function in electronic health records (EHR). Providers sometimes copy a previous note and bring F43.0 forward into the new encounter without updating the HPI. This creates a contradictory medical record where the date of service falls outside the allowable one-month window of the original trauma, but the diagnosis code remains unchanged.
Required documentation elements for claim compliance
Medical coders cannot assume information that does not appear in the record. Providers can protect their claims by adopting a standardized documentation template for trauma-related visits.
A complete clinical note for an acute stress reaction must explicitly list:
The exact date of the traumatic event.
The specific nature of the event (verifying it meets the life-threatening threshold).
The date the psychiatric symptoms began.
A list of the specific symptoms matching the DSM-5-TR categories.
A statement regarding the impairment of the patient's occupational or social functioning.
The specific therapeutic interventions or medications provided during the encounter.
F43.0 Acute Stress Reaction: Key Takeaway
F43.0 serves a very specific clinical and administrative purpose. It captures the immediate, intense psychiatric fallout following a severe trauma. Medical billers, coders, and providers must work together to ensure the clinical documentation matches the strict chronological limits of the diagnosis. Accurate coding prevents claim denials, protects the practice during regulatory audits, and ensures the patient's medical history accurately reflects their clinical journey from acute reaction to recovery or long-term management.