



F14.20 Diagnosis Code: Symptoms, Documentation, and Billing Guidelines
Accurate behavioral health coding can mean the difference between a clean claim and a months-long appeal. For providers treating patients with cocaine addiction, F14.20 sits at the center of that accuracy. This ICD-10-CM code represents cocaine dependence, uncomplicated, a classification that applies to both moderate and severe cocaine use disorder when no acute complications, such as intoxication, withdrawal, or induced psychiatric disorders, are present at the time of the encounter. Billers, coders, and clinicians who understand exactly what this code captures, and what it does not, will submit stronger claims and maintain cleaner audit trails.
What F14.20 Actually Means
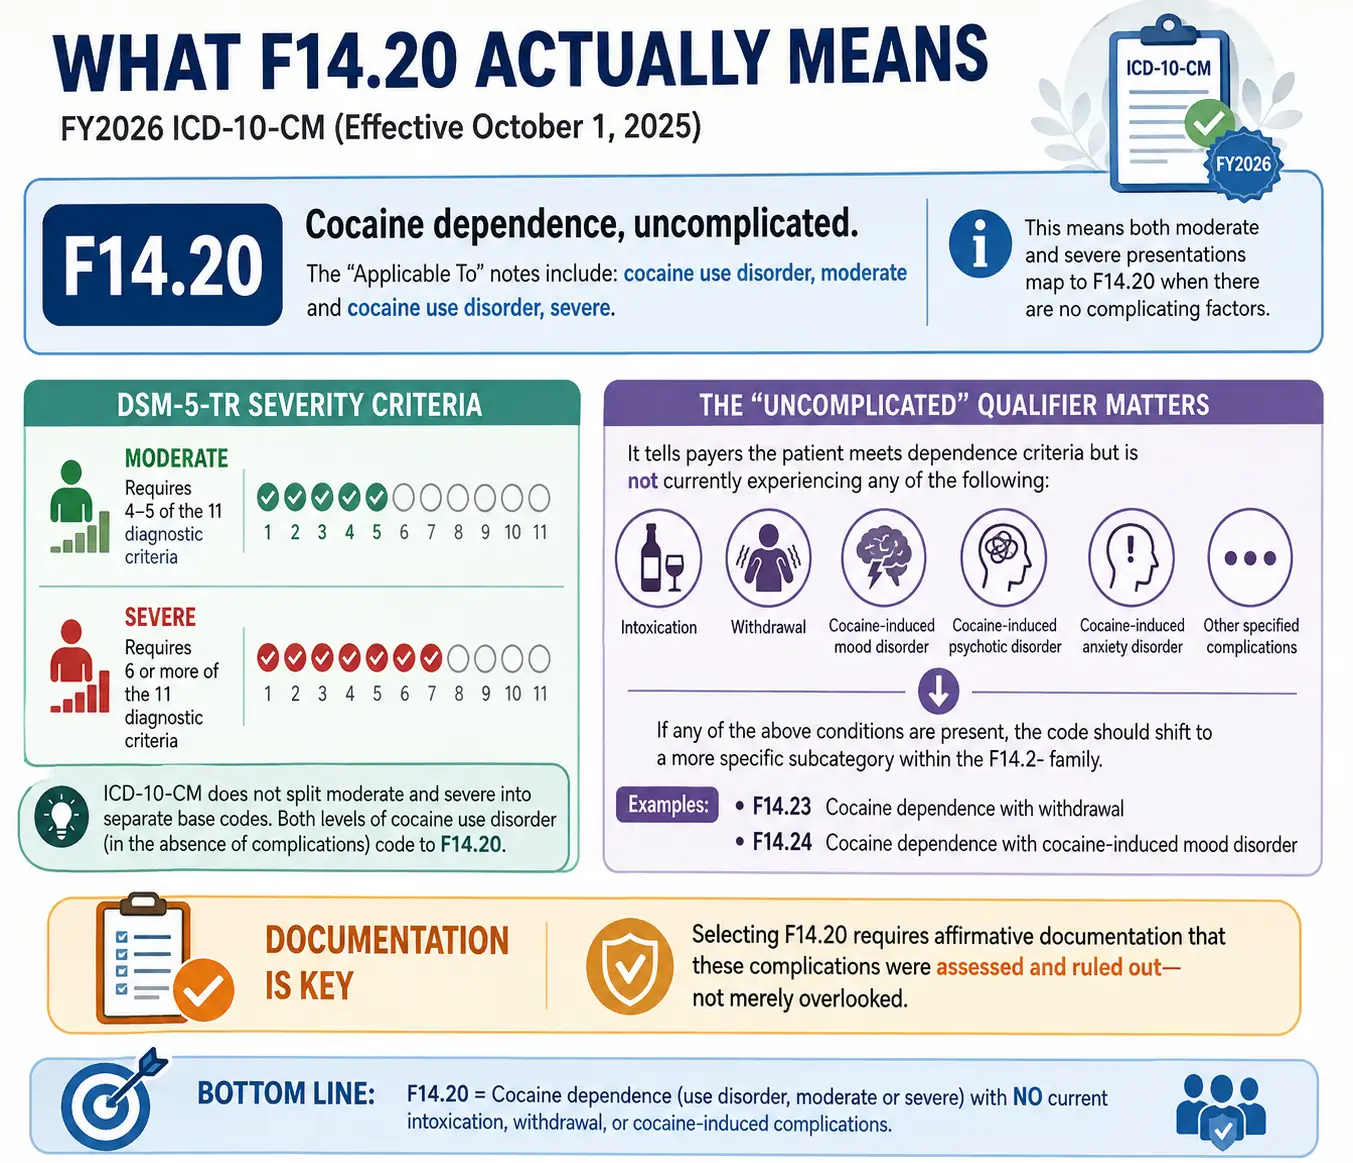
The FY2026 ICD-10-CM tabular list, effective October 1, 2025, defines F14.20 as “Cocaine dependence, uncomplicated.” The code’s “Applicable To” notes explicitly include cocaine use disorder, moderate and cocaine use disorder, severe. This dual applicability confuses some coders. In DSM-5-TR terms, a moderate stimulant use disorder requires four or five of the eleven diagnostic criteria, while a severe diagnosis requires six or more. ICD-10-CM does not split moderate and severe into separate base codes. Instead, both severity levels map to F14.20 when the presentation lacks complicating factors.
The “uncomplicated” qualifier carries weight. It tells payers the patient meets dependence criteria but is not currently intoxicated, withdrawing, or suffering from a cocaine-induced mood disorder, psychotic disorder, anxiety disorder, or other specified complication. If any of those conditions exist, the code shifts to a more specific subcategory within the F14.2- family, such as F14.23 for withdrawal or F14.24 for cocaine-induced mood disorder. Selecting F14.20 requires affirmative documentation that these complications were assessed and ruled out, not merely overlooked.
The Clinical Criteria Providers Must Document
The 11 DSM-5-TR Symptoms
The American Psychiatric Association’s DSM-5-TR, published in 2022, sets the clinical standard for diagnosing stimulant use disorder. The criteria apply across stimulant types, including cocaine, amphetamines, and prescription stimulants misused outside medical supervision. A diagnosis requires at least two of the following eleven symptoms within twelve months, with severity determined by the total count.
The criteria fall into four clusters. Impaired control covers taking larger amounts than intended, persistent desire or unsuccessful efforts to cut down, spending excessive time obtaining or recovering from the substance, and craving. Social impairment includes failure to fulfill major role obligations, continued use despite interpersonal problems, and giving up important activities. Risky use captures recurrent use in physically hazardous situations and continued use despite knowledge of physical or psychological problems likely caused or exacerbated by the drug. Pharmacologic indicators include tolerance and withdrawal.
For F14.20 specifically, the provider’s note should reference which criteria the patient meets and the total symptom count. A note stating “cocaine use disorder, severe, six criteria met” supports F14.20. A vague label of “cocaine dependence” without criteria enumeration leaves the claim vulnerable to payer scrutiny.
Why “Uncomplicated” Matters
The uncomplicated designation does not mean the patient’s condition is mild. It means the encounter does not involve an acute complicating condition that requires additional coding specificity. A patient with severe cocaine use disorder who presents for a stable outpatient therapy session, with no current intoxication, no withdrawal syndrome, and no induced psychosis, receives F14.20. The same patient arriving in the emergency department with cocaine-induced psychotic disorder featuring paranoid delusions would instead warrant F14.250 as the primary diagnosis, with F14.20 potentially dropping to a secondary position or disappearing entirely depending on the clinical circumstances.
This distinction directly affects reimbursement. Uncomplicated codes typically group to different MS-DRG weights and authorization pathways than complicated presentations. Coders who default to F14.20 for every cocaine-dependent patient undercode when complications exist. Conversely, providers who assign complication codes without explicit clinical evidence risk compliance violations.
Documentation Rules That Protect Your Claims
The ICD-10-CM Official Guidelines for Coding and Reporting, maintained by CMS and the National Center for Health Statistics, govern how substance use codes are assigned. Section I.C.5.b.2 establishes a strict hierarchy: when a provider documents both abuse and dependence for the same substance, coders must assign only the dependence code. An intake note describing “cocaine abuse” combined with a psychiatric evaluation stating “cocaine dependence” yields F14.20, not F14.10. The higher-severity code wins.
Section I.C.5.b.1 adds another layer: remission codes such as F14.21 require explicit provider documentation. A negative urine drug screen alone does not justify switching an active F14.20 to remission status. The provider must state that the patient is in early or sustained remission.
For F14.20 claims to survive audit, the medical record should contain three elements. First, a diagnostic statement from a qualified provider linking the patient to cocaine use disorder with documented severity. Second, evidence that intoxication, withdrawal, and induced disorders were actively ruled out through assessment, not omission. Third, a clear connection between the diagnosis and the service provided. A progress note reading “Patient reports continued cocaine use, three grams weekly via insufflation. Meets six DSM criteria for severe stimulant use disorder. No current withdrawal symptoms. No intoxication on exam. No hallucinations or delusions. Diagnosis: F14.20” satisfies all three requirements.
Coding Errors That Trigger Denials
The most common error in the F14 family happens before the fourth character is selected: placing a methamphetamine patient in F14 or a cocaine patient in F15. The FY2026 tabular list draws a hard line. F14 covers cocaine in all forms, including powder and crack. F15 covers every other stimulant: methamphetamine, amphetamine, prescription stimulant misuse such as Adderall, and MDMA. Because the relationship is Excludes2 rather than Excludes1, a patient using both cocaine and methamphetamine can carry both F14.20 and F15.20 on the same claim, provided each substance is documented separately.
Another frequent mistake involves remission timing. A residential facility cannot bill F14.20 for continued stay while simultaneously documenting remission. The diagnosis must match the treatment rationale. If the patient has stabilized and the provider documents sustained remission, the code should shift to F14.21, and the level of care may need step-down justification.
Unspecified use codes such as F14.90 also cause problems. Per Official Guidelines Section I.C.5.b.3, these codes require documented use plus a documented link to a related disorder or medical condition. Coders sometimes reach for F14.90 when documentation is thin. That choice often backfires during authorization reviews because unspecified codes carry the lowest clinical severity and frequently fail to support medical necessity for intensive services like residential treatment or intensive outpatient programs.
Billing and Reimbursement Essentials
MS-DRG Assignment
In the inpatient setting, F14.20 groups to MS-DRG categories 894 through 897 under the Alcohol, Drug Abuse or Dependence classification. The specific assignment depends on whether the patient left against medical advice (894), received rehabilitation therapy (895), or was treated without rehabilitation therapy, with or without major complications and comorbidities (896 and 897). Coders should verify that the principal diagnosis and any CCs or MCCs align with the MS-DRG logic for the admission.
Service Codes by Level of Care
Unlike opioid use disorder, which often anchors medical necessity claims to medication-assisted treatment protocols, cocaine use disorder has no FDA-approved pharmacotherapy. This absence shifts the entire burden of medical necessity onto documented psychosocial treatment intensity and dimensional severity.
For residential treatment, common HCPCS codes include H0017, H0018, and H0019. Partial hospitalization and intensive outpatient programs typically bill H0035 or H0015. Outpatient individual therapy uses 90834 or 90837, while group therapy maps to 90853. Initial assessments fall under 90791 or H0001.
Authorization reviewers look for specificity in the treatment plan. A plan stating “continue therapy” will not suffice. Instead, the record should detail craving-management skills, contingency-management participation where available, structured scheduling to interrupt the binge-crash cycle, and explicit tracking of co-occurring mood symptoms. The post-use crash can mimic major depressive disorder, and the plan should clarify whether the provider views mood symptoms as substance-induced or primary.
Treatment Planning Without FDA-Approved Medication
The lack of an FDA-approved medication for cocaine use disorder changes how providers build their clinical narrative. Payers cannot rely on a buprenorphine or methadone protocol to justify continued stay. They look instead at ASAM criteria dimensions, particularly Dimension 1 (acute intoxication/withdrawal potential), Dimension 2 (biomedical conditions), Dimension 3 (emotional/behavioral/cognitive conditions), and Dimension 5 (relapse potential).
Contingency management, which provides tangible incentives for verified abstinence, currently holds the strongest evidence base for stimulant use disorders according to SAMHSA guidance. When a program offers contingency management, the treatment plan should name it specifically. The plan should also document baseline craving scores, urine drug screen schedules, and step-down criteria tied to measurable outcomes rather than calendar dates alone.
A Practical Documentation Example
Consider a 34-year-old patient admitted to a partial hospitalization program. The intake note documents daily cocaine use via inhalation for the past eight months, with two failed quit attempts. The patient lost a construction job due to attendance issues, reports spending four to five hours daily obtaining and using cocaine, and meets six DSM-5-TR criteria. Current examination shows no signs of intoxication, no withdrawal symptoms, and no perceptual disturbances. The provider assigns F14.20.
The treatment plan includes daily PHP programming billed under H0035, weekly individual therapy under 90834, and contingency-management incentives tied to thrice-weekly negative urine screens. The plan notes a mood re-evaluation at day fourteen after sustained abstinence to differentiate cocaine-induced dysphoria from a primary depressive disorder. At reassessment, the mood symptoms have resolved. The provider removes any mood-disorder code and continues PHP under F14.20 with step-down to IOP planned upon three consecutive negative screens and a craving-scale score below a defined threshold.
This example illustrates clean coding: the diagnosis matches the documented severity, the service codes match the level of care, and the plan contains measurable goals that justify continued treatment without medication.
Key Takeaways for Accurate F14.20 Coding
F14.20 applies to moderate or severe cocaine use disorder when the patient presents without acute intoxication, withdrawal, or induced psychiatric complications. The DSM-5-TR criteria provide the clinical foundation, with four to five symptoms indicating moderate severity and six or more indicating severe. Coders must respect the hierarchy that elevates dependence over abuse, must obtain explicit provider language before assigning remission codes, and must never use unspecified codes as a shortcut. Because no FDA-approved medication exists for this disorder, medical necessity rests entirely on detailed psychosocial treatment plans, structured levels of care, and documented severity. Accurate F14.20 coding starts with thorough clinical documentation and ends with claims that reflect exactly what happened in the treatment room.