



The F11.20 diagnosis code represents "Opioid dependence, uncomplicated" in the ICD-10-CM classification system. Healthcare providers and medical billers use this specific alphanumeric string to classify patients with moderate to severe opioid use disorder. This code applies specifically when the patient is not actively experiencing withdrawal, intoxication, or opioid-induced mental disorders during the clinical encounter.
Proper application of the F11.20 diagnosis code determines clinical care pathways and dictates reimbursement rates for addiction medicine practices. Medical claims featuring substance use disorder diagnoses face high scrutiny from commercial payers and federal health programs. According to the Centers for Medicare and Medicaid Services (CMS) 2024 Official Guidelines for Coding and Reporting, improper documentation of substance use disorders remains a frequent trigger for medical claim audits. Medical billers must understand the strict criteria required to assign this code successfully.
Clinical definition of the F11.20 diagnosis code
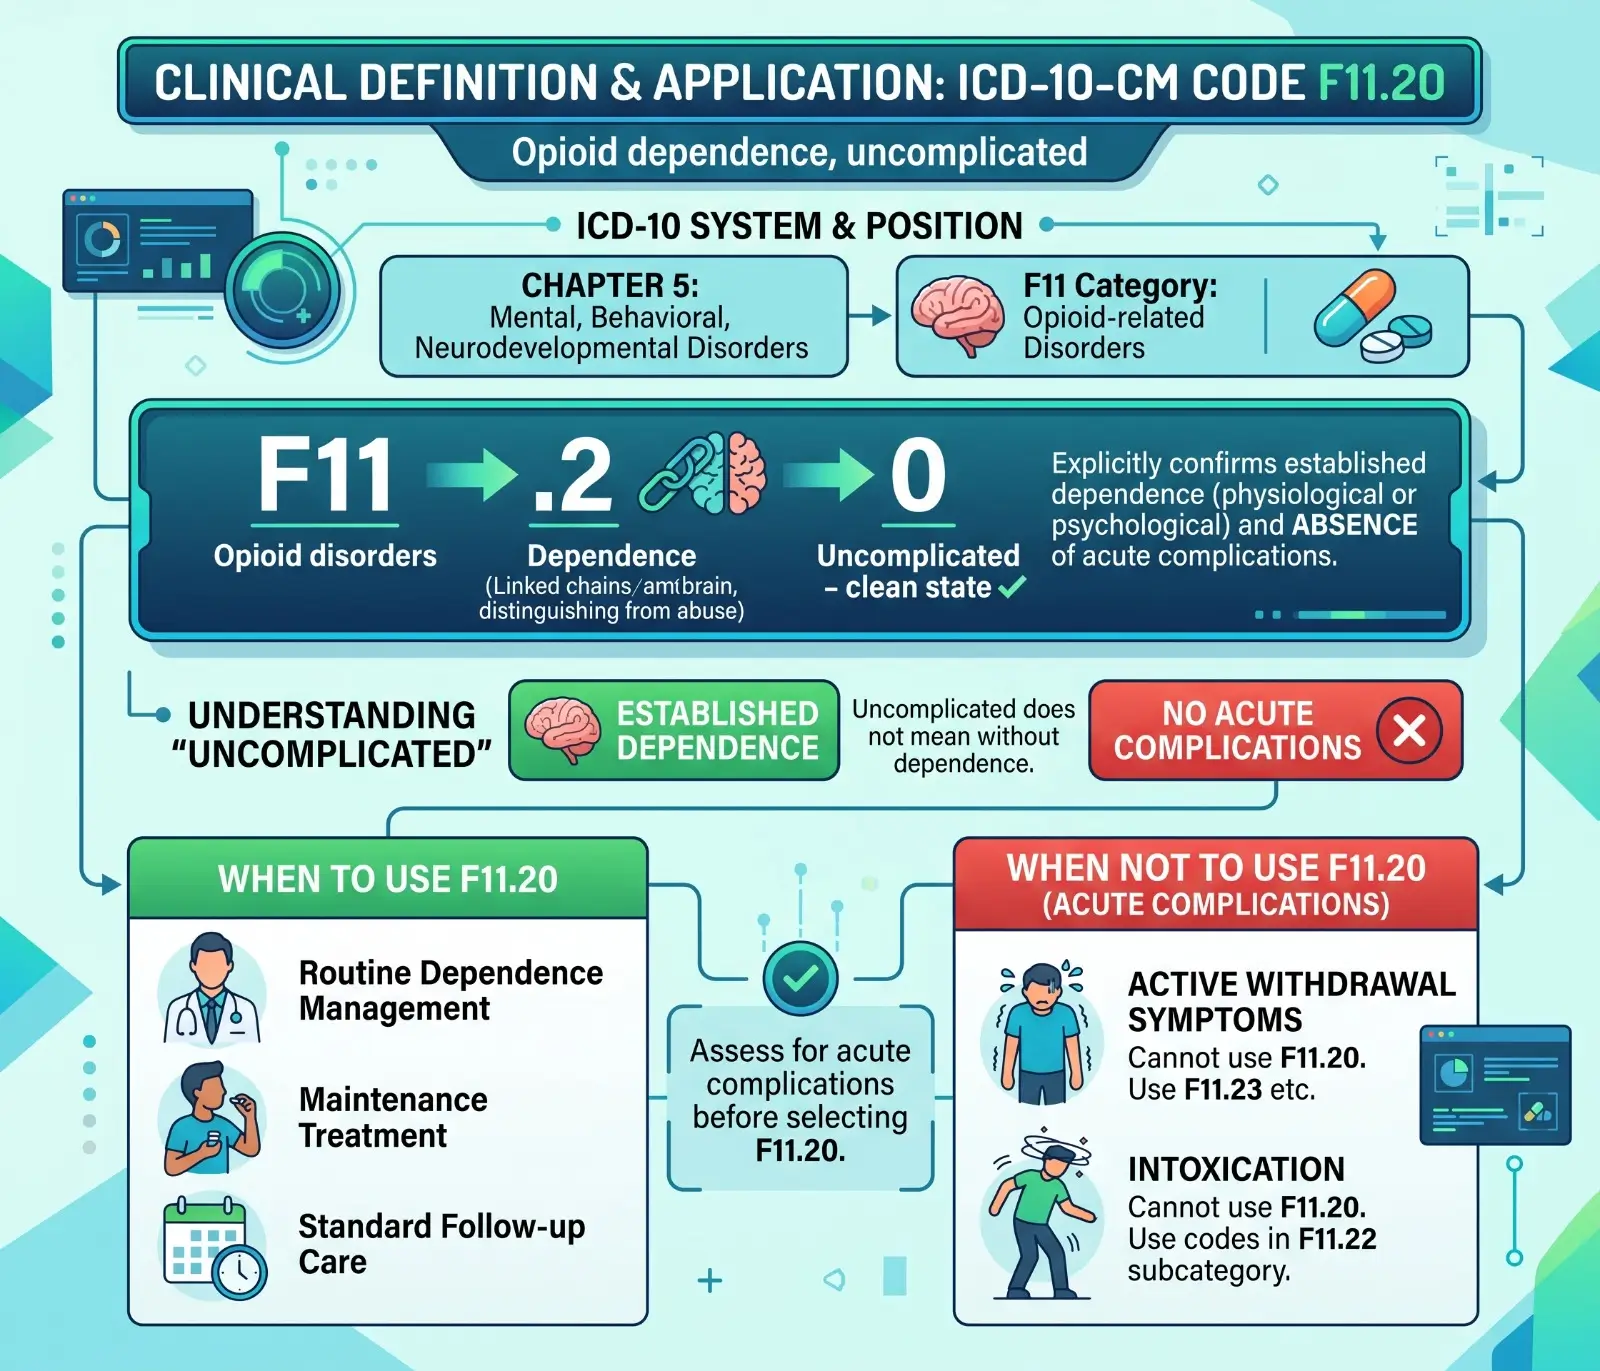
The ICD-10-CM system uses specific character positions to convey exact medical information. The F11.20 code sits within Chapter 5, which covers Mental, Behavioral, and Neurodevelopmental disorders.
The structure breaks down into specific diagnostic elements. The "F11" category designates opioid-related disorders. The ".2" extension specifies dependence, separating it from abuse or unspecified use. The final "0" indicates the condition is uncomplicated.
The term "uncomplicated" carries a specific clinical meaning in medical coding. It confirms the patient has an established physiological or psychological dependence on opioids. It also explicitly confirms the absence of acute complications. If a patient presents to a clinic actively experiencing withdrawal symptoms, the coder cannot use F11.20. They must use a combination code such as F11.23 (Opioid dependence with withdrawal). Similarly, if the patient is intoxicated, codes in the F11.22 subcategory apply.
F11.20 is standard for patients presenting for routine dependence management, maintenance treatment, or standard follow-up care.
Diagnostic criteria and DSM-5 alignment
Medical coders cannot assign a dependence code based on a provider writing "opioid use" in a chart. The clinical documentation must align with established diagnostic standards. According to the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR) published by the American Psychiatric Association in 2022, a diagnosis of opioid use disorder requires specific behavioral and physical markers.
The F11.20 code encompasses both moderate opioid use disorder (defined as four to five symptoms) and severe opioid use disorder (defined as six or more symptoms). Providers must document that the patient exhibits these criteria within a continuous 12-month period.
Auditors look for explicit documentation of these symptoms in the electronic health record. Providers must note when a patient takes opioids in larger amounts or over a longer period than intended. They must document unsuccessful efforts to cut down or control opioid use. The clinical notes should detail the excessive time the patient spends obtaining, using, or recovering from the effects of opioids.
Physical indicators also support the F11.20 diagnosis. Providers document tolerance, which occurs when a patient requires markedly increased amounts of opioids to achieve the desired effect. They also document withdrawal history, noting that the patient previously experienced withdrawal syndrome when opioid use ceased or diminished.
ICD-10-CM coding hierarchy for substance use
One of the most frequent errors in behavioral health billing involves confusing use, abuse, and dependence. The ICD-10-CM Official Guidelines establish a strict hierarchy for substance use disorders. Coders must follow these rules when a provider documents multiple levels of substance use in the same clinical encounter.
- If the provider documents both substance use and substance abuse, the coder assigns only the code for abuse.
- If the provider documents both substance abuse and substance dependence, the coder assigns only the code for dependence (F11.20).
- If the provider documents use, abuse, and dependence, the coder assigns only the code for dependence (F11.20).
- If the provider documents substance use and substance dependence, the coder assigns only the code for dependence (F11.20).
This hierarchy exists because dependence represents the highest severity level of the disorder. Assigning multiple codes for the same substance violates coding guidelines and triggers automated claim denials.
| ICD-10-CM Code | Clinical Designation | Documentation Requirement |
|---|---|---|
| F11.10 | Opioid abuse, uncomplicated | Harmful use pattern causing impairment without physiological dependence. |
| F11.20 | Opioid dependence, uncomplicated | Compulsive use, tolerance, and reliance without active withdrawal or intoxication. |
| F11.21 | Opioid dependence, in remission | Provider explicitly states the patient is in early or sustained remission. |
| F11.23 | Opioid dependence with withdrawal | Provider documents active physiological withdrawal symptoms during the visit. |
Specific documentation requirements for F11.20 claims
To secure reimbursement for services tied to F11.20, the clinical documentation must paint a clear picture of the patient's condition. Generic templates stating "patient has opioid addiction" fail commercial payer audits. A 2023 report published by the Department of Health and Human Services Office of Inspector General (HHS-OIG) found high error rates in behavioral health billing primarily due to insufficient documentation of dependence criteria.
Providers must identify the specific substance. The notes should clarify whether the patient depends on prescription opioids (such as oxycodone or hydrocodone), synthetic opioids (such as fentanyl), or illicit substances (such as heroin).
The documentation must detail functional impairment. Medical billers need providers to record how the dependence affects the patient's daily life. This includes documenting missed workdays, decreased occupational productivity, and the abandonment of important social or recreational activities. Providers should also note relationship difficulties or financial problems directly attributed to drug-seeking behavior.
Current status indicators are mandatory. The provider note must state that the dependence is active. The assessment section of the note should clearly summarize the treatment response, noting whether the patient is stable on their current regimen or requires dosage adjustments.
Medication for opioid use disorder (MOUD) guidelines
Billing for patients receiving Medication for Opioid Use Disorder requires specific code combinations. F11.20 applies when a patient is dependent on opioids as a substance of misuse. It also applies to patients receiving prescribed treatments such as methadone or buprenorphine, provided they have not met the clinical criteria for full remission.
When a provider prescribes methadone or buprenorphine for maintenance therapy, the coder uses F11.20 as the primary diagnosis code. The coder must also assign Z79.891 (Long term current use of opiate analgesic) as a secondary code. This secondary code informs the insurance payer that the patient takes a prescribed opioid medication as part of their evidence-based treatment plan.
A common billing error occurs when billers apply F11.20 to a patient dependent on prescribed opioids strictly for chronic pain management. If a patient takes prescribed pain medication precisely as directed and develops physiological tolerance without compulsive drug-seeking behavior, they do not have an opioid use disorder. In chronic pain scenarios, providers use codes from the G89 category (Pain, not elsewhere classified) and Z79.891, entirely avoiding the F11 category.
Transitioning from active dependence to remission
Coders frequently struggle with knowing when to transition a patient from F11.20 (active dependence) to F11.21 (dependence, in remission). This transition dictates changes in authorized treatment plans and billing cycles.
The ICD-10-CM guidelines are explicit regarding remission. A medical coder cannot independently determine that a patient is in remission based on negative drug screens or a lack of reported cravings. The provider must explicitly write "in remission" in the clinical note.
Until the provider documents sustained remission, F11.20 remains the correct code. This applies even if the patient has been stable on buprenorphine for several months. The American Society of Addiction Medicine (ASAM) defines early remission as a period of at least three months without meeting criteria for active dependence (except for cravings). Sustained remission requires twelve months. Coders must wait for the provider's formal clinical assessment before altering the final digit of the diagnosis code.
Billing combinations and outpatient procedures
The F11.20 diagnosis code pairs with specific Current Procedural Terminology (CPT) codes to generate revenue for outpatient encounters. Proper alignment between the diagnosis and the procedure prevents claim rejections.
For standard medical management, providers use Evaluation and Management (E/M) codes 99202 through 99215. The level of the E/M code depends on medical decision-making complexity or total time spent with the patient. Managing active opioid dependence frequently justifies moderate (99214) or high (99215) complexity codes due to the prescription of controlled substances and the inherent risks of the condition.
When behavioral health specialists provide therapy, they use specific psychotherapy codes. Typical pairings with F11.20 include 90832 (30 minutes of psychotherapy), 90834 (45 minutes of psychotherapy), and 90837 (60 minutes of psychotherapy).
If a physician or psychiatric nurse practitioner provides both medical management and psychotherapy during the same visit, they bill the appropriate E/M code along with a psychotherapy add-on code, such as 90833, 90836, or 90838.
Telehealth modifiers and virtual care
Addiction medicine providers increasingly treat F11.20 patients via telemedicine. When a provider conducts a virtual visit for opioid dependence, the biller appends specific modifiers to the CPT codes. Medicare requires the 95 modifier (Synchronous telemedicine service rendered via a real-time interactive audio and video telecommunications system) for most virtual behavioral health services.
Commercial payers may require the GT modifier instead. Accurate application of these modifiers alongside the F11.20 diagnosis proves that the provider delivered standard care through an approved digital medium.
Audit triggers and claim denial prevention
Insurance companies utilize automated software to flag coding irregularities. Claims featuring F11.20 frequently face pre-payment reviews.
Truncated codes cause immediate automatic rejections. The F11 code block requires all five characters. Submitting a claim with only "F11.2" results in a denial for an invalid diagnosis code.
Mismatching the diagnosis with the procedure also triggers audits. For example, billing an intensive outpatient program (IOP) per diem code (H0015) typically requires an active dependence code like F11.20. If a biller uses F11.10 (abuse) for an IOP claim, the payer will likely deny it, arguing that standard abuse does not meet the medical necessity threshold for intensive outpatient care.
Another frequent audit trigger involves billing F11.20 on the same date of service as a hospital emergency department visit for an overdose. If the patient suffered an overdose, they were intoxicated. The coder must use the specific complication code, such as F11.229 (Opioid dependence with intoxication, unspecified), rather than the uncomplicated code.
Maintaining compliance in clinical documentation
Maintaining accurate F11.20 claims requires clear communication between the medical biller and the healthcare provider. The biller must query the provider when notes lack the necessary details regarding the specific substance, the presence of physiological dependence, or the functional impairments caused by the disorder.
Accurate assignment of the F11.20 diagnosis code protects healthcare practices from financial penalties during post-payment audits. Medical coders ensure compliance by verifying the provider explicitly documented opioid dependence, confirmed the absence of acute complications during the encounter, and linked the diagnosis to recognized DSM-5 criteria. Thorough clinical documentation provides payers with the exact clinical picture required to approve claims and fund ongoing addiction treatment.