



According to the 2024 ICD-10-CM official coding guidelines published by the Centers for Medicare & Medicaid Services (CMS) and the National Center for Health Statistics (NCHS), the F32.1 ICD-10 diagnosis code for moderate depression classifies a single episode of major depressive disorder characterized by moderate severity. Medical coders and healthcare providers use this specific alphanumeric identifier to process insurance claims, justify medical necessity for behavioral health services, and track epidemiological data.
The United States healthcare system transitioned from the ICD-9 classification system to ICD-10-CM in October 2015. Under the previous system, medical billers reported a single episode of moderate major depressive disorder using code 296.22. The mapping to F32.1 introduced a more specific alphanumeric structure requiring exact documentation of the episode count, severity level, and absence of psychotic features.
Data published by the National Institute of Mental Health (NIMH) in 2023 indicates that an estimated 21 million adults in the United States experienced at least one major depressive episode during the reporting year. Because a significant percentage of these patients present in primary care settings rather than specialized psychiatric facilities, accurate application of the F32.1 code is a standard requirement for coders across multiple medical specialties.
Clinical criteria supporting moderate severity
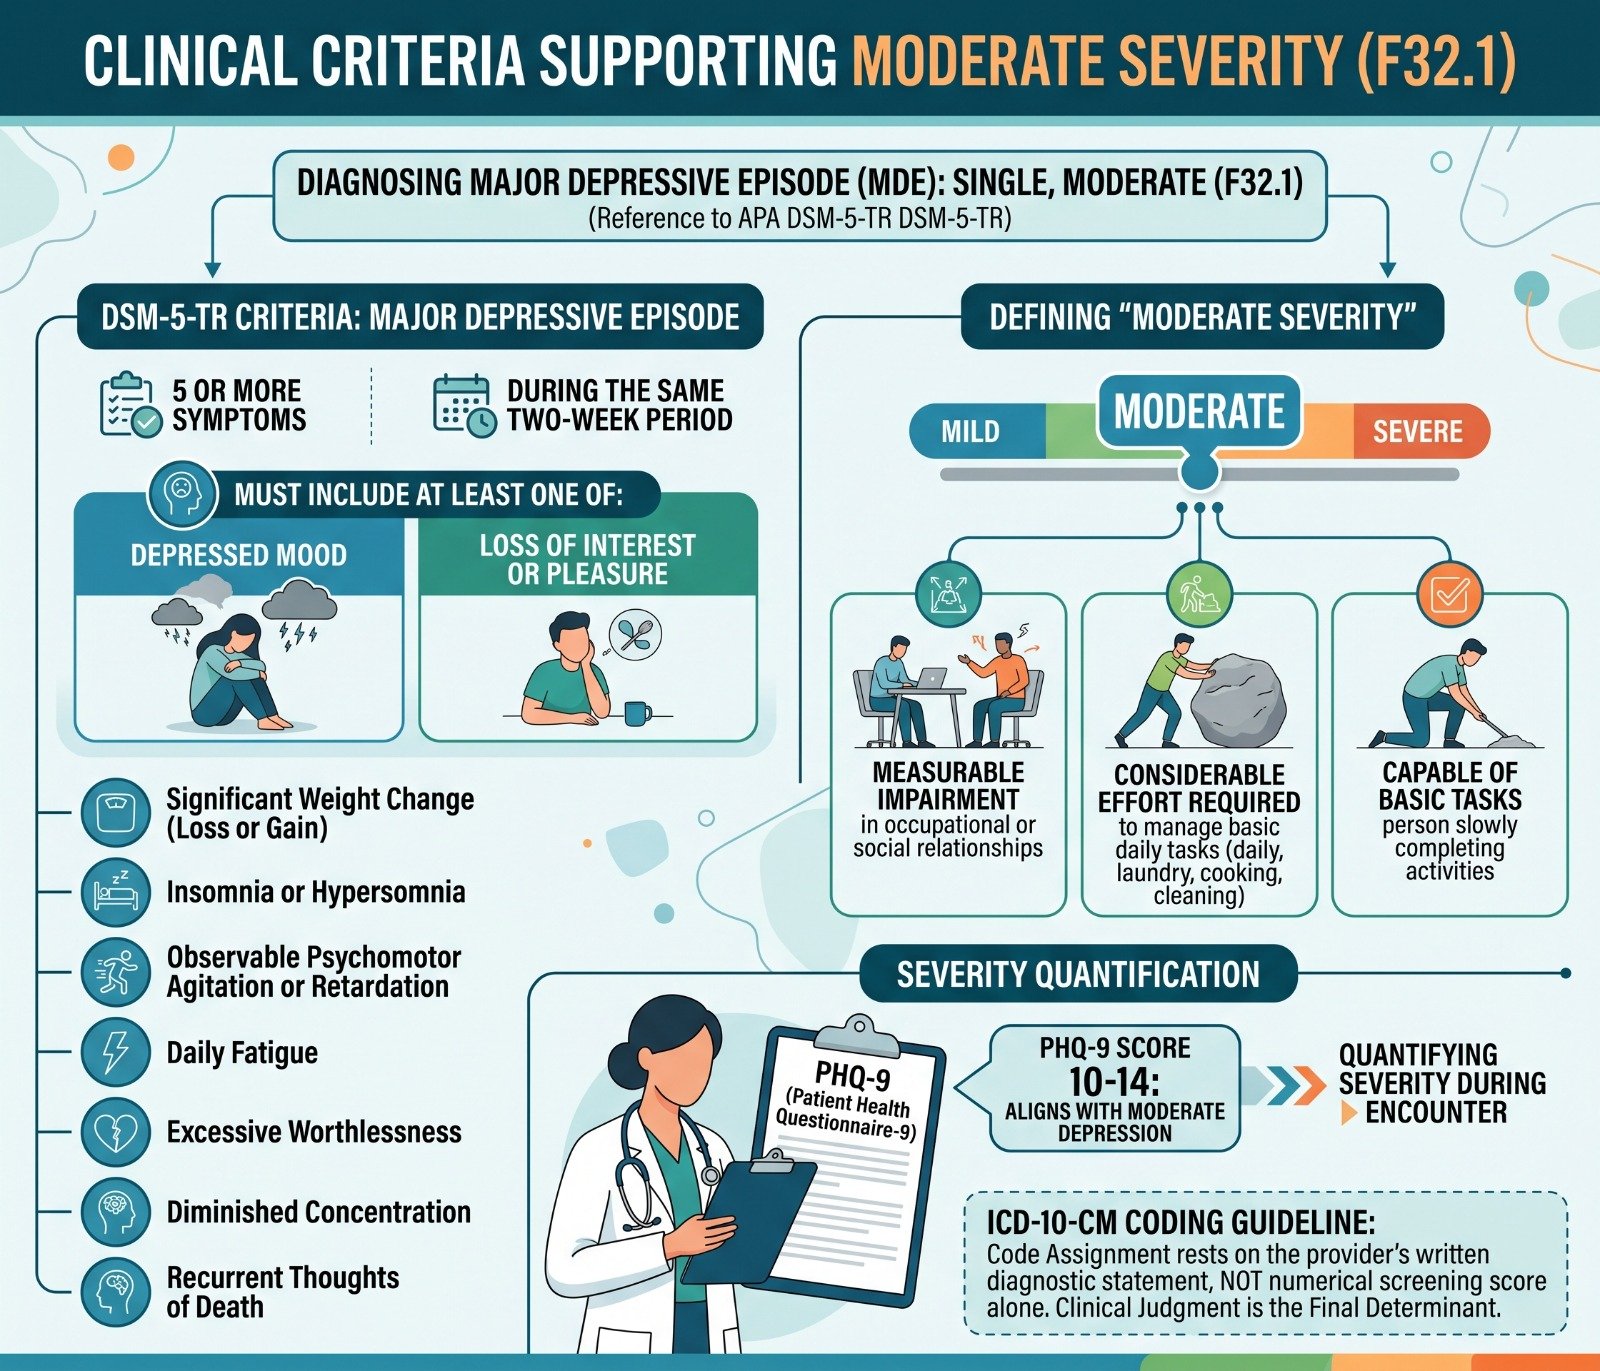
To justify reporting F32.1 on a medical claim, the provider's clinical documentation must indicate a major depressive episode that is both a single occurrence and moderate in severity. The American Psychiatric Association (APA) outlines the diagnostic criteria for Major Depressive Disorder (MDD) in the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR).
A patient must present with five or more specific symptoms during the exact same two-week period. At least one of those symptoms must be either a depressed mood or a distinct loss of interest or pleasure in daily activities. Other qualifying symptoms include significant unintended weight loss or gain, insomnia or hypersomnia, observable psychomotor agitation or retardation, daily fatigue, feelings of excessive worthlessness, a diminished ability to concentrate, and recurrent thoughts of death.
The designation of "moderate" means the clinical presentation falls squarely between mild and severe. The documented symptoms cause measurable impairment in occupational functioning or social relationships. The patient remains capable of managing basic daily tasks, but requires considerable effort to do so.
Physicians frequently utilize standardized psychometric screening tools to quantify this severity during the patient encounter. The Patient Health Questionnaire-9 (PHQ-9) is the most widely adopted assessment instrument in general medical practice. A PHQ-9 score ranging from 10 to 14 typically aligns with moderate depression. Clinical judgment remains the final determinant. The ICD-10-CM coding guidelines state that code assignment rests on the provider's written diagnostic statement rather than the numerical result of a screening score alone.
Strict documentation requirements for medical coders
Medical billers cannot assume a diagnosis of moderate depression based on a list of prescribed selective serotonin reuptake inhibitors (SSRIs) or a patient's verbal complaints of sadness. The medical record must contain an explicit diagnostic statement authored by a physician, nurse practitioner, physician assistant, or licensed mental health professional.
A compliant chart note for the F32.1 ICD-10 diagnosis code for moderate depression includes three distinct elements. The documentation must state the episode is a single occurrence. It must declare the severity as moderate. It must state that psychotic features are absent. If a patient experiences hallucinations or delusions during the depressive episode, the diagnostic category shifts. The correct code for a single episode with psychotic features is F32.3.
Auditors from the Office of Inspector General (OIG) regularly review behavioral health claims to identify specificity errors. When a provider documents "depression" without specifying the episode count or severity, coders must assign the unspecified code F32.A. Commercial payers and Medicare Administrative Contractors deny claims containing unspecified codes at a higher rate than claims containing specific codes like F32.1.
Navigating Excludes1 and Excludes2 instructions
The ICD-10-CM tabular list contains specific instructional notes dictating when multiple conditions can or cannot be billed together on a CMS-1500 claim form. Medical coders must review both Excludes1 and Excludes2 notes applied to category F32 before reporting F32.1.
An Excludes1 note acts as a strict billing prohibition. It means the two conditions cannot occur together by clinical definition. For the F32 category, the Excludes1 list contains bipolar disorder (F31.-), manic episodes (F30.-), and recurrent depressive disorder (F33.-). If a patient's medical record shows a history of a previous major depressive episode, the current episode is recurrent. The coder must use a code from the F33 category instead of F32.1. A 2023 study published in the Journal of Clinical Psychiatry analyzed commercial claims data and found that nearly 18 percent of MDD diagnoses were miscoded as single episodes (F32.-) when historical chart reviews revealed previous depressive episodes.
An Excludes2 note indicates that the excluded condition is not part of the condition represented by the primary code. A patient may have both conditions simultaneously. The Excludes2 note for category F32 includes adjustment disorders (F43.2-). If a patient meets the clinical criteria for a single episode of moderate major depression and simultaneously has an adjustment disorder related to a separate external stressor, the biller can report both codes on the claim.
Comparing F32.1 to related depressive disorder codes
Selecting the correct code requires medical coders to differentiate F32.1 from closely related diagnoses located in the F32 and F33 blocks. The following table illustrates the exact distinctions between these primary codes based on episode frequency and severity.
| ICD-10 Code | Episode Count | Clinical Severity | Psychotic Features |
|---|---|---|---|
| F32.0 | Single | Mild | Absent |
| F32.1 | Single | Moderate | Absent |
| F32.2 | Single | Severe | Absent |
| F32.3 | Single | Severe | Present |
| F33.1 | Recurrent | Moderate | Absent |
The distinction between F32.1 and F33.1 rests entirely on the patient's psychiatric history. Coders must query the provider if the medical record contains conflicting information regarding past depressive episodes.
Linking F32.1 with CPT codes for claim submission
Medical billers use F32.1 to establish medical necessity for specific Current Procedural Terminology (CPT) codes. The diagnosis code justifies why the medical service was necessary, while the CPT code identifies exactly what the provider did.
Psychiatric diagnostic evaluation (CPT 90791 for non-medical services or CPT 90792 for medical services) is frequently paired with F32.1 during the initial patient assessment. For ongoing treatment, mental health providers link F32.1 to time-based psychotherapy codes such as 90832 (30 minutes), 90834 (45 minutes), or 90837 (60 minutes).
Primary care physicians treat a large percentage of moderate depression cases and link F32.1 to standard Evaluation and Management (E/M) codes. CPT codes 99213 or 99214 represent office visits for established patients. The selection between these specific E/M codes depends on the medical decision-making complexity or the total time the provider spent on the date of the encounter. Initiating prescription management for a single episode of moderate depression typically qualifies as a moderate level of medical decision-making. This supports billing CPT 99214 if all other E/M documentation requirements are met.
Incorporating Z codes for social determinants of health
In 2024, CMS issued updated guidance encouraging healthcare facilities to report Z codes alongside primary behavioral health diagnoses. Codes from categories Z55 through Z65 capture Social Determinants of Health (SDOH). These factors frequently influence the severity and treatment of moderate depression.
If a patient diagnosed with F32.1 also experiences housing instability, the coder should append Z59.00 (Homelessness, unspecified). If the patient recently lost their job, the coder can report Z56.0 (Unemployment, unspecified). While Z codes do not typically increase direct reimbursement on a fee-for-service claim, Medicare and Medicare Advantage plans use this data to calculate risk adjustment scores and allocate population health resources. Coders can abstract SDOH data from notes written by social workers or nurses, provided the primary physician has documented the underlying F32.1 diagnosis.
Application in specialized patient populations
The F32.1 code applies across different demographic groups, though clinical assessment methods vary by age. When evaluating pediatric and adolescent patients, pediatricians use the PHQ-A (a version modified for adolescents) or the Center for Epidemiological Studies Depression Scale for Children (CES-DC). The strict documentation requirements for medical coders remain identical regardless of the patient's age. The chart must explicitly list a single episode of moderate severity.
For perinatal or postpartum depression, coders must follow specific sequencing rules outlined in Chapter 15 of the ICD-10-CM guidelines (Pregnancy, Childbirth, and the Puerperium). Codes from category O90.6 (Postpartum mood disturbance) take mandatory sequencing priority. If a female patient experiences a single episode of moderate major depression within six weeks of childbirth, the biller must report O90.6 as the primary diagnosis. F32.1 is listed as the secondary diagnosis to identify the specific psychiatric condition.
Common reasons for claim denials
Insurance payers deny claims involving F32.1 for several specific reasons. The most frequent clinical denial occurs due to a lack of detailed documentation supporting the "moderate" severity level. If the provider simply writes "depression" in the assessment and plan, but the biller codes F32.1, an audit will result in a retraction of payment.
Payers also reject claims when the diagnosis code contradicts the patient's historical claims data. If a payer's internal system shows a paid claim for a major depressive episode in 2022, and a new claim arrives in 2025 using F32.1 (single episode), the payer's automated claims editing software will flag the mismatch. The correct code for the 2025 encounter is F33.1 (recurrent). Coders must verify previous internal billing records for established patients before applying a single-episode code.
Another frequent denial involves the misuse of psychiatric add-on codes. If a physician bills for an E/M service (like 99214) and an add-on psychotherapy code (like 90833) during the same visit, the documentation must separate the time and interventions. The chart note must show the medical management (prescribing medication, reviewing side effects) distinct from the specific psychotherapeutic techniques used. The F32.1 diagnosis supports both services, but the physical chart note must reflect two entirely distinct services to pass a payer audit.
Practical coding scenario for F32.1
A 45-year-old male patient presents to his primary care physician complaining of fatigue, insomnia, and a loss of interest in his usual hobbies over the past month. He has no prior history of psychiatric care. The physician administers a PHQ-9, which yields a score of 12.
The physician's assessment note states: "Major depressive disorder, single episode. The patient's symptoms are moderate in severity, affecting his ability to focus at work, though he is still employed. No suicidal ideation. No history of mania or psychosis. Will start on 50mg Zoloft daily."
The medical coder reviews this documentation. The record clearly indicates "single episode." It specifies "moderate." It notes the absence of psychosis and mania. The patient has no prior history. The coder correctly assigns the F32.1 ICD-10 diagnosis code for moderate depression. The coder links this diagnosis to CPT 99214 based on the moderate complexity of initiating prescription drug management for a new problem. This claim meets all CMS and commercial payer requirements for clean submission.