



F50.0 Diagnosis Code Explained: Symptoms, Billing, and ICD-10 Guidelines
The F50.0 diagnosis code represents anorexia nervosa within the International Classification of Diseases, Tenth Revision, Clinical Modification (ICD-10-CM). Mental health professionals, physicians, and medical coders use this classification to document a severe eating disorder defined by a restriction of energy intake, an intense fear of weight gain, and a disturbance in body image.
According to 2023 statistics published by the National Institute of Mental Health, anorexia nervosa carries the highest mortality rate among all psychiatric diagnoses. This risk stems directly from physical complications such as starvation, cardiac arrest, and suicide. For medical billers and coders, translating this psychiatric condition into alphanumeric codes requires strict adherence to federal rules. Accurate coding ensures proper reimbursement, tracks public health data accurately, and maintains a clean clinical record for the patient.
Clinical Definition and Psychiatric Criteria
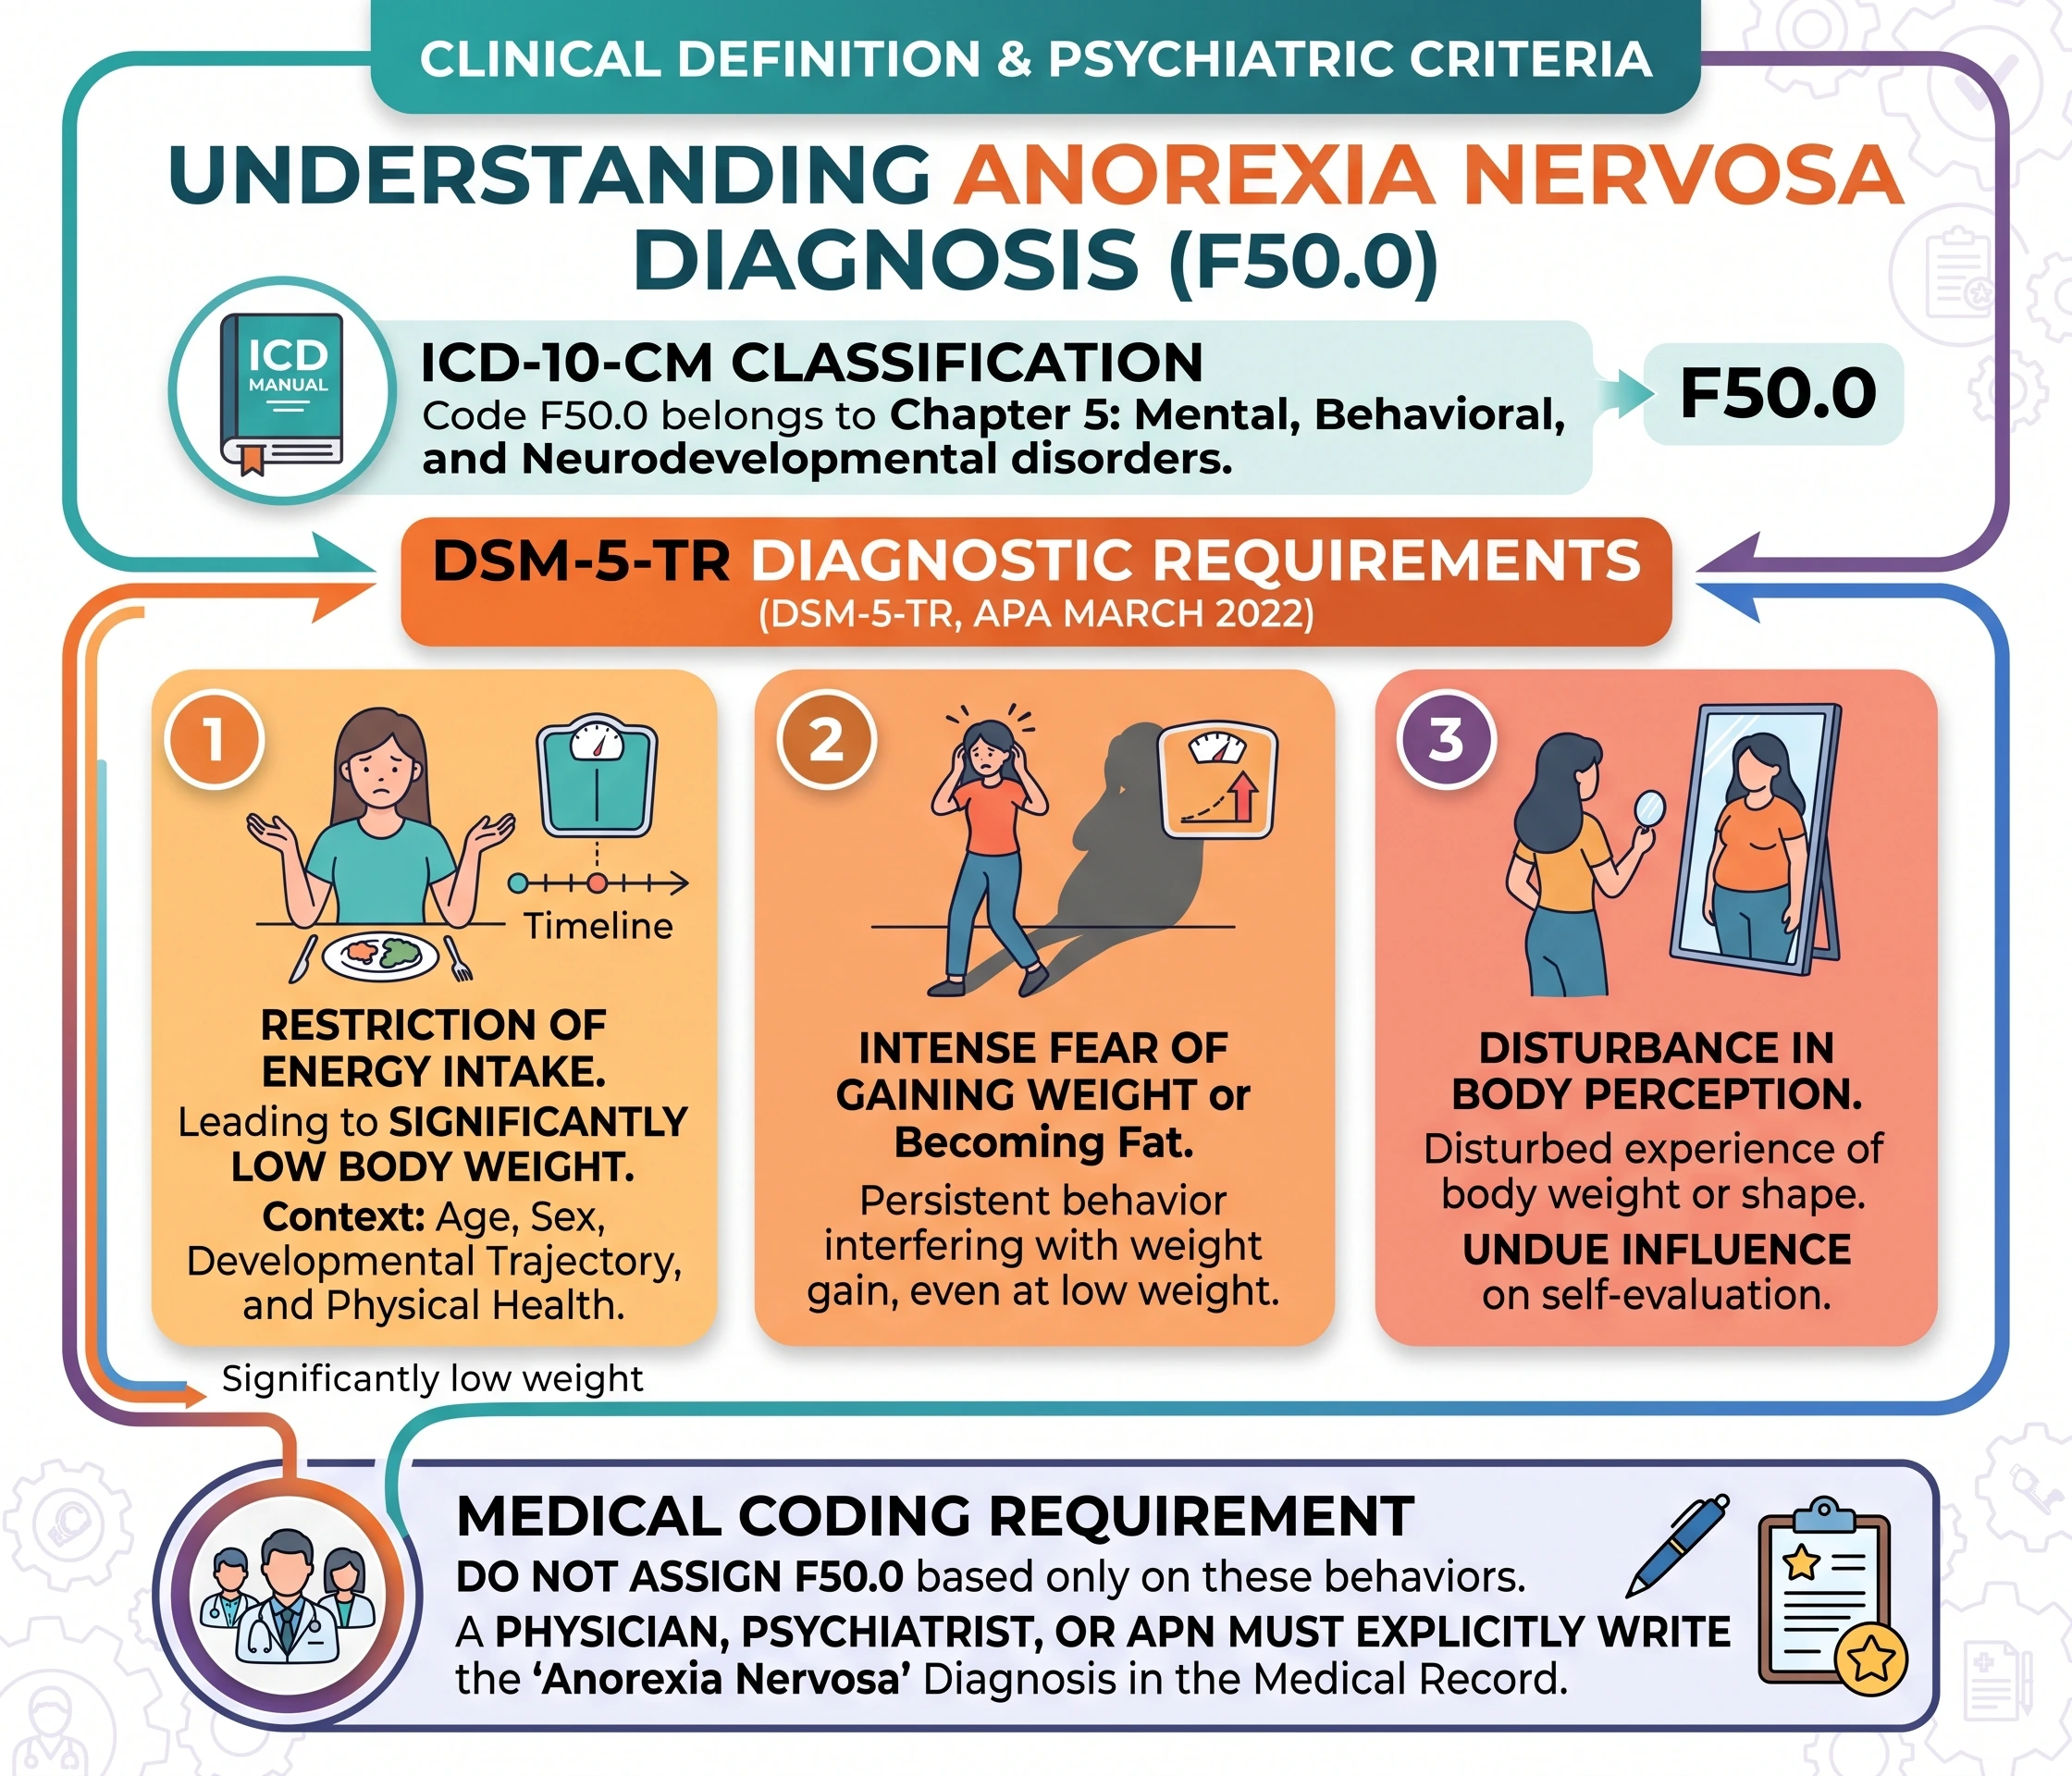
Under the ICD-10-CM manual, F50.0 falls within Chapter 5, which covers Mental, Behavioral, and Neurodevelopmental disorders. To assign a code from the F50.0 family, the clinical documentation must align with accepted psychiatric standards. Most healthcare providers use the diagnostic criteria outlined in the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR), published by the American Psychiatric Association in March 2022.
Diagnostic Requirements Under DSM-5-TR
The DSM-5-TR requires three specific behaviors for an anorexia nervosa diagnosis. First, the patient must restrict energy intake relative to their physical requirements. This restriction must lead to a significantly low body weight in the context of the patient’s age, sex, developmental trajectory, and physical health.
Second, the patient must exhibit an intense fear of gaining weight or becoming fat. This condition also applies if the patient engages in persistent behavior that interferes with weight gain, even when they are already at a significantly low weight.
Third, there must be a disturbance in the way the patient perceives their body weight or shape.
Medical coders cannot diagnose patients based on these behaviors alone. They must wait for the attending physician, psychiatrist, or advanced practice nurse to explicitly write the diagnosis of anorexia nervosa into the medical record before assigning the F50.0 code.
ICD-10 Coding Guidelines for the F50.0 Diagnosis Code
F50.0 is a category heading. Medical billers cannot submit F50.0 alone as a valid diagnosis on an insurance claim form. The Centers for Medicare & Medicaid Services (CMS) 2024 ICD-10-CM Official Guidelines require coding to the highest level of specificity. For anorexia nervosa, this requires a five-character code. Submitting a four-character code results in an immediate claim denial from clearinghouses and insurance payers.
The F50.0 Subcategories
The ICD-10-CM manual divides the F50.0 category into three distinct billable codes based on the patient’s specific behaviors.
|
Diagnosis Code |
Description |
Clinical Indicators Required for Billing |
|
F50.00 |
Anorexia nervosa, unspecified |
The provider documented anorexia nervosa but did not specify the subtype. |
|
F50.01 |
Anorexia nervosa, restricting type |
The provider documented weight loss achieved primarily through dieting, fasting, or excessive exercise. |
|
F50.02 |
Anorexia nervosa, binge eating/purging type |
The provider documented episodes of binge eating followed by self-induced vomiting or the misuse of laxatives, diuretics, or enemas. |
Coders must default to F50.00 if the provider simply writes “anorexia nervosa” in the chart. Relying on unspecified codes often triggers commercial insurance audits. Many payers require clinical clarification before reimbursing claims containing unspecified mental health diagnoses, extending the revenue cycle by weeks or months.
Mandatory Secondary Codes and Documentation
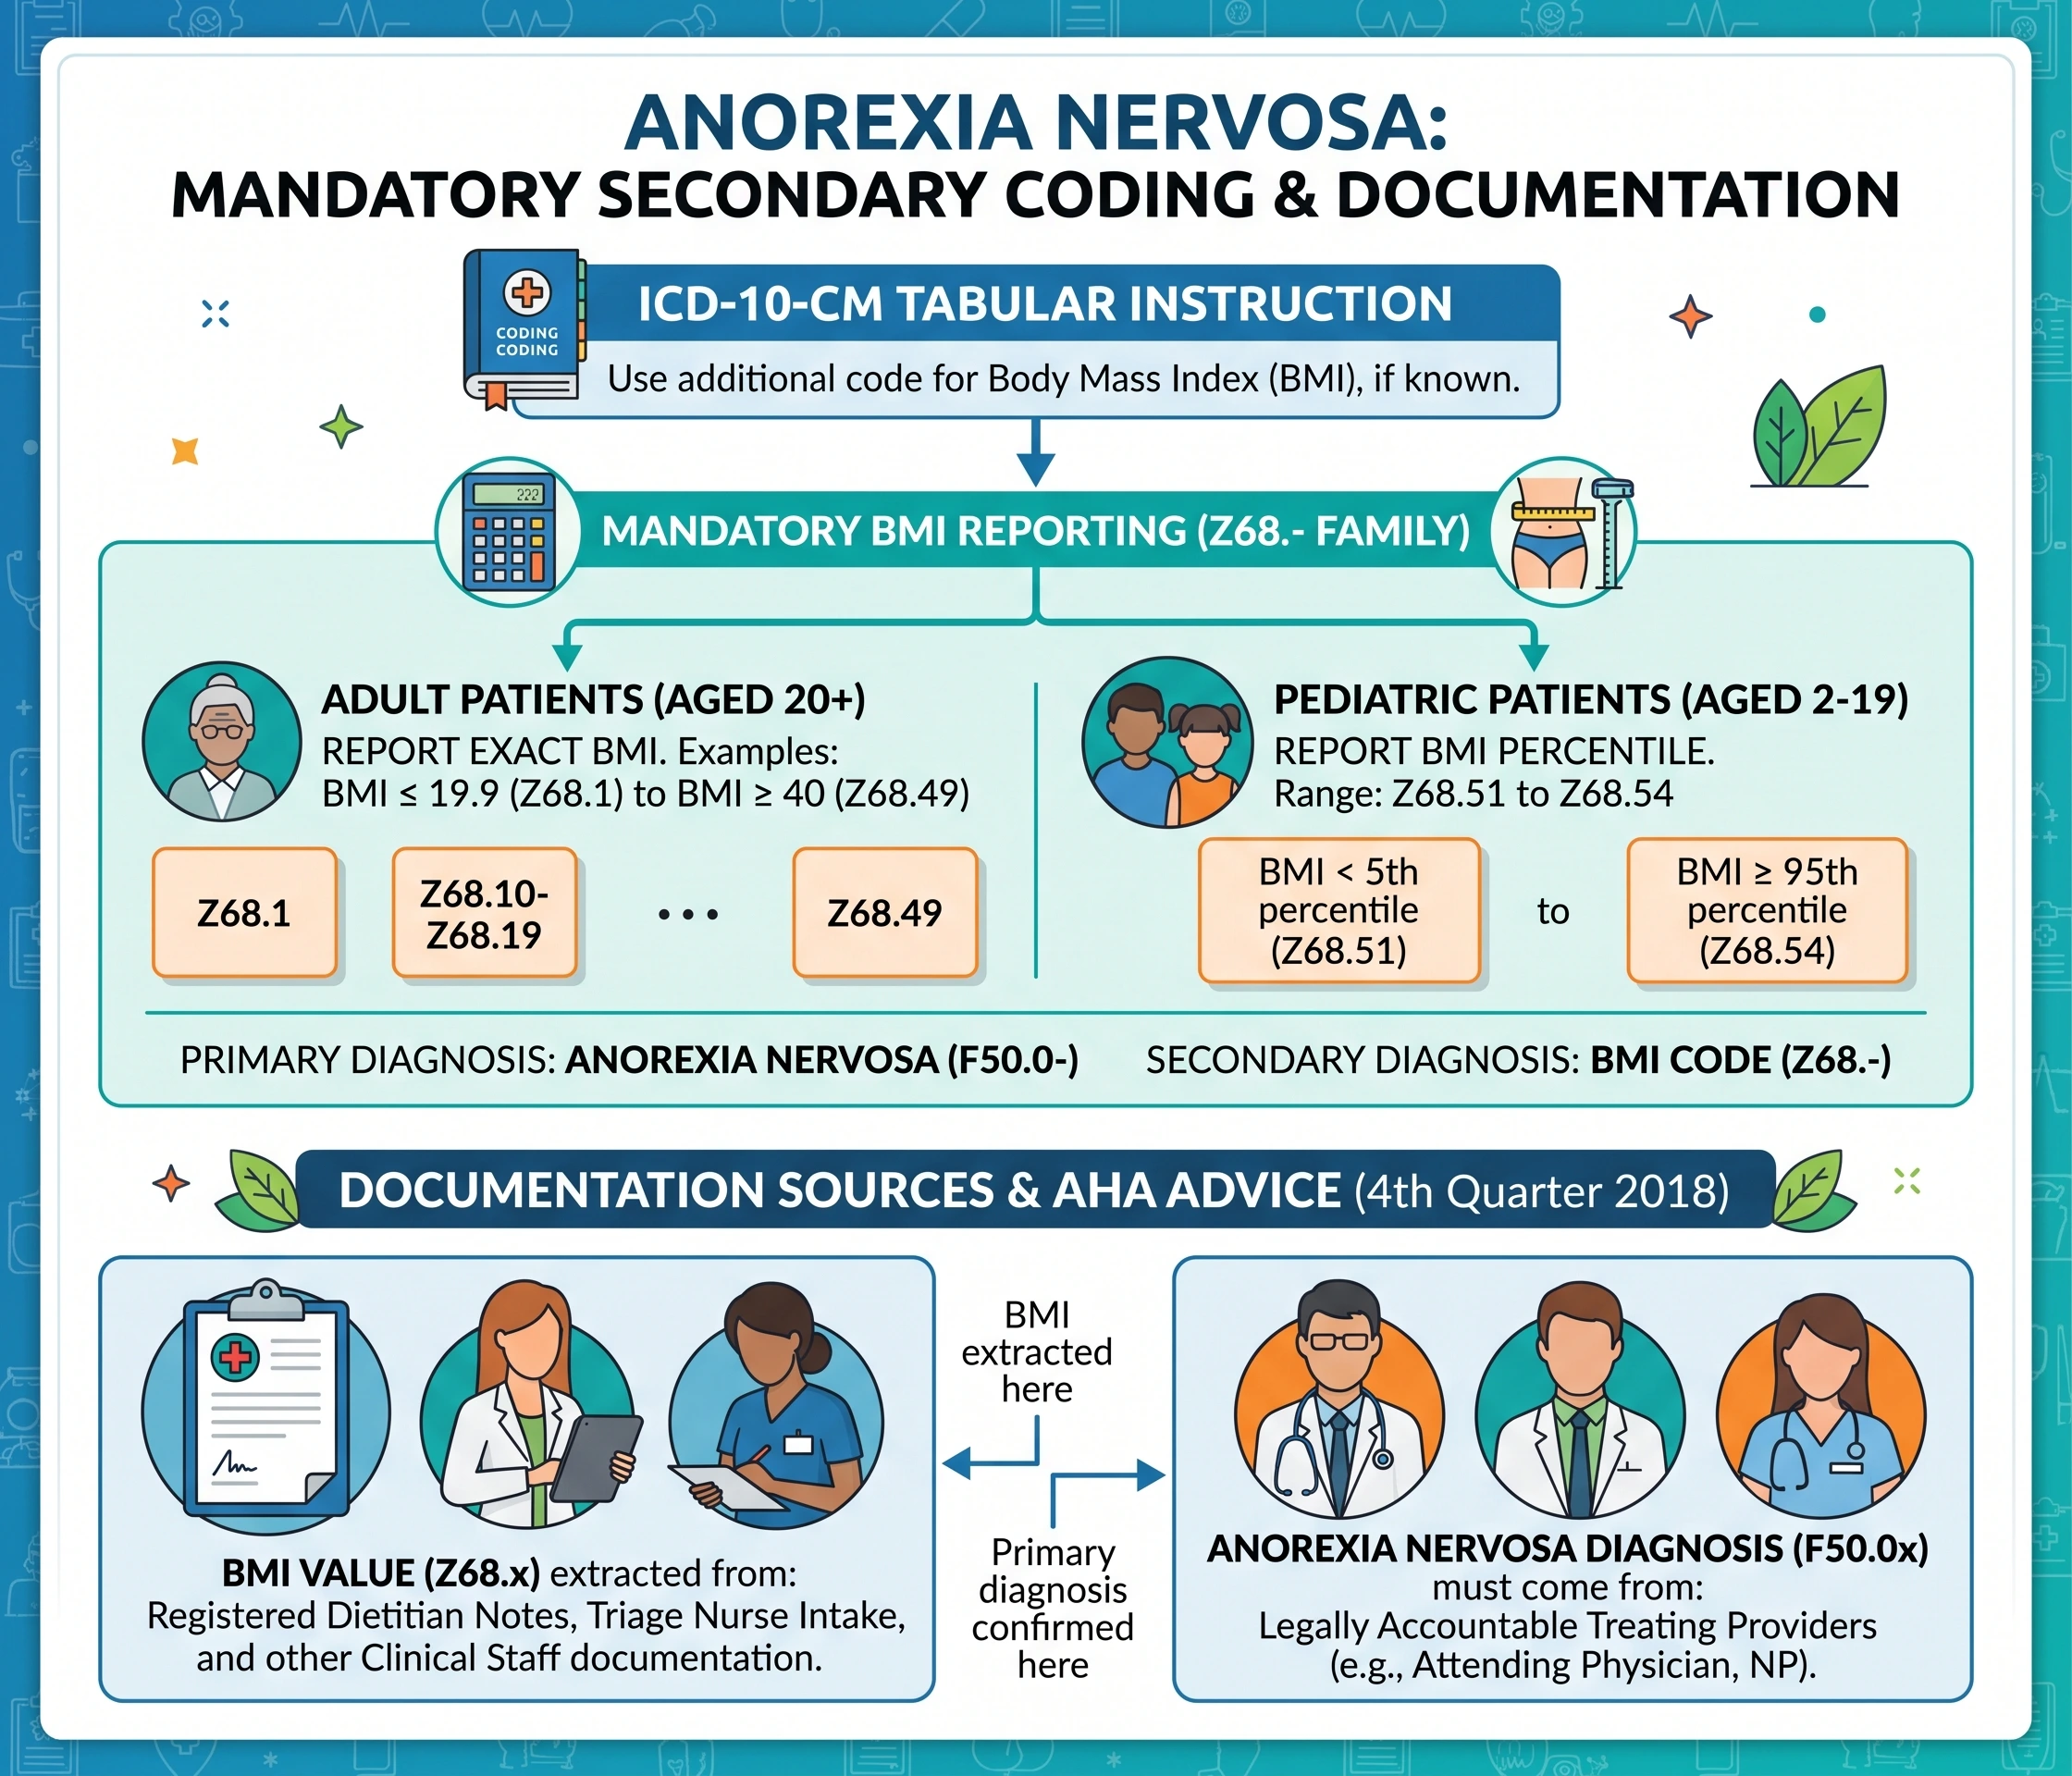
When coding for anorexia nervosa, the primary diagnosis code rarely stands alone. The tabular list in the ICD-10-CM manual provides a direct instruction under the F50.0 category: “Use additional code for Body Mass Index (BMI), if known.”
Body Mass Index (BMI) Reporting
This instruction mandates the use of the Z68.- code family. Medical coders must locate the patient’s exact BMI in the clinical notes and append the corresponding Z68 code as a secondary diagnosis. For adults aged 20 and older, the codes range from Z68.1 (BMI 19.9 or less) to Z68.49 (BMI 40 or greater). For pediatric patients aged 2 to 19, coders use BMI percentile codes ranging from Z68.51 (BMI less than 5th percentile) to Z68.54 (BMI greater than or equal to 95th percentile).
The American Hospital Association (AHA) publishes official coding advice regarding this requirement. According to the AHA Coding Clinic for ICD-10-CM/PCS (Fourth Quarter 2018), medical coders can extract the BMI value from documentation recorded by clinical staff other than the patient’s primary provider. A coder can use a registered dietitian’s note or a triage nurse’s intake form to find the BMI and assign the Z68 code. The primary diagnosis of F50.01 or F50.02 must still come directly from the legally accountable treating provider.
Excludes1 Notes and Coding Conflicts
The ICD-10-CM system uses Excludes notes to prevent contradictory coding. An Excludes1 note means “not coded here.” It indicates that the two conditions cannot occur together, and billers cannot submit both codes on the same claim for the same encounter.
The F50.0 category carries a strict Excludes1 note. Medical coders cannot bill F50.0 alongside the following codes:
- R63.0 (Anorexia, unspecified)
- R63.4 (Abnormal weight loss)
- F50.8 (Other eating disorders)
If a physician diagnoses a patient with anorexia nervosa (F50.01) and also notes “abnormal weight loss” (R63.4) in the physical exam, the coder must only report F50.01. The weight loss is inherently part of the F50.01 disease process. Billing both codes constitutes unbundling, which violates federal billing regulations.
Distinguishing Psychiatric F50.0 from Physiological R63.0
The distinction between F50.0 and R63.0 causes frequent confusion among entry-level medical coders. R63.0 describes a general, physiological loss of appetite. This physical symptom occurs with many medical illnesses, such as influenza, gastrointestinal infections, or cancer.
F50.0 describes a psychiatric eating disorder. If the physician documents “anorexia” without the word “nervosa,” the coder must review the chart. If the clinical context indicates a temporary loss of appetite due to a medical condition like chemotherapy treatment, R63.0 applies. If the context points to a psychiatric eating disorder but lacks the specific word “nervosa,” the coder must query the provider for written clarification before assigning F50.00.
Sequencing Rules for Inpatient and Outpatient Claims
Patients with F50.0 diagnoses frequently suffer from severe physical complications. When a patient has both anorexia nervosa and an acute physical condition, medical coders must follow specific sequencing rules determined by the setting of care.
In the outpatient setting, coders follow the first-listed diagnosis rules. The primary code is the main reason for the visit. If the patient presents to a psychiatric clinic specifically for eating disorder therapy, F50.01 is listed first.
In the inpatient hospital setting, coders follow the Uniform Hospital Discharge Data Set (UHDDS). The UHDDS defines the principal diagnosis as the condition established after study to be chiefly responsible for occasioning the admission of the patient to the hospital for care.
If a patient arrives at the emergency department in cardiac arrest due to an extreme electrolyte imbalance caused by the binge eating/purging type of anorexia nervosa, the sequencing changes. The physician admits the patient to the intensive care unit to stabilize the heart. In this scenario, the cardiac condition or the severe electrolyte imbalance (E87.8) serves as the principal diagnosis. The anorexia nervosa (F50.02) and the exact BMI (Z68.-) are reported as secondary diagnoses.
Severe Malnutrition and OIG Audits
Severe protein-calorie malnutrition (E43) is common among patients admitted to inpatient eating disorder programs. Over the past three years, the Department of Health and Human Services Office of Inspector General (OIG) has increased audits on malnutrition coding. Code E43 significantly increases hospital reimbursement rates.
When an auditor sees E43 paired with an F50.0 diagnosis, they look for specific clinical indicators in the chart. The physician must document muscle wasting, subcutaneous fat loss, or specific laboratory values to justify the severe malnutrition code. Coders cannot assume severe malnutrition based solely on a low BMI or an F50.0 diagnosis.
Documentation Requirements for Healthcare Providers
Medical billers and coders rely entirely on the exact words written by the healthcare provider. To ensure clean claims and accurate data abstraction, providers must document the F50.0 diagnosis with deliberate specificity.
A standard clinical note for an eating disorder evaluation should include the specific DSM-5-TR subtype. Providers must write “restricting type” or “binge-eating/purging type” rather than just “anorexia.” The note must include the patient’s current height, weight, and calculated BMI to satisfy the Z68 secondary code requirement.
Providers should also explicitly link any associated physical manifestations to the eating disorder. If a patient experiences amenorrhea (N91.2), bradycardia (R00.1), or osteoporosis (M81.0) as a direct result of the anorexia nervosa, the physician must state the causal relationship in the assessment and plan. Coders are not permitted to link separate conditions together without direct provider confirmation. By documenting these links, providers give coders the authority to paint a complete clinical picture on the final medical claim.
Summary of F50.0 Coding Protocols
Assigning the F50.0 diagnosis code requires strict attention to ICD-10-CM guidelines and provider documentation. Medical billers must verify that the F50.0 code extends to five characters to specify the restricting or binge-eating/purging subtype. Claims must include a secondary Z68 code to report the patient’s body mass index, which can be extracted from nursing or dietitian notes. Coders must cross-reference all Excludes1 notes, particularly regarding general anorexia (R63.0) and abnormal weight loss (R63.4), to prevent unbundling on the claim form. Associated physical conditions such as severe malnutrition or electrolyte imbalances require explicit physician documentation linking them to the psychiatric diagnosis to withstand payer audits.