



Physicians and mental health professionals assign the alphanumeric ICD-10-CM code F32.2 when a patient suffers from a single, severe episode of major depressive disorder, explicitly lacking psychotic symptoms. Medical billers rely on this precise identifier to process claims through insurance networks and secure reimbursement.
Converting a clinical visit into this exact diagnostic code demands strict compliance with rules established by the World Health Organization (WHO) and the Centers for Medicare and Medicaid Services (CMS). Providers cannot simply use F32.2 for generalized depression. The chart notes must clearly validate the frequency, the exact severity level, and the absence of delusions or hallucinations.
Diagnostic criteria and clinical thresholds
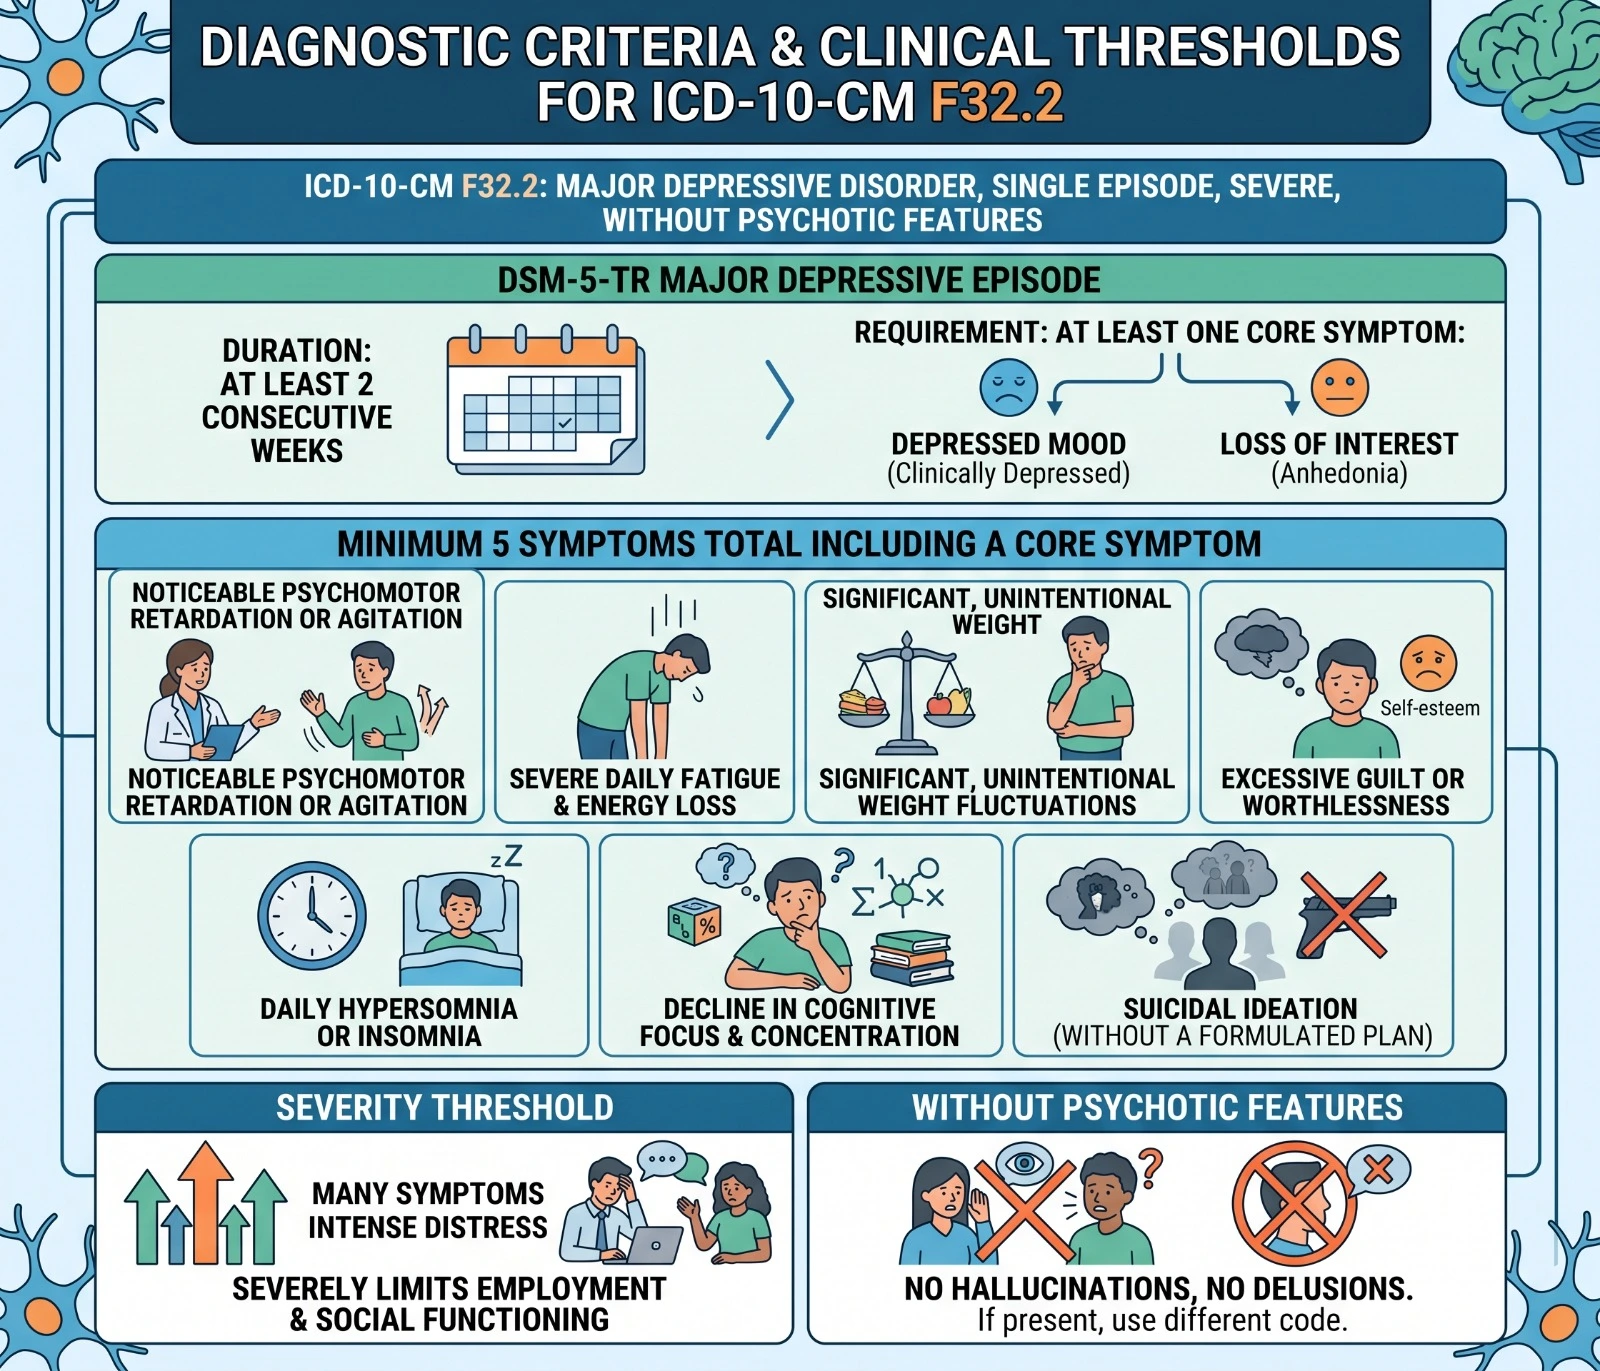
Official ICD-10-CM reporting guidelines restrict F32.2 to patients enduring their first recorded bout of major depression. This occurrence must also meet the clinical threshold for a "severe" classification.
The Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR) defines the exact clinical presentation corresponding to this diagnostic code. Patients must endure at least five specific symptoms simultaneously over a consecutive two-week span. A depressed mood or clinical anhedonia (the loss of ability to feel pleasure) must account for at least one of these core symptoms.
The recognized clinical indicators include:
- Noticeable psychomotor retardation or agitation visible to clinicians or family members.
- Severe daily fatigue or depleted physical energy.
- Significant, unintentional fluctuations in body weight.
- Excessive, inappropriate guilt or persistent feelings of worthlessness.
- Daily struggles with hypersomnia or insomnia.
- A measurable decline in cognitive focus and concentration.
- Suicidal ideation or recurring thoughts of death, excluding those with a formulated plan.
To reach the "severe" threshold mandatory for F32.2, the symptom count usually exceeds the five-symptom minimum. These issues must cause intense distress and severely restrict the patient's capacity to maintain employment or social relationships.
Furthermore, the code’s nomenclature specifies "without psychotic features." If auditory hallucinations, visual hallucinations, or delusions accompany the severe depression, the coder must select a different alphanumeric category entirely.
Differentiating F32.2 from related ICD-10 categories
Claim denials frequently happen when clinical narratives lack the detail necessary to isolate F32.2 from adjacent categories in the F32 and F33 families.
The table below outlines the primary differences between this diagnosis and its most common coding alternatives.
| ICD-10 Code | Code Description | Key Differentiating Factor |
|---|---|---|
| F32.0 | Major depressive disorder, single episode, mild | Minimal symptoms beyond the baseline diagnostic requirement; slight functional disruption. |
| F32.1 | Major depressive disorder, single episode, moderate | Symptom burden and daily impairment sit midway between the mild and severe classifications. |
| F32.2 | Major depressive disorder, single episode, severe without psychotic features | Extensive symptom list, debilitating impairment, absence of psychotic symptoms. |
| F32.3 | Major depressive disorder, single episode, severe with psychotic features | Active mood-congruent or mood-incongruent delusions or hallucinations. |
| F33.2 | Major depressive disorder, recurrent, severe without psychotic features | Medical records confirm a past major depressive episode. |
Distinguishing a single occurrence from a recurrent pattern requires detailed historical chart audits. If a physician identifies a past major depressive episode in the patient's medical file even an episode that resolved a decade ago the current severe manifestation maps to F33.2, never F32.2.
Validating severity with objective screening tools
Insurance companies consistently look for quantifiable data to justify billing for high-severity diagnostic codes. A physician’s subjective summary often falls short during an external audit. Integrating validated psychiatric rating scales directly into the clinical narrative supplies concrete proof of the patient's condition.
Clinics frequently deploy the Patient Health Questionnaire (PHQ-9) as a standard self-report instrument. It quantifies nine depression criteria on a numerical scale from 0 to 27. Clinical protocols published by the American Psychological Association (APA) indicate that scores landing between 20 and 27 align with severe major depression.
Clinicians also utilize the clinician-scored Hamilton Depression Rating Scale (HAM-D) and the Beck Depression Inventory (BDI-II). Documenting the specific questionnaire title and the final numerical score within the chart provides direct structural support for billing F32.2.
Chart documentation standards for coders
Medical coders operate under a strict rule: they cannot extract diagnoses from assumptions. When a provider scribbles "severe depression," coders cannot legally translate that directly to F32.2. In the ICD-10-CM alphabetical index, the isolated word "depression" maps to the unspecified code F32.A.
Accurate assignment of F32.2 requires the attending provider to document four distinct clinical facts:
- The presence of major depressive disorder.
- Confirmation that this is the patient's first (single) episode.
- A specific severity level of "severe".
- A clear notation that psychotic features are not present.
Many billing departments train providers using the MEAT framework (Monitor, Evaluate, Assess, Treat) to capture risk-adjustment data accurately.
Monitoring tracks the physical and mental progression of the illness. Evaluating requires the administration of tests, like the PHQ-9. Assessing demands a definitive provider statement regarding the current diagnosis and functional limitations. Treating covers the exact pharmacological or therapeutic interventions prescribed.
A fully compliant chart entry might state: "The patient presents with major depressive disorder, single episode. The severity is currently severe, verified by a PHQ-9 score of 24, active suicidal thoughts without a plan, and an inability to perform basic hygiene. No psychotic symptoms are present. Treatment plan: Start Sertraline 50mg daily and initiate an immediate referral for intensive outpatient psychotherapy."
Managing Excludes1 and Excludes2 instructions
The ICD-10-CM tabular list dictates strict rules regarding concurrent conditions. Medical coders must review the Excludes1 and Excludes2 directives attached to the F32 block to stop automatic claim rejections.
An Excludes1 directive translates clinically to "not coded here." It means the two identified conditions are mutually exclusive and cannot appear on the same billing claim. The F32 block carries a permanent Excludes1 restriction for bipolar disorders. If a patient's chart contains any historical reference to hypomanic or manic episodes, coders must abandon F32.2 entirely and select from the bipolar disorder block (F31.-).
Additional Excludes1 restrictions for this category include:
- Recurrent depressive disorder categories (F33.-)
- Manic episode classifications (F30.-)
Conversely, an Excludes2 directive means "not included here." This instruction signals that while the secondary condition is not part of the primary F32 diagnosis, a patient can suffer from both simultaneously. Coders can place both codes on the claim if the provider documents both. The F32 category lists an Excludes2 note for adjustment disorders (F43.2).
Medical billing and CPT code alignment
The F32.2 code explains the medical necessity of the visit. Current Procedural Terminology (CPT) codes define the actual service rendered. Clean claims require a logical medical relationship between these two code sets.
Psychiatric diagnostic evaluations utilize CPT 90791 for non-medical assessments and 90792 when medical services are included. Because this diagnosis involves severe impairment, providers frequently prescribe medications. Psychiatrists managing these prescriptions typically bill standard outpatient Evaluation and Management (E/M) codes, specifically 99213, 99214, or 99215.
The American Medical Association (AMA) E/M guidelines base coding levels on either total encounter time or Medical Decision Making (MDM). Prescription drug management automatically classifies as a moderate risk of morbidity. When a physician prescribes a medication for a severe psychiatric exacerbation and reviews prior records, the MDM calculation often supports billing a 99214 or 99215.
Psychologists and licensed clinical social workers bill therapy sessions based on the exact minutes spent with the patient:
- 90832 covers 30 minutes of clinical psychotherapy.
- 90834 covers 45 minutes of clinical psychotherapy.
- 90837 covers 60 minutes of clinical psychotherapy.
When a physician conducts an E/M service and provides psychotherapy in the same appointment, they use specific add-on codes (such as 90833 or 90836). The provider must document the exact time dedicated solely to therapy, keeping it entirely separate from the time used to calculate the E/M code.
Navigating compliance reviews and risk adjustment audits
The Centers for Medicare and Medicaid Services (CMS) and the Office of Inspector General (OIG) heavily audit behavioral health records to recover overpayments. F32.2 attracts specific audit scrutiny because "severe" clinical designations directly increase Hierarchical Condition Category (HCC) risk scores. Higher risk scores trigger larger capitated payments to insurance networks and health systems.
Auditors search for contradictions between the billed severity and the physician's written observations. If a clinic bills F32.2 but the progress notes describe a patient who maintains full-time employment, sleeps eight hours a night, and reports only minor low moods, the auditor will invalidate the code and issue a recoupment demand.
Healthcare facilities use routine internal audits to maintain compliance. When a chart labels a patient's depression as "severe" but the listed symptoms reflect a mild presentation, coders must issue a provider query before generating the claim. This query must neutrally ask the clinician to clarify the discrepancy in the medical record rather than prompting them to select a predetermined code.
Correct primary and secondary sequencing also prevents compliance failures. If a patient schedules a visit specifically to address their severe depression, F32.2 goes on the first line of the CMS-1500 form. If the primary reason for the visit is diabetes management, and the provider simply authorizes a psychiatric medication refill at the end of the appointment, the diabetes code takes the primary slot, pushing F32.2 to a secondary position.
Accurate, highly specific charting shields medical practices during federal audits. A descriptive clinical narrative that directly connects a patient's exact daily struggles to the official diagnostic criteria for severe major depressive disorder ensures appropriate reimbursement and maintains the integrity of public health databases.