



F32.0 Diagnosis Code: Symptoms, Billing, and Documentation Tips
The F32.0 diagnosis code specifies a mild, single episode of major depressive disorder. Medical billers, coders, and healthcare providers use this ICD-10-CM code to establish medical necessity for behavioral health services and prescription management. Accurate application of this code requires clear clinical documentation that differentiates a single mild episode from recurrent or more severe depressive disorders.
Clinical criteria for F32.0
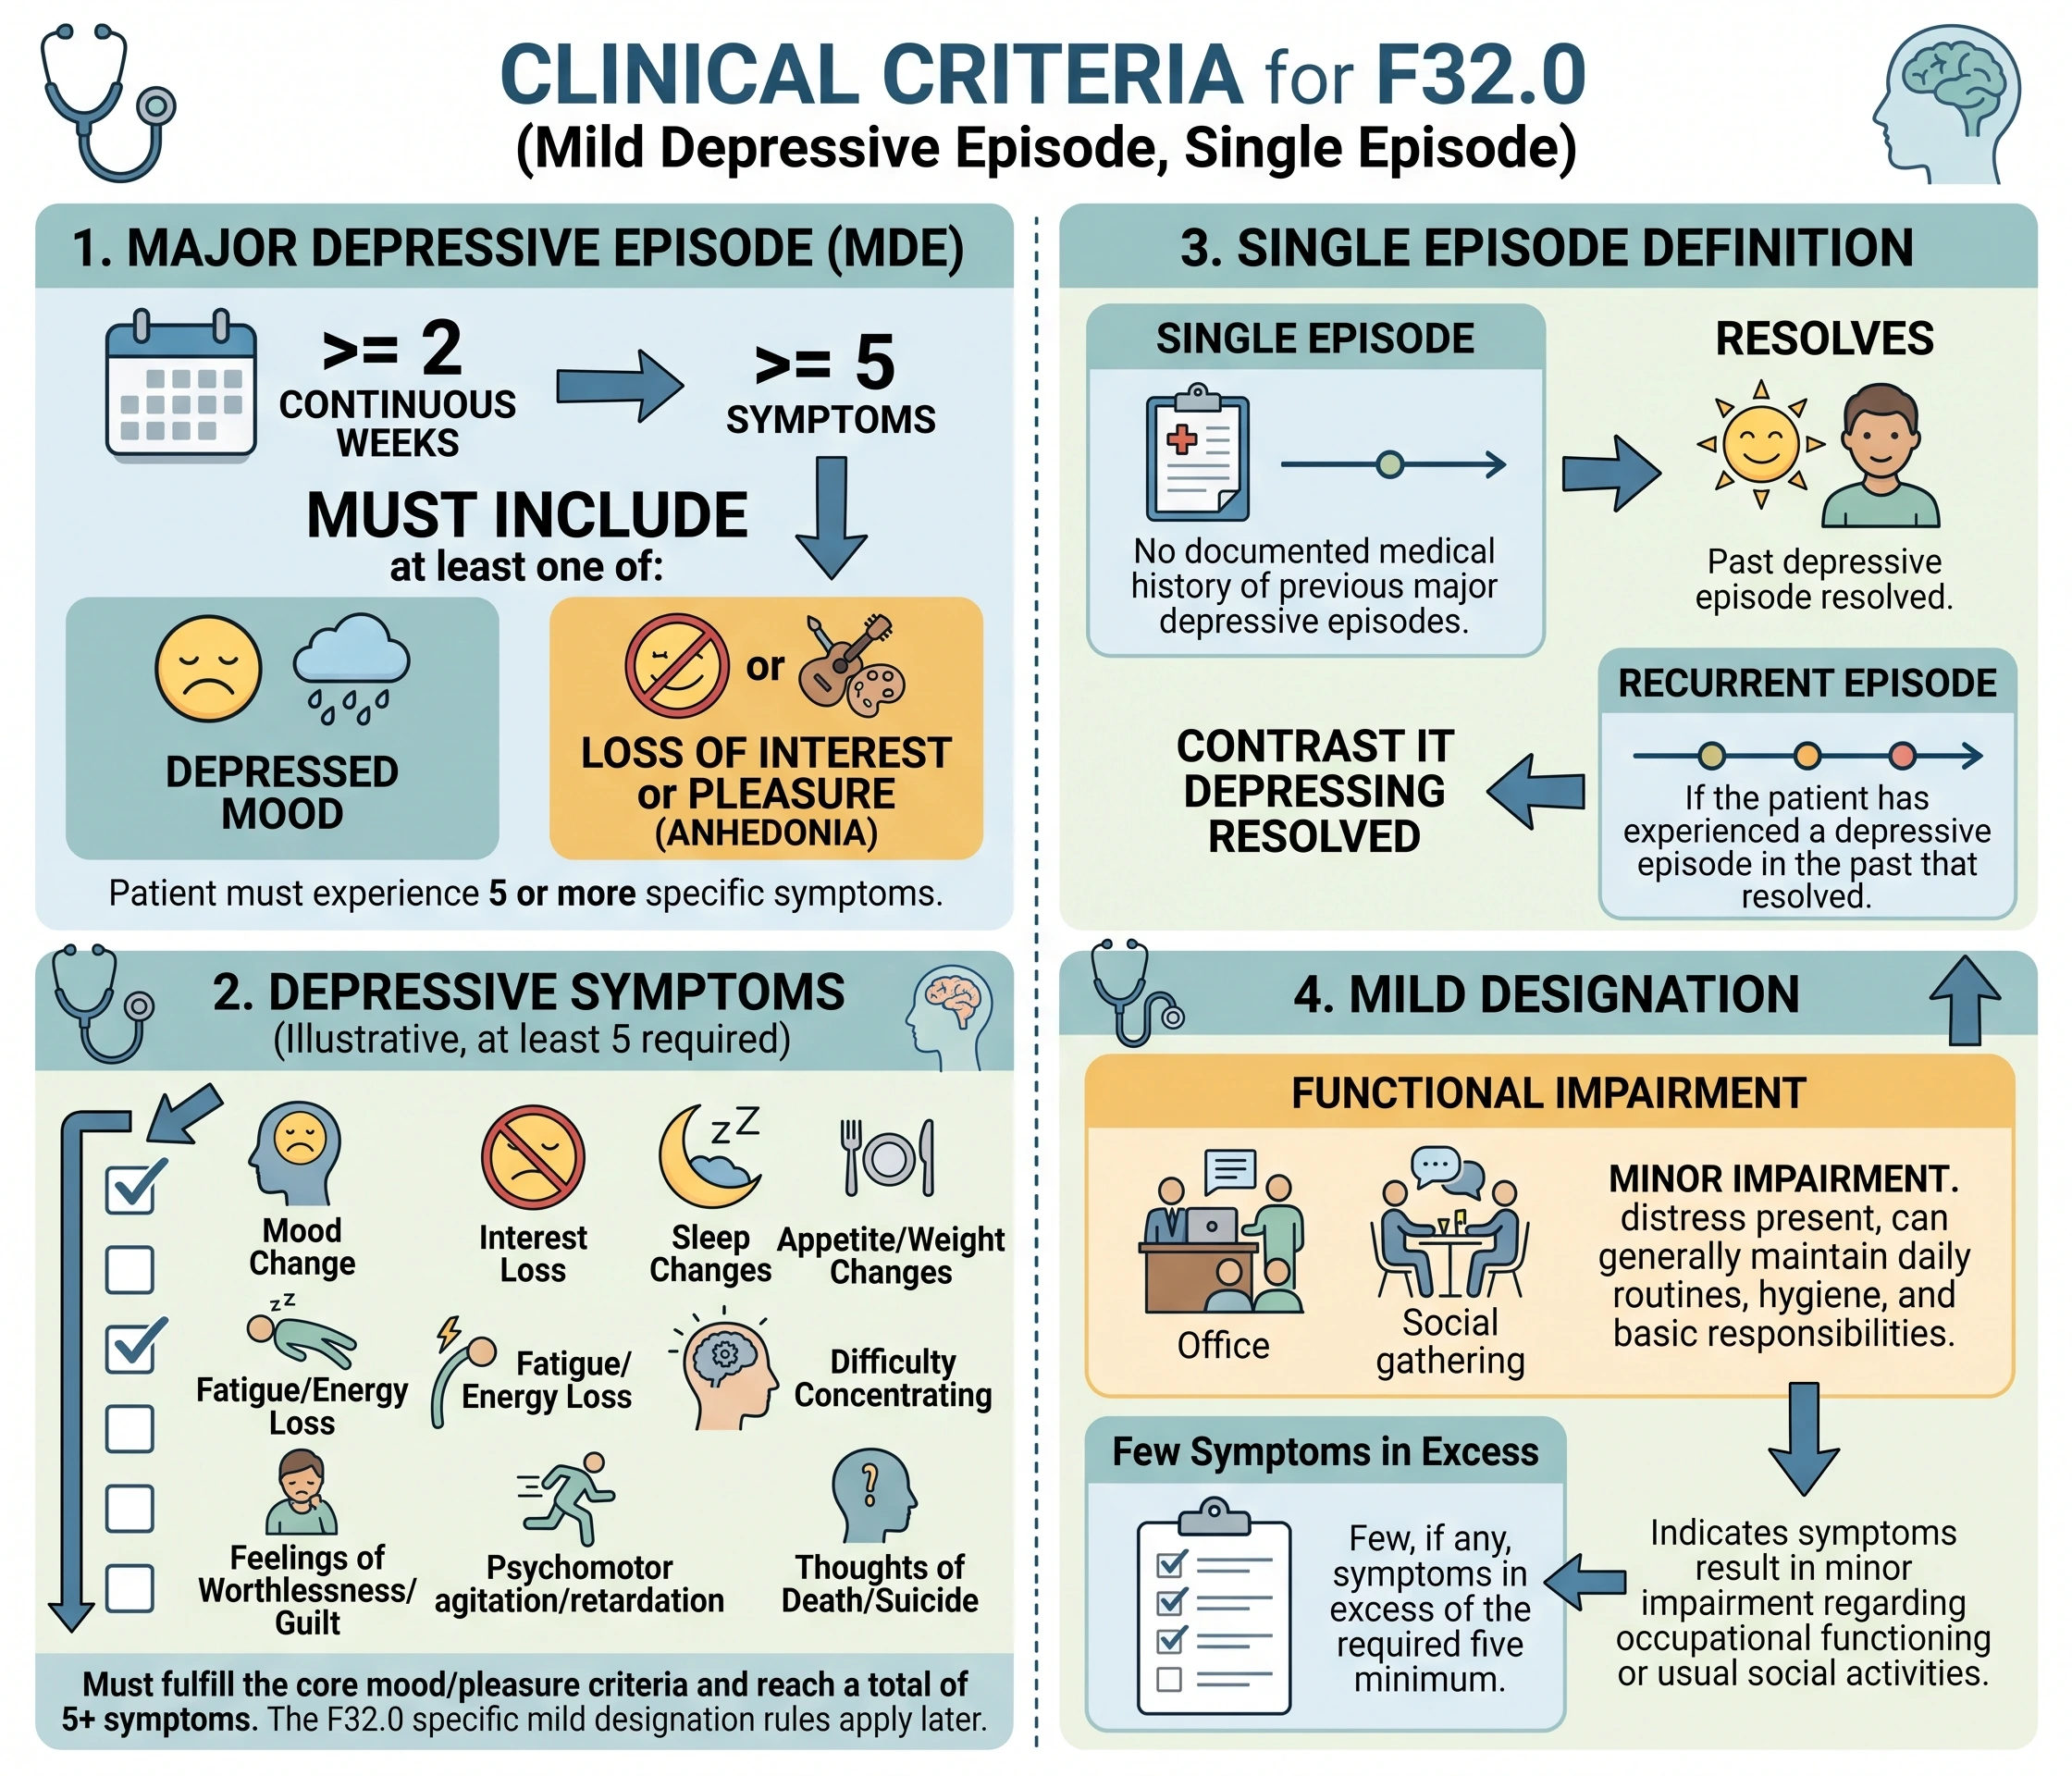
The diagnostic framework for F32.0 aligns with the criteria established by the American Psychiatric Association (APA) in the DSM-5-TR. A major depressive episode requires the patient to experience five or more specific symptoms during a continuous two-week period. At least one of these symptoms must be a depressed mood or a distinct loss of interest or pleasure in daily activities.
The phrase “single episode” means the patient has no documented medical history of previous major depressive episodes. If the patient has experienced a depressive episode in the past that resolved, the current episode classifies as recurrent.
The “mild” designation indicates that the symptoms result in minor impairment regarding occupational functioning or usual social activities. The patient experiences distress but can generally maintain their daily routines, hygiene, and basic responsibilities. They present with few, if any, symptoms in excess of the required five minimum diagnostic markers.
Recognizing F32.0 symptoms in clinical practice
Providers must document specific clinical symptoms to support the use of the F32.0 diagnosis code. The clinical notes should reflect a minimum two-week duration of presenting issues. Commonly documented symptoms include:
- Depressed mood for most of the day, nearly every day.
- Diminished interest or pleasure in almost all activities.
- Significant, unintended weight loss or weight gain.
- Insomnia or hypersomnia.
- Psychomotor agitation or physical retardation observable by others.
- Fatigue or daily loss of energy.
- Feelings of worthlessness or excessive, inappropriate guilt.
- Diminished ability to think, concentrate, or make decisions.
When a patient presents with exactly five of these symptoms and reports only minor interference with their work or school life, F32.0 is the appropriate diagnostic classification.
Documentation tips for the F32.0 diagnosis code
Auditors frequently review behavioral health claims to ensure the diagnosis code matches the provider’s clinical notes. When applying the F32.0 diagnosis code, documentation must explicitly state the severity level and the episode frequency. Writing “depression” or “feeling down” in a chart note does not meet ICD-10 coding compliance standards.
The medical record must confirm this is the patient’s first episode of depression. If the provider uncovers a history of major depressive disorder during the clinical interview, coders must bypass the F32 category and use the F33 category for recurrent episodes.
Clinical notes must also specify the severity as mild. If the provider documents “moderate” or “severe” symptoms, the billing department must use F32.1 or F32.2.
Utilizing assessment tools
Providers should use standardized assessment tools to quantify symptom severity and support the diagnosis. The Patient Health Questionnaire-9 (PHQ-9) serves as the primary screening tool in both primary care and psychiatric settings.
A PHQ-9 score between 5 and 9 correlates directly with mild depression. Including the specific numerical score and the date of the assessment in the clinical documentation provides measurable evidence to justify billing the F32.0 code. For pediatric patients, providers use the Patient Health Questionnaire for Adolescents (PHQ-A). A documented mild score on the PHQ-A supports an F32.0 diagnosis for patients aged 12 to 18.
Billing guidelines and exclusions
The ICD-10-CM manual contains specific inclusion and exclusion instructions for the F32 category. Medical billers must verify these clinical notes to prevent immediate claim denials from clearinghouses or insurance payers.
Coders must carefully review the Excludes1 notes. An Excludes1 note means “not coded here” and establishes that two conditions cannot be billed together on the same claim because they are mutually exclusive. F32.0 carries Excludes1 notes for:
- Bipolar disorder (F31.-)
- Manic episode (F30.-)
- Recurrent depressive disorder (F33.-)
If a patient’s medical history includes a previous manic or hypomanic episode, the diagnosis defaults to a bipolar classification, rendering F32.0 invalid.
An Excludes2 note indicates “not included here” but allows both codes to be billed simultaneously if the patient genuinely suffers from both conditions. The F32 category carries an Excludes2 note for adjustment disorder (F43.2). A patient can receive treatment for a mild single episode of depression while also suffering from a separate adjustment disorder.
Differentiating F32 codes
Selecting the correct code requires understanding the differences within the F32 and F33 coding blocks. Coding errors often occur when billers select a code based on a keyword search rather than reading the full description.
|
ICD-10 Code |
Clinical Description |
Episode History |
Severity Level |
|
F32.0 |
Major depressive disorder, single episode, mild |
First episode |
Mild (minor impairment) |
|
F32.1 |
Major depressive disorder, single episode, moderate |
First episode |
Moderate (noticeable impairment) |
|
F32.9 |
Major depressive disorder, single episode, unspecified |
First episode |
Not documented |
|
F33.0 |
Major depressive disorder, recurrent, mild |
Two or more episodes |
Mild (minor impairment) |
Common reasons for F32.0 claim denials
Insurance payers deny behavioral health claims when the diagnosis code contradicts the provided service or conflicts with the patient’s established medical history.
One frequent billing error involves using F32.0 for a patient receiving long-term treatment for depression. If a patient is currently stable on a daily antidepressant and attends a standard medication management appointment, the condition is usually in remission. The accurate code in this scenario is F32.4 (Major depressive disorder, single episode, in full remission) or F32.5 (Major depressive disorder, single episode, in partial remission).
Another common denial trigger is the overuse of unspecified codes. Many providers default to F32.9 (Major depressive disorder, single episode, unspecified) out of habit. Commercial payers and Medicare increasingly reject unspecified codes when the clinical notes contain enough information to determine a specific severity level. Transitioning a practice from F32.9 to F32.0 directly reduces denial rates when the medical record explicitly supports a mild severity level.
Linking F32.0 to specific treatment modalities
The F32.0 diagnosis code establishes the medical necessity for specific clinical interventions and treatments.
When a provider bills for psychotherapy, such as CPT code 90834 (Psychotherapy, 45 minutes), linking it to F32.0 demonstrates that the therapy targets a recognized, diagnosable condition. The American Psychological Association identifies cognitive behavioral therapy (CBT) and interpersonal therapy (IPT) as primary evidence-based treatments for mild depression. The clinical documentation must reflect these therapeutic approaches when billed alongside F32.0.
Pharmacotherapy is also a standard intervention. Primary care physicians manage the vast majority of mild depression cases. According to 2022 data from the National Institute of Mental Health (NIMH), primary care settings account for most antidepressant prescriptions in the United States. An evaluation and management (E/M) code, such as 99213 or 99214, paired with F32.0, explains why the physician spent the appointment assessing the patient’s mood, reviewing screening scores, and discussing medication side effects.
Telehealth billing considerations
The delivery of behavioral health services via telehealth expanded rapidly over the past several years. When billing F32.0 for a virtual psychiatric or primary care visit, coders must append the correct place of service (POS) code and modifiers.
For Medicare claims, the Centers for Medicare & Medicaid Services (CMS) requires POS 10 for telehealth provided in the patient’s home and POS 2 (Telehealth Provided Other than in Patient’s Home) if the patient is located elsewhere. The documentation must state the specific modality used (audio-visual or audio-only). Applying modifier 95 to the CPT code indicates synchronous telemedicine service rendered via a real-time interactive audio and video telecommunications system. Using F32.0 without the correct POS code or modifier for a virtual visit results in an automatic system denial.
Impact on patient care and history
The diagnosis codes assigned to a patient’s medical record follow them indefinitely throughout the healthcare system. Coding accuracy affects more than immediate financial reimbursement.
If a biller inaccurately assigns a severe depression code (F32.2) to a patient experiencing mild symptoms (F32.0), it permanently alters the patient’s psychiatric history. This inaccuracy can cause complications during future life insurance applications, occupational health screenings, and military enlistment physicals. Precise use of F32.0 ensures the patient’s permanent medical record reflects their actual clinical presentation.
Auditing teams working for insurance companies conduct regular chart reviews to verify code accuracy. If an auditor reviews a chart billed with F32.0 and finds documentation describing “severe, debilitating symptoms with suicidal ideation,” they will flag the claim for a coding mismatch. The provider will have to amend the chart, and the practice may face financial clawbacks for incorrect billing.
The Centers for Disease Control and Prevention (CDC) reported in 2023 that approximately 29 percent of adults in the United States receive a formal depression diagnosis at some point during their lifetime. Accurately categorizing and tracking these cases relies entirely on strict adherence to ICD-10-CM coding guidelines. The F32.0 diagnosis code fulfills a specific clinical function by identifying first-time, mildly disruptive depressive episodes. Healthcare facilities that train their clinical and billing staff to document episode frequency, quantify symptom severity using standardized scales, and apply accurate coding guidelines reduce their claim denial rates while maintaining precise medical records.