



Understanding 99204 CPT Code: Description, Time & Requirements
The 99204 CPT code reports an office or other outpatient evaluation and management (E/M) visit for a new patient. Code selection can rest on moderate medical decision making (MDM) or at least 45 minutes of qualifying practitioner time on the encounter date. These are alternative pathways. A visit selected through MDM does not also have to meet the time threshold.
Accurate selection therefore requires three checks: whether the patient qualifies as new, which selection method supports the service, and whether the record explains the work performed.
What the 99204 CPT code describes
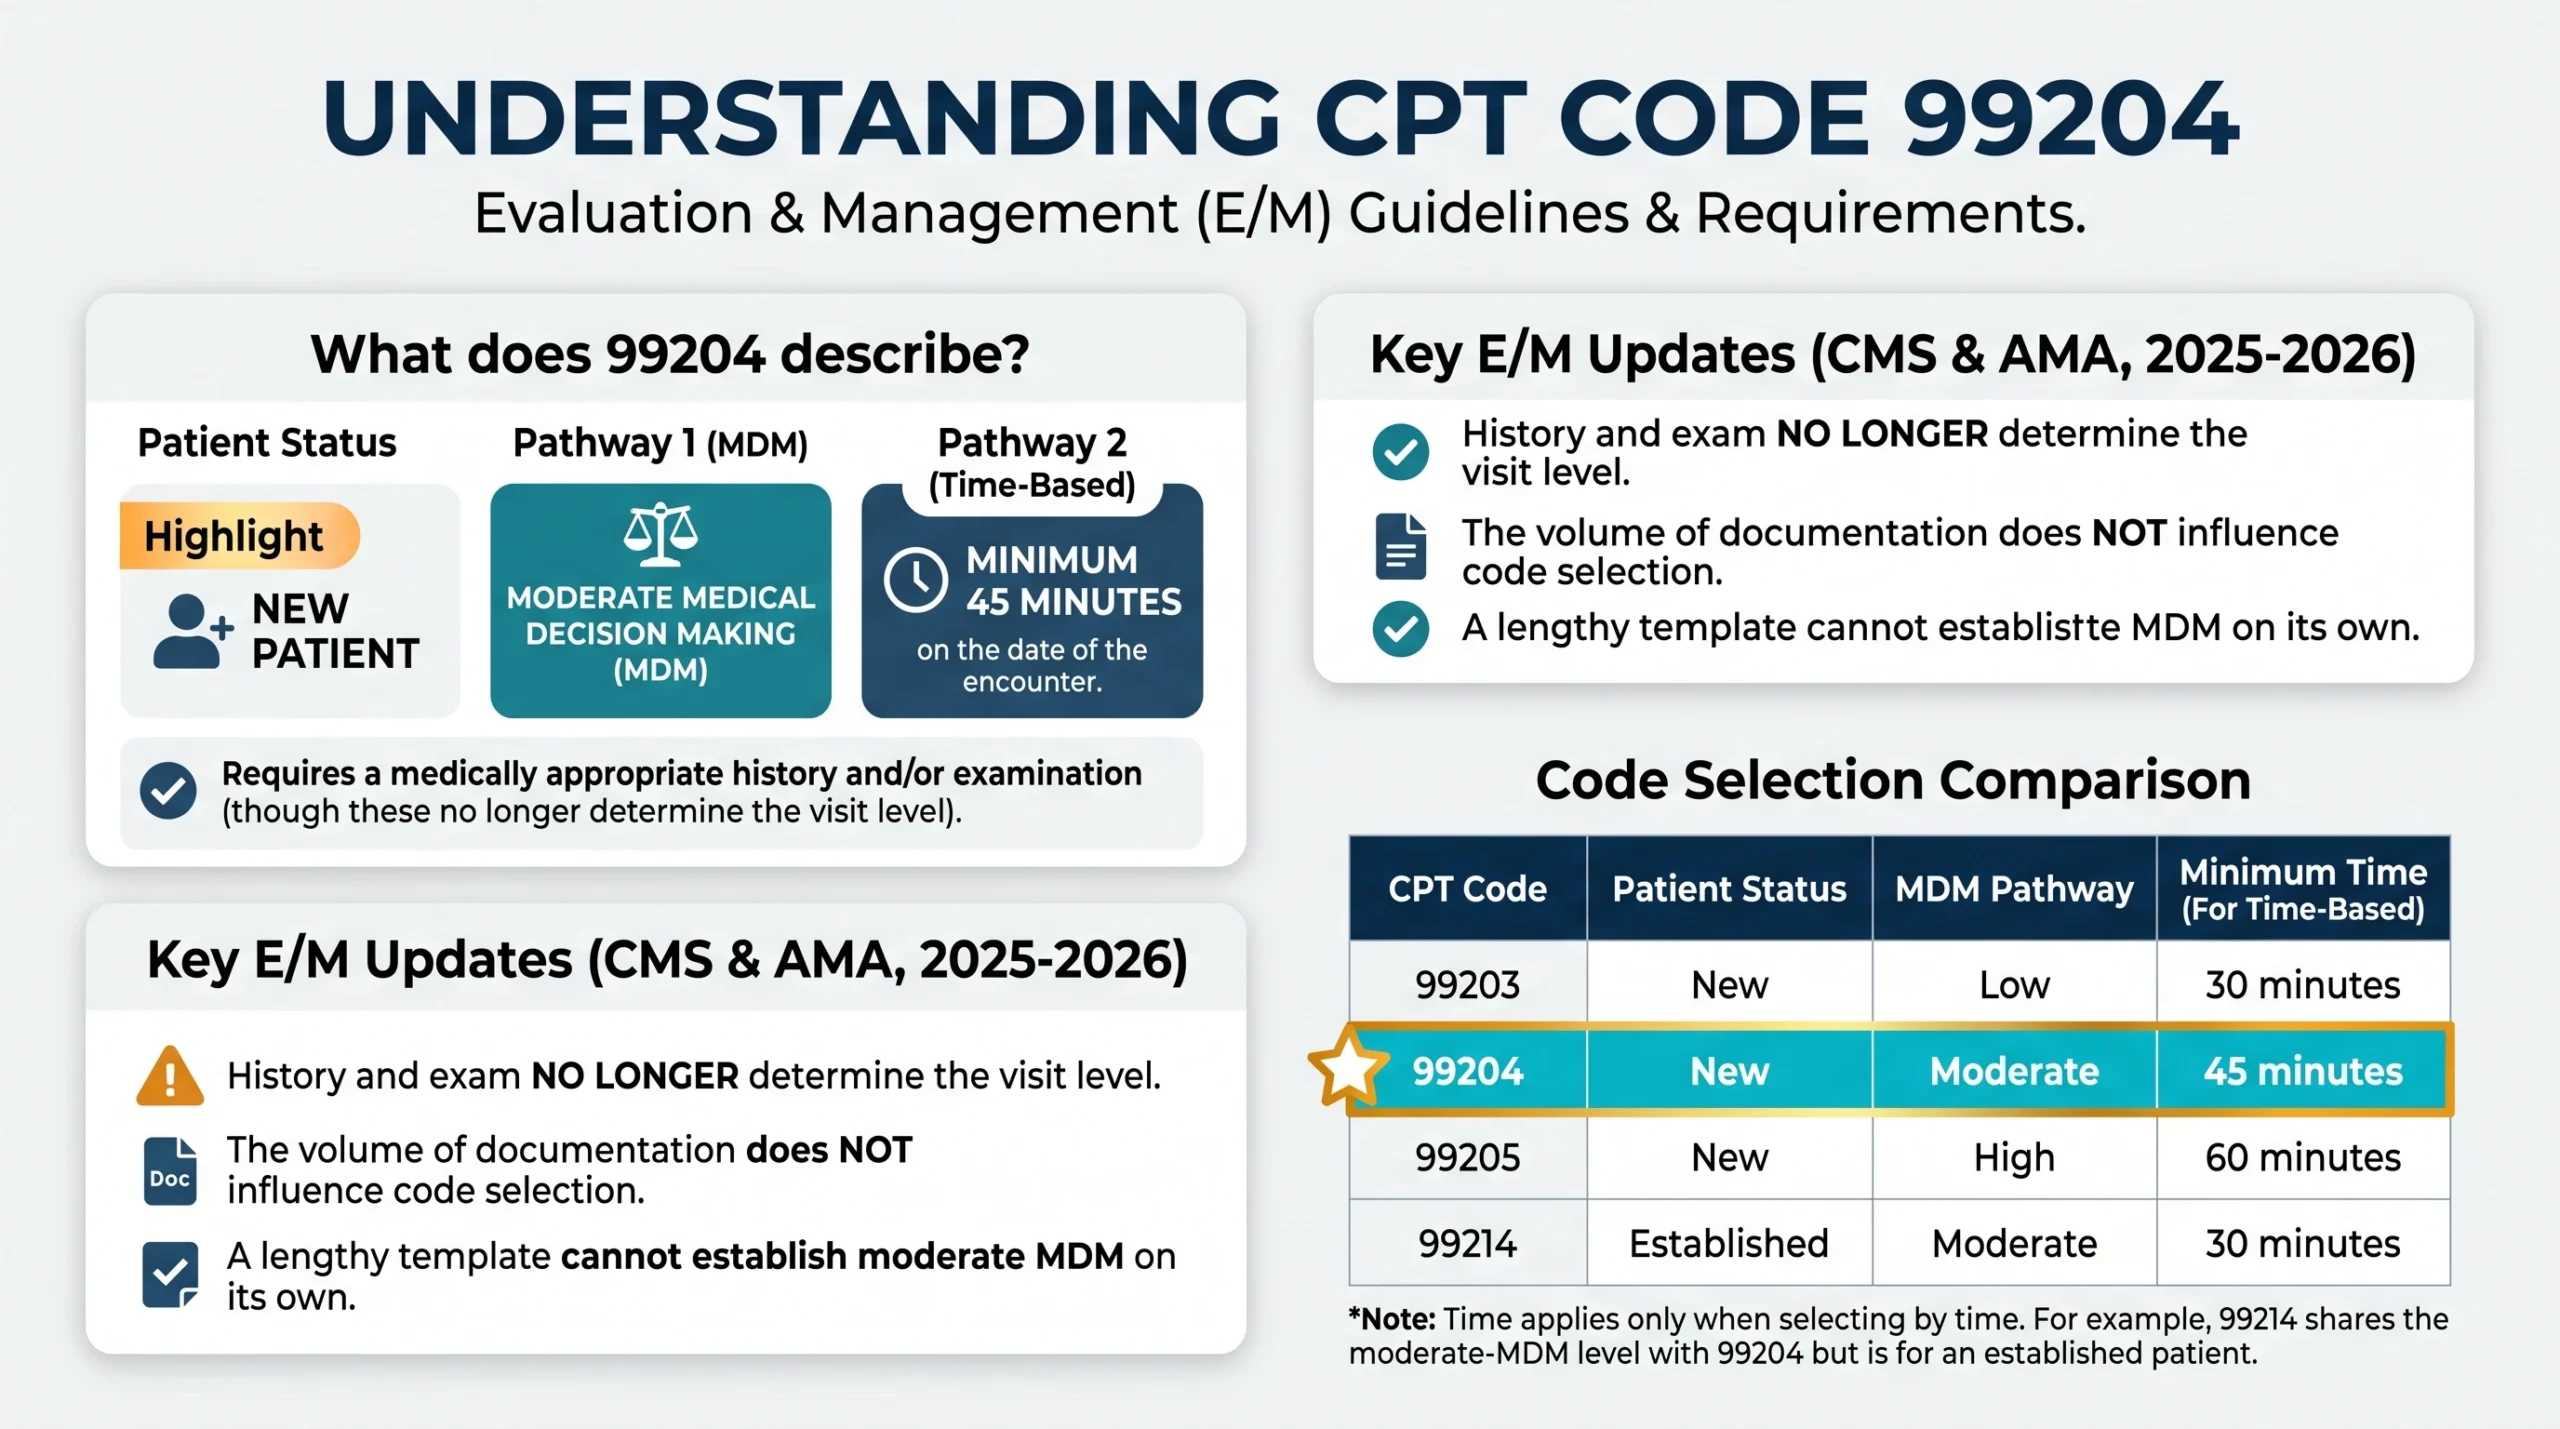
99204 requires a medically appropriate history and/or examination, together with the applicable MDM or time criteria. The American Medical Association’s 2025 report, Requiring Payment for Physician Signatures, reproduces these requirements in its E/M code appendix.
CMS’s Evaluation & Management Services compliance guidance, updated February 11, 2026, explains that history and examination no longer determine the visit level. The volume of documentation should not influence code selection. A lengthy template cannot establish moderate MDM by itself.
The comparison below distinguishes patient status from the two code selection methods:
CPT code | Patient status | MDM pathway | Minimum time when selecting by time |
99203 | New | Low | 30 minutes |
99204 | New | Moderate | 45 minutes |
99205 | New | High | 60 minutes |
99214 | Established | Moderate | 30 minutes |
The time column applies only to time-based selection. For example, 99214 shares the moderate-MDM level with 99204 but belongs to the established-patient category.
Confirm that the patient qualifies as new
Under the AMA’s 2023 CPT E/M Descriptors and Guidelines, a new patient has received no professional services during the preceding three years from the reporting physician or qualified health care professional, or another clinician of the exact same specialty and subspecialty in the same group.
A first appointment with one clinician can therefore be an established-patient visit. Consider someone seen by an internist in the group 18 months earlier who now sees another internist there. Changing clinicians does not restart the three-year period.
Medicare’s wording refers to the same physician or same-specialty group practice. CMS’s Medicare Claims Processing Manual, Chapter 12, section 30.6.7, revised May 7, 2026, also clarifies that a previous diagnostic interpretation without an E/M or other face-to-face service does not, by itself, establish the patient.
During intake, review prior encounters and the applicable payer’s specialty rules before assigning the new-patient category.
How the 45-minute requirement works
Understand the threshold
Older references describe 99204 as a 45–59-minute visit. For CPT 2024, office/outpatient descriptors changed from ranges to minimum thresholds. Andis Robeznieks explained this revision in the AMA article A simpler approach helps physicians properly report E/M services, published December 13, 2023.
For 99204, the threshold is 45 minutes. When selecting solely by time, 45–59 qualifying minutes generally supports 99204; at 60 minutes, assess 99205.
Do not round 44 minutes up to 45. CMS specifies that the full time must be completed; the midpoint rule used for certain other timed services does not apply.
Count the practitioner’s eligible work
The American Academy of Family Physicians’ E/M Coding: Guidelines and FAQs (accessed October 9, 2026) identifies eligible activities performed on the encounter date, including:
- Reviewing relevant records and test results.
- Evaluating and examining the patient.
- Counseling the patient, family, or caregiver.
- Ordering medications, tests, or procedures.
- Documenting the encounter and coordinating care when not separately reported.
Exclude clinical staff time, work performed on another date, and time attributable to separately reported services. An appointment scheduled for 45 minutes does not establish 45 minutes of qualifying work.
For a hypothetical visit, the clinician might spend 9 minutes reviewing records, 29 minutes evaluating and counseling the patient, and 8 minutes completing orders and documentation that evening. The total is 46 minutes. Assuming all activities qualify and the service is medically necessary, time supports 99204.
If those final 8 minutes occurred the following morning, they would not count toward that encounter’s time.
What qualifies as moderate medical decision making?
The AMA’s office E/M decision-making table, effective January 1, 2021, evaluates three elements:
- Problems addressed.
- Data reviewed and analyzed.
- Risk associated with patient management.
At least two of the three elements must reach the moderate level or higher. A moderate-risk treatment decision alone does not establish moderate MDM.
Problems addressed
Examples in the moderate problem category include:
- At least two stable chronic conditions.
- A chronic condition that has deteriorated or caused adverse effects related to treatment.
- A recently discovered problem that has not yet been diagnosed and has an uncertain outcome.
- An acute illness producing systemic symptoms.
- An acute injury with complicating features.
Only conditions evaluated or managed during the encounter count. An imported problem list can contain several diagnoses while the clinician addresses only one.
The AMA’s CPT Evaluation and Management Revisions FAQs, updated January 26, 2026, explains that the clinician determines whether a condition is stable or worsening. Coders should request clarification rather than infer that status from an isolated laboratory value.
Data reviewed and analyzed
The 2025 E/M Services Reference Guide from the Infectious Diseases Society of America outlines three pathways for meeting the moderate data requirements:
- A qualifying combination of three items involving unique tests, external notes from unique sources, or an assessment requiring an independent historian.
- Independent interpretation of a test performed by another clinician, when the interpretation is not separately reported.
- Discussion of management or test interpretation with an external clinician or another appropriate source, when not separately reported.
Apply the AMA’s definitions to each category; a relative’s presence alone does not establish a required independent historian. The counting details matter. Ordering and reviewing the same unique test are not two separate credits. Multiple pages from one external source also do not automatically become multiple data items.
Risk of patient management
Prescription drug management is a moderate-risk example in the AMA table.
Noridian Medicare’s E/M Office or Other Outpatient Services Top Provider Questions with Answers, updated October 9, 2025, explains that a medication change is not always necessary. The documentation must reflect the clinician’s assessment of whether treatment is necessary. A refill entry without documentation of the problem addressed is insufficient.
Document the decision and its rationale. Listing the patient’s current medications leaves the reviewer unable to determine whether any prescription management occurred.
Two examples that separate time from MDM
These hypothetical scenarios illustrate code selection, rather than guarantee payment.
Moderate MDM with 32 minutes: A new patient receives evaluation of two stable chronic illnesses. The clinician assesses treatment response and makes documented decisions to continue prescription therapy. Assuming the record supports moderate problems and moderate management risk, 99204 can be selected through MDM despite the shorter duration.
Low MDM with 48 minutes: A new patient’s medically necessary evaluation involves extensive same-day record review, counseling, and documentation. The problems, data, and management risk support only low MDM, but the clinician documents 48 qualifying minutes. Time can support 99204 without moderate MDM.
For internal reviews, record the selection pathway beside the rationale. This makes it easier to distinguish an unsupported level from a valid level reached through a different method.
Documentation requirements that support the claim
CMS’s Evaluation and Management Services, updated May 2026, calls for documentation that supports the reported service and explains the patient’s assessment and treatment. A practical review should confirm:
- The encounter date, clinician identity, and reason for the visit.
- Relevant history, examination findings, and reviewed results.
- The conditions addressed and their assessed status.
- Tests ordered, treatment decisions, and follow-up plans.
- Documentation should include supporting evidence for the MDM components considered or the exact total time spent when time is used to determine the service level.
A hypothetical time statement could read:
“I spent 47 minutes on this patient’s care on the encounter date, including review of outside records, evaluation, counseling, medication orders, and documentation. This excludes separately reported services.”
Use such wording only when it accurately describes the encounter. The AAFP advises documenting patient-specific details and the exact total time spent, rather than using generic copied statements or broad time ranges.
Same-day procedures and prolonged services
A new-patient visit does not automatically justify a separate E/M charge alongside a minor procedure. CMS’s 2026 National Correct Coding Initiative Policy Manual, effective January 1, 2026, requires a significant, separately identifiable E/M service beyond the work included in the procedure.
When supported, modifier 25 belongs on the E/M code. A different diagnosis is not required, but the record must demonstrate the separate work. New-patient status alone does not satisfy that requirement.
Prolonged-service add-ons also require a different analysis. For new-patient office visits, evaluate the applicable highest-level base code, 99205, and the payer’s prolonged-service rules. Do not append 99417 or Medicare’s G2212 directly to 99204.
Before submitting the 99204 CPT code, confirm new-patient status and identify whether moderate MDM or qualifying time supports the level. Keep the clinical reasoning visible, count only eligible work, and ensure the service remains medically necessary.