



99202 CPT Code Explained: Definition, Billing & Reimbursement Guide
CPT 99202 is used to report a new-patient evaluation and management (E/M) service performed in an office or outpatient setting when the encounter meets the criteria for straightforward medical decision-making (MDM). Providers may also select this code based on the total qualifying time spent on the date of service.
Understanding the difference between these two coding methods is important for accurate medical billing. A brief appointment may qualify for 99202 based on the documented MDM, whereas time-based coding requires the provider to account for all eligible minutes. Neither the scheduled appointment duration nor the length of the clinical note independently establishes the appropriate code.
What Services Does CPT Code 99202 Represent?
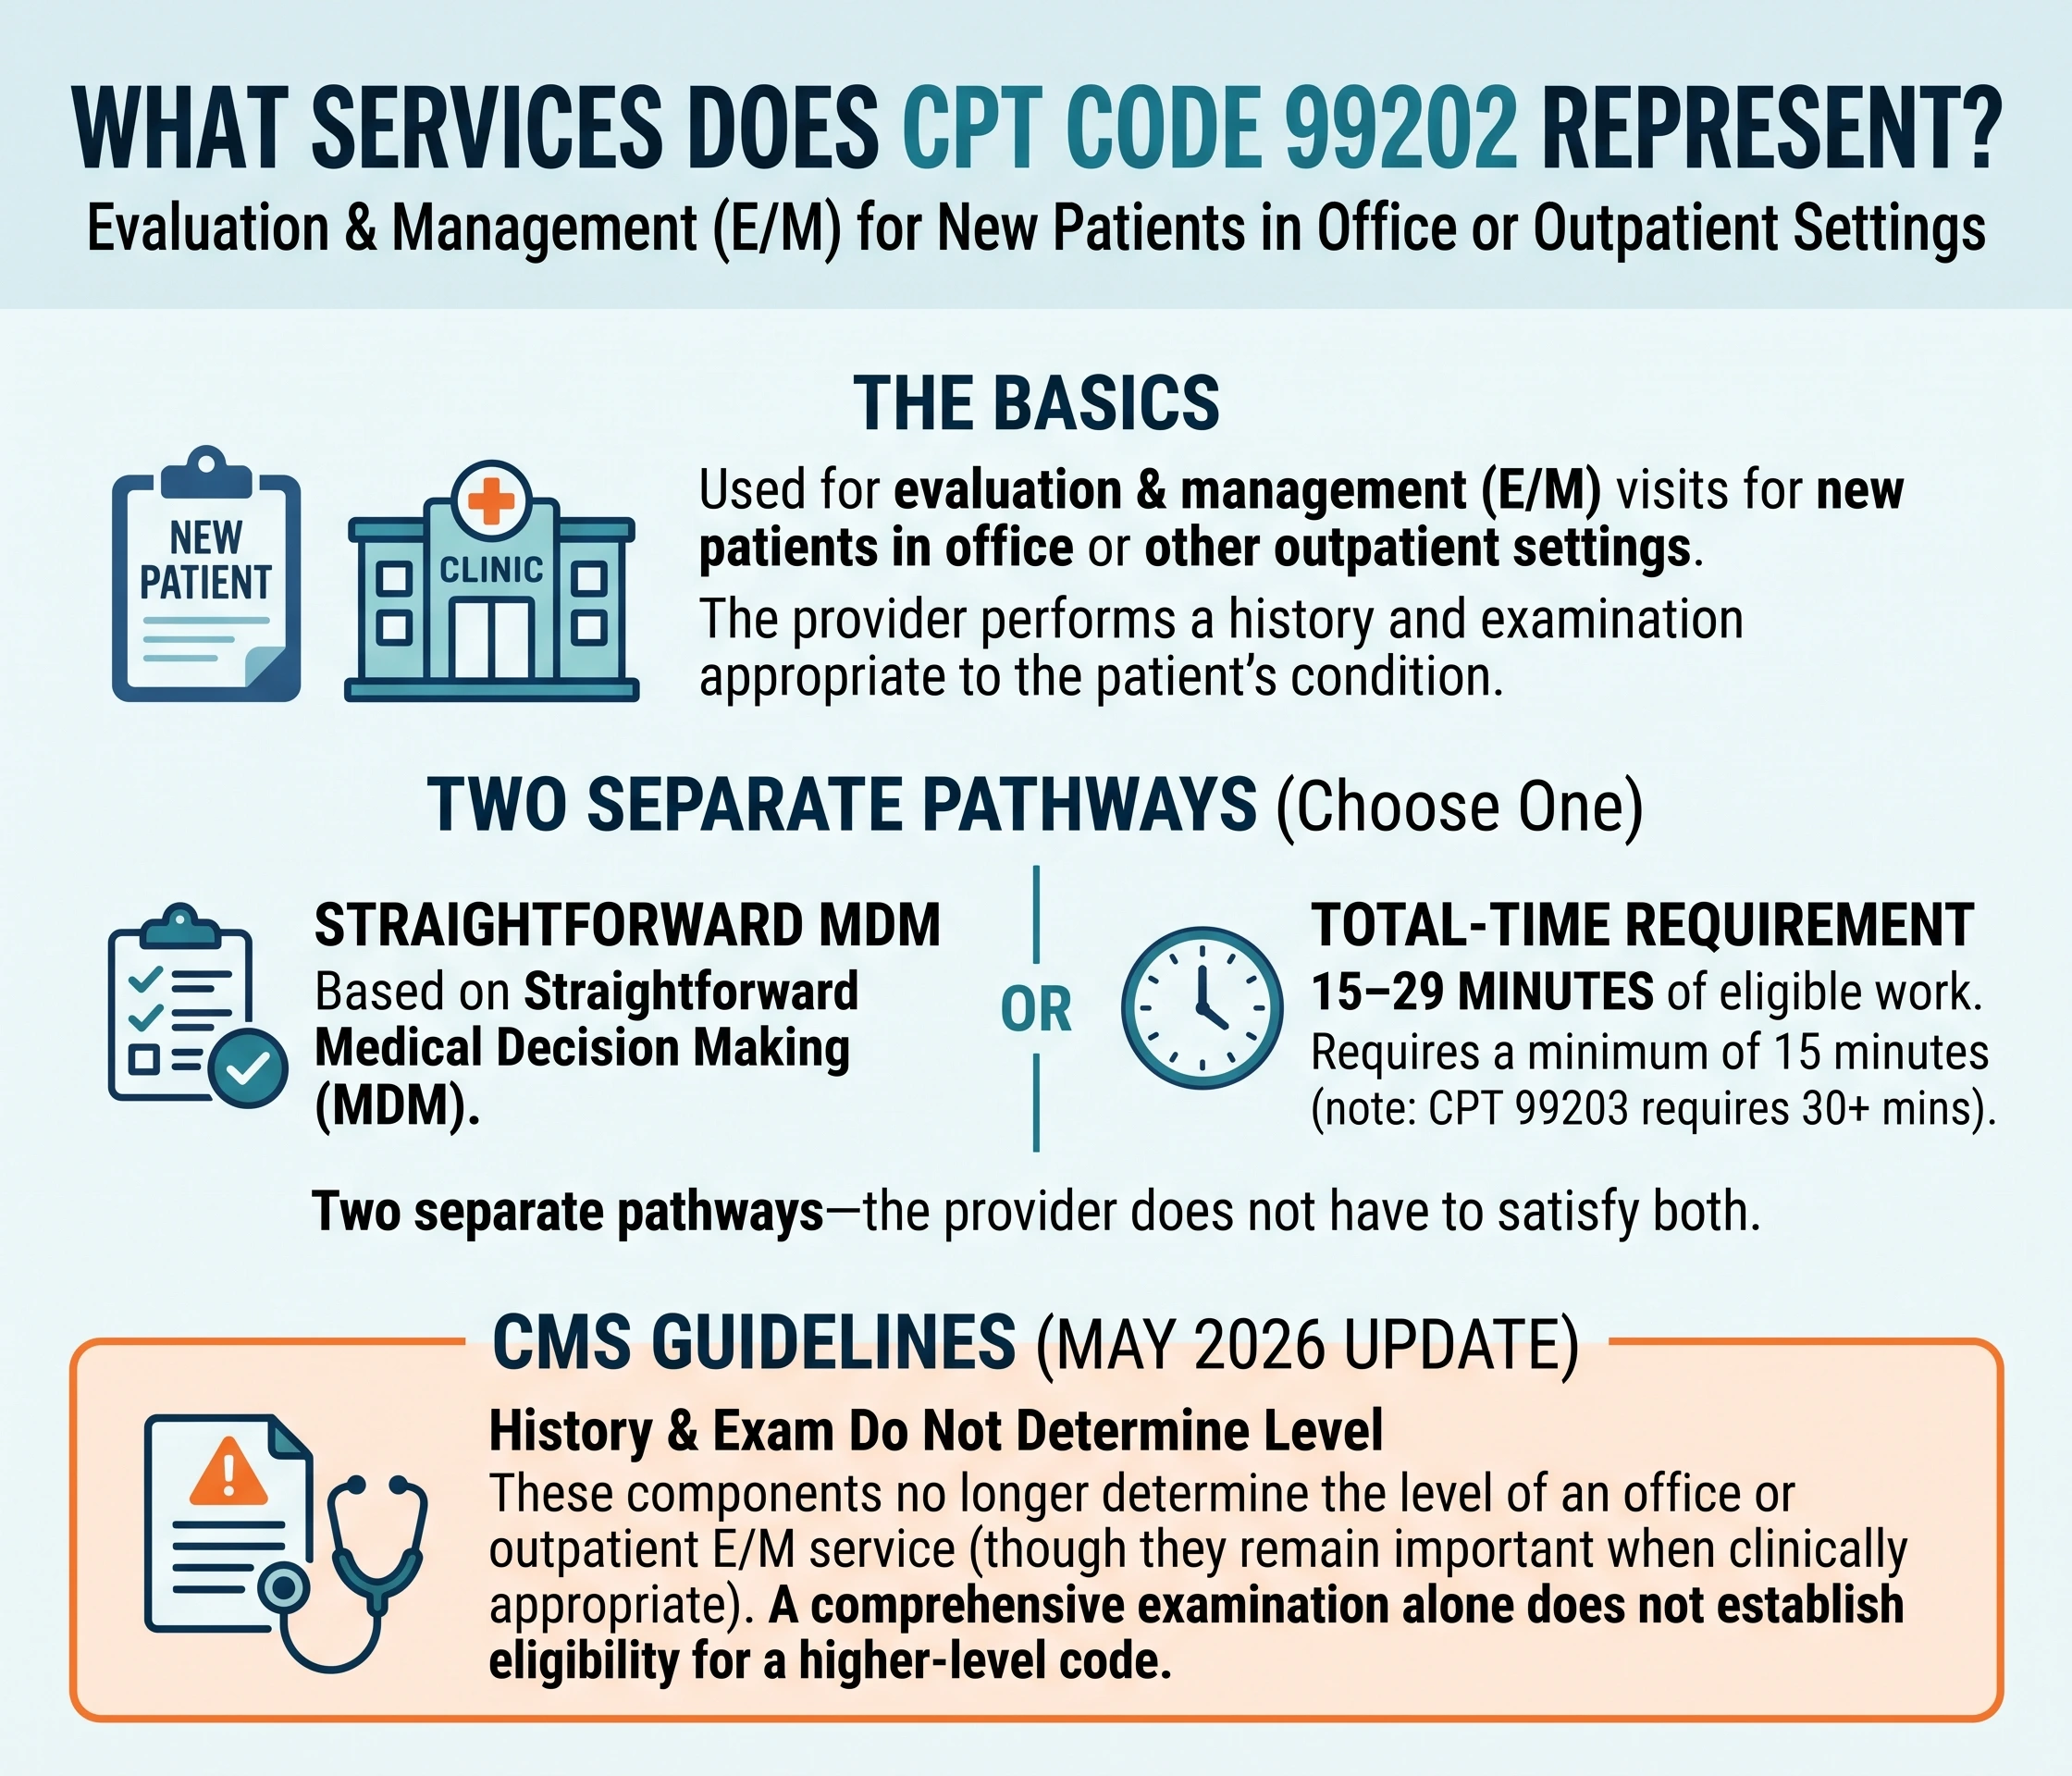
CPT 99202 is used for evaluation and management visits involving new patients in office or other outpatient settings. The provider performs the history and examination appropriate to the patient’s condition. Code assignment is based on either straightforward MDM or the applicable total-time requirement.
To bill based on time, the provider must document a minimum of 15 minutes of eligible work. The commonly referenced range of 15–29 minutes distinguishes this service from CPT 99203, which requires at least 30 minutes when time determines the code. These are two separate coding pathways, so the provider does not have to satisfy both the MDM criteria and the time requirement.
CMS’s Evaluation and Management Services guidance, revised in May 2026, explains that history and examination no longer determine the level of an office or outpatient E/M service. However, these components remain important when clinically appropriate. Performing a comprehensive examination alone does not establish eligibility for a higher-level code.
Verify That the Patient Meets the New-Patient Definition
Creating a new medical record or registering someone for the first time does not automatically make that person a new patient for CPT billing purposes.
Under CPT guidelines, new-patient classification generally depends on whether the individual has received professional services during the preceding three years from the same physician or qualified healthcare professional, or another provider of the same specialty and subspecialty within the same group practice.
The Medicare Claims Processing Manual, revised January 18, 2024, describes the applicable Medicare rule in terms of the same physician specialty within a group. Billing teams should verify the payer’s requirements before treating a subspecialty distinction as grounds for new-patient classification.
For example, imagine that a patient visited a family physician in a group practice 18 months ago and subsequently schedules an appointment with another family physician from that group. The second visit would generally qualify as an established-patient encounter, even if the new physician has never treated that individual before.
Medicare also recognizes an important distinction involving diagnostic testing. Interpreting a test without providing an E/M service or another qualifying face-to-face service does not, by itself, establish a previous patient relationship. Consequently, an earlier ECG interpretation alone does not automatically disqualify someone from new-patient billing.
Understanding Straightforward Medical Decision-Making
The American Medical Association’s 2023 CPT E/M Descriptors and Guidelines identifies three components used to evaluate medical decision-making:
- Problems evaluated or managed during the visit.
- Data reviewed and analyzed by the provider.
- Risk associated with the treatment or management plan.
Straightforward MDM typically includes one minor or self-limiting condition, little to no data review, and minimal risk associated with treatment or management decisions. At least two of the three MDM elements must meet or exceed the level associated with the selected code. The complete encounter should be reviewed before assigning straightforward MDM.
Consider a hypothetical example involving a new patient with a small friction blister that has no complications. The clinician examines the affected area, finds no warning signs, recommends protective measures, and explains when the patient should seek additional care. No diagnostic testing or prescription medication is necessary.
This encounter may support straightforward MDM if the documentation accurately reflects the clinical assessment and management. The appropriate E/M level is determined by more than the diagnosis alone. Additional symptoms, diagnostic work, or treatment decisions could change the MDM classification.
During a coding review, ask: “Which problems did the clinician evaluate, and what decisions were made during this encounter?” Simply listing past diagnoses without clarifying their connection to the current encounter does not establish the work performed.
Which Activities Count Toward the 99202 Time Requirement?
Time-based E/M coding includes qualifying activities personally performed by the physician or other qualified healthcare professional on the date of the encounter. Depending on the service, these activities may involve reviewing records, preparing for the visit, evaluating the patient, providing counseling, ordering services, documenting findings, and coordinating care.
Certain activities must be excluded from the total. These include staff-only work, travel, separately billed services, and work performed on a different date. For instance, the time a nurse spends completing intake procedures cannot be added to the physician’s personal time total.The AMA’s March 2022 guidance on outpatient encounter time also excludes general education that is not directly related to the management of the individual patient’s care.
Suppose a physician spends four minutes reviewing relevant medical records, 12 minutes evaluating and counseling the patient, and another five minutes completing the documentation later that day. The combined total is 21 qualifying minutes, which may support 99202 under the time-based method when the service is medically necessary and all applicable requirements are satisfied.
This time allocation is provided for illustration only and does not represent a mandatory distribution.
The medical record should state the actual qualifying total and provide enough detail to explain the activities performed. For example, documentation might state:
“The physician spent 21 minutes on the date of the encounter, covering relevant record review, patient assessment, counseling, and documentation. Time spent on separately billed services was not included.”
Do not increase a 14-minute total to 15 minutes through rounding. Time-based E/M selection requires the minimum threshold to be met. However, an encounter that falls short of the time requirement may still qualify for 99202 if the documented MDM independently supports that code.
CPT 99202 Compared With Other Office Visit Codes
The main differences between these E/M codes involve patient classification, MDM complexity, and qualifying time.
|
CPT code |
Patient classification |
MDM level |
Minimum time for time-based selection |
|
99202 |
New patient |
Straightforward |
15 minutes |
|
99203 |
New patient |
Low |
30 minutes |
|
99204 |
New patient |
Moderate |
45 minutes |
|
99212 |
Established patient |
Straightforward |
10 minutes |
The listed time thresholds apply when the provider selects the code using time. They do not establish mandatory appointment durations for encounters coded through MDM.
For example, a qualifying 30-minute encounter may support 99203 through the time-based method even when the documented MDM remains straightforward. Conversely, an encounter with low MDM does not automatically require 30 minutes if the provider selects the code through the MDM pathway and the documentation supports that choice.
CPT 99202 should not be assigned automatically whenever a patient attends a brief first appointment. Verify the patient’s status, review the clinical work, and determine whether MDM or qualifying time supports the reported service.
Documentation Requirements for CPT 99202
A strong E/M note should clearly document the patient’s medical needs, the clinician’s evaluation, and the treatment decisions made during the visit.
Documentation should include the presenting concern, relevant history, appropriate clinical findings, assessment, treatment or follow-up plan, and provider authentication. When time is the basis for code selection, record the actual qualifying total. When MDM is used, the note should clearly demonstrate the problems addressed, data considered, and management risks involved.
CMS’s May 2026 E/M guidance identifies medical necessity as the primary consideration in determining payment. A longer note or additional paragraphs cannot replace evidence that the service was necessary and actually performed.
As part of an internal billing audit, distinguish between missing clinical details and coding errors. When the documentation fails to clearly support the provider’s assessment, seek clarification from the clinician when necessary. Simply changing the CPT code will not correct incomplete or unclear documentation.
When Is Modifier 25 Appropriate With CPT 99202?
Reporting a procedure and an E/M service on the same date does not automatically justify appending modifier 25 to CPT 99202.
CMS’s 2026 National Correct Coding Initiative Policy Manual, effective January 1, 2026, states that modifier 25 may be applicable when an E/M service is significant, separately identifiable, and distinct from the work typically performed as part of the related procedure.
For minor surgical procedures, the routine evaluation and decision-making necessary to perform the procedure are generally included in the procedure’s payment. The patient’s new-patient status does not change this requirement.
Before submitting 99202 with modifier 25, confirm that the documentation demonstrates additional E/M work beyond the usual procedural services. The modifier belongs on the E/M code. When time determines the E/M level, exclude time attributable to separately reported procedures from the total.
How Is Reimbursement for CPT 99202 Calculated?
CPT 99202 does not have one universal reimbursement amount. The payment depends on the applicable fee schedule, geographic location, service setting, and payer-specific rules.
Medicare calculates Physician Fee Schedule payments using relative value units (RVUs) for physician work, practice expenses, and professional liability insurance. Geographic adjustment factors are applied to account for regional cost differences, and the applicable conversion factor is used to calculate the payment amount. Payment rates may differ between facility and nonfacility settings.
CMS’s PFS Look-Up Tool Overview, updated February 9, 2026, explains how to search for payment information using a procedure code and Medicare payment locality. For a reliable estimate, select the appropriate service year, geographic locality, and place-of-service setting.
Medicare Payment Updates for 2026
CMS’s October 31, 2025, fact sheet concerning the Calendar Year 2026 Medicare Physician Fee Schedule Final Rule identifies two conversion factors: approximately $33.57 for qualifying participants in alternative payment models (APMs) and $33.40 for other applicable participants.
These values are conversion factors and should not be interpreted as the actual payment rates for CPT 99202. The final payment must be calculated using the applicable RVUs, geographic adjustments, and other relevant fee-schedule rules.
Understanding the Allowed Amount and Insurance Payment
For covered physician services under Original Medicare, beneficiaries generally pay 20% of the Medicare-approved amount after satisfying the applicable Part B deductible, subject to relevant coverage and payment rules.
For illustration, assume Medicare approves a service at $100 and the beneficiary has already met the deductible. Before accounting for other adjustments, Medicare would generally pay $80, while the beneficiary would owe $20 in coinsurance. This example uses a hypothetical allowed amount and does not represent a published reimbursement rate for 99202.
When reviewing a claim, compare the payer’s allowed amount with the correct fee schedule before concluding that a lower-than-expected payment represents an underpayment. Reconcile the remittance advice against deductible obligations, coinsurance, secondary insurance, contractual adjustments, and other applicable payment details.
Final Checklist Before Submitting a CPT 99202 Claim
Before submitting a claim for CPT 99202, confirm that the patient meets the applicable new-patient requirements. Review the clinical record to determine whether straightforward MDM or the minimum qualifying time supports the selected code.
Check any procedure performed during the same encounter to determine whether a separately identifiable E/M service and modifier 25 are justified. Finally, verify the appropriate fee schedule, geographic locality, and service setting when reviewing expected reimbursement.
These steps help ensure that the billed service accurately reflects the care provided and that the claim is supported by the clinical documentation.