



What Is CPT Code 96127? Description, Uses & Billing Tips
CPT code 96127 reports a brief assessment of emotional or behavioral health using a standardized instrument, with scoring and documentation. Depression inventories and attention-deficit/hyperactivity disorder (ADHD) rating scales are examples. The service is reported per instrument.
For a billing team, the questions extend beyond whether a questionnaire was completed. Why was it administered? Was it scored? Does the patient’s plan pay separately for that assessment alongside the other services provided?
Those distinctions shape the claim. A depression screening during preventive care and an assessment used to monitor an established condition can involve the same questionnaire but require different diagnosis coding and coverage analysis.
What CPT code 96127 covers
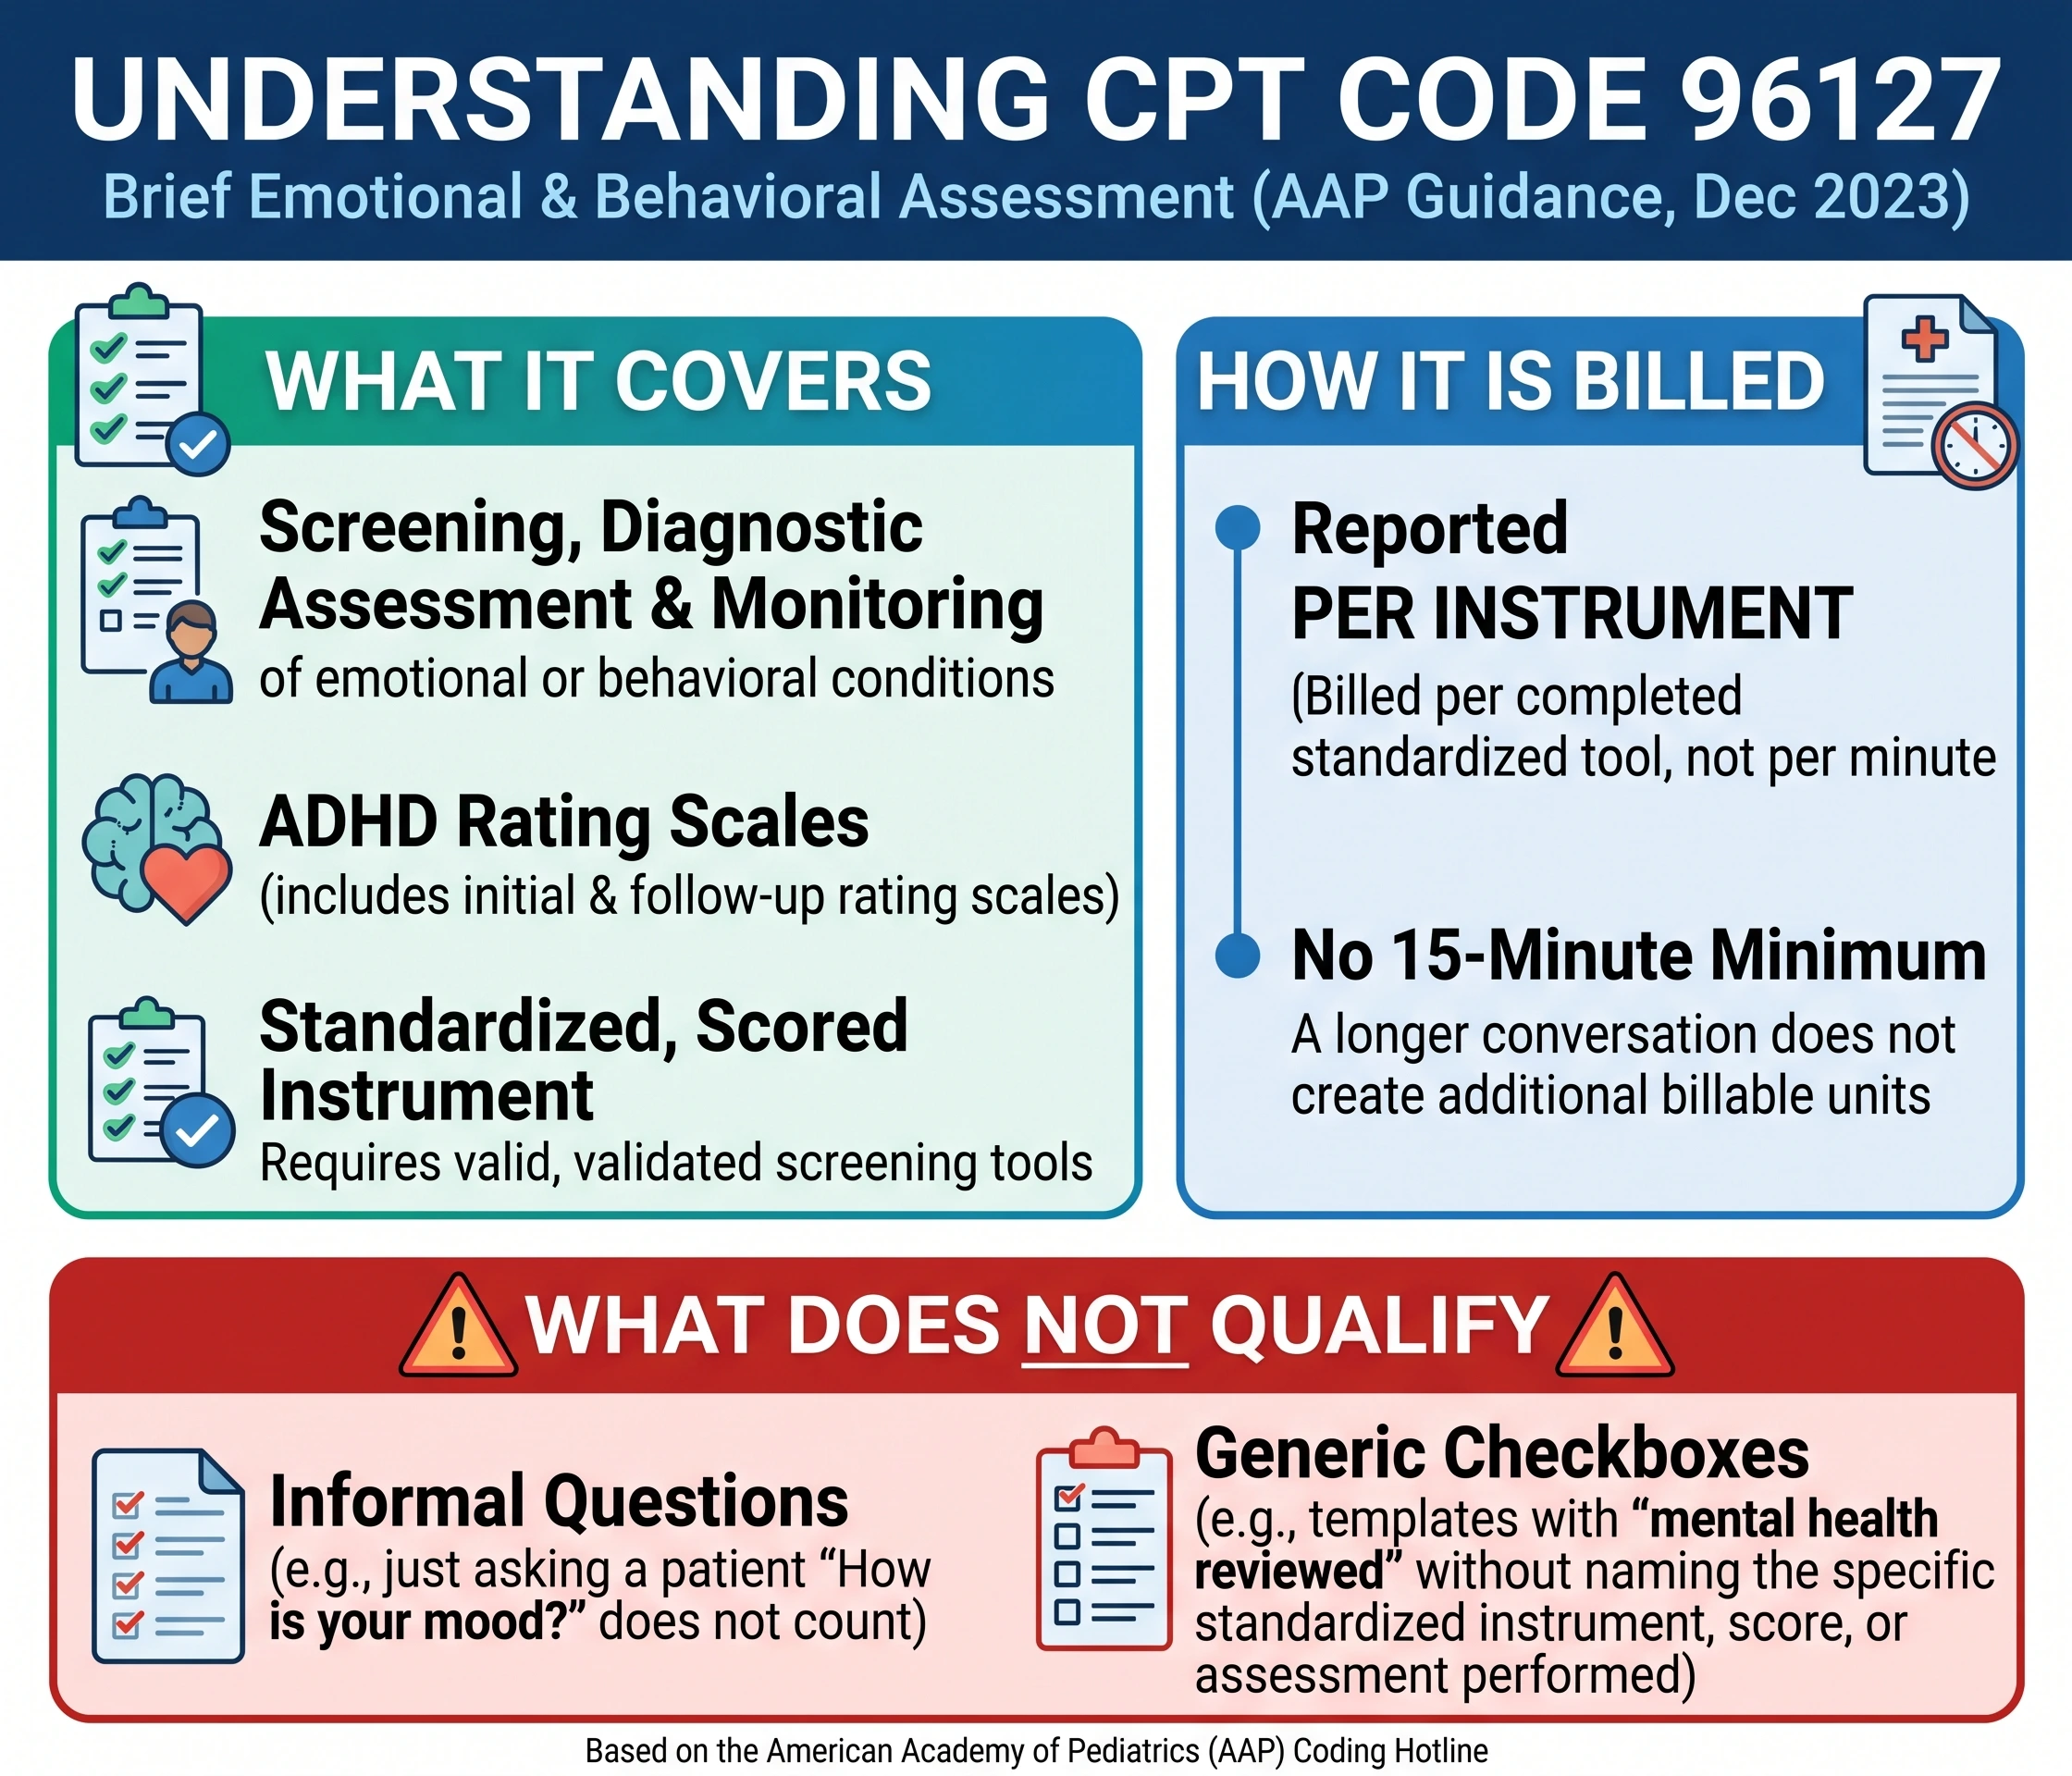
The American Academy of Pediatrics (AAP), in its December 2023 Pediatric Coding Q&A: Expert Advice From the AAP Coding Hotline, explains that 96127 can support screening, diagnostic assessment, and monitoring of emotional or behavioral conditions. Its ADHD guidance specifically includes initial and follow-up rating scales.
96127 is reported per instrument, not per minute. The descriptor does not establish a 15-minute minimum. A longer conversation therefore does not create additional units, and an informal question about mood does not meet the requirement for a standardized, scored instrument.
This distinction also helps practices review their templates. A checkbox reading “mental health reviewed” does not identify the instrument, score, or assessment performed.
Which assessment tools may qualify?
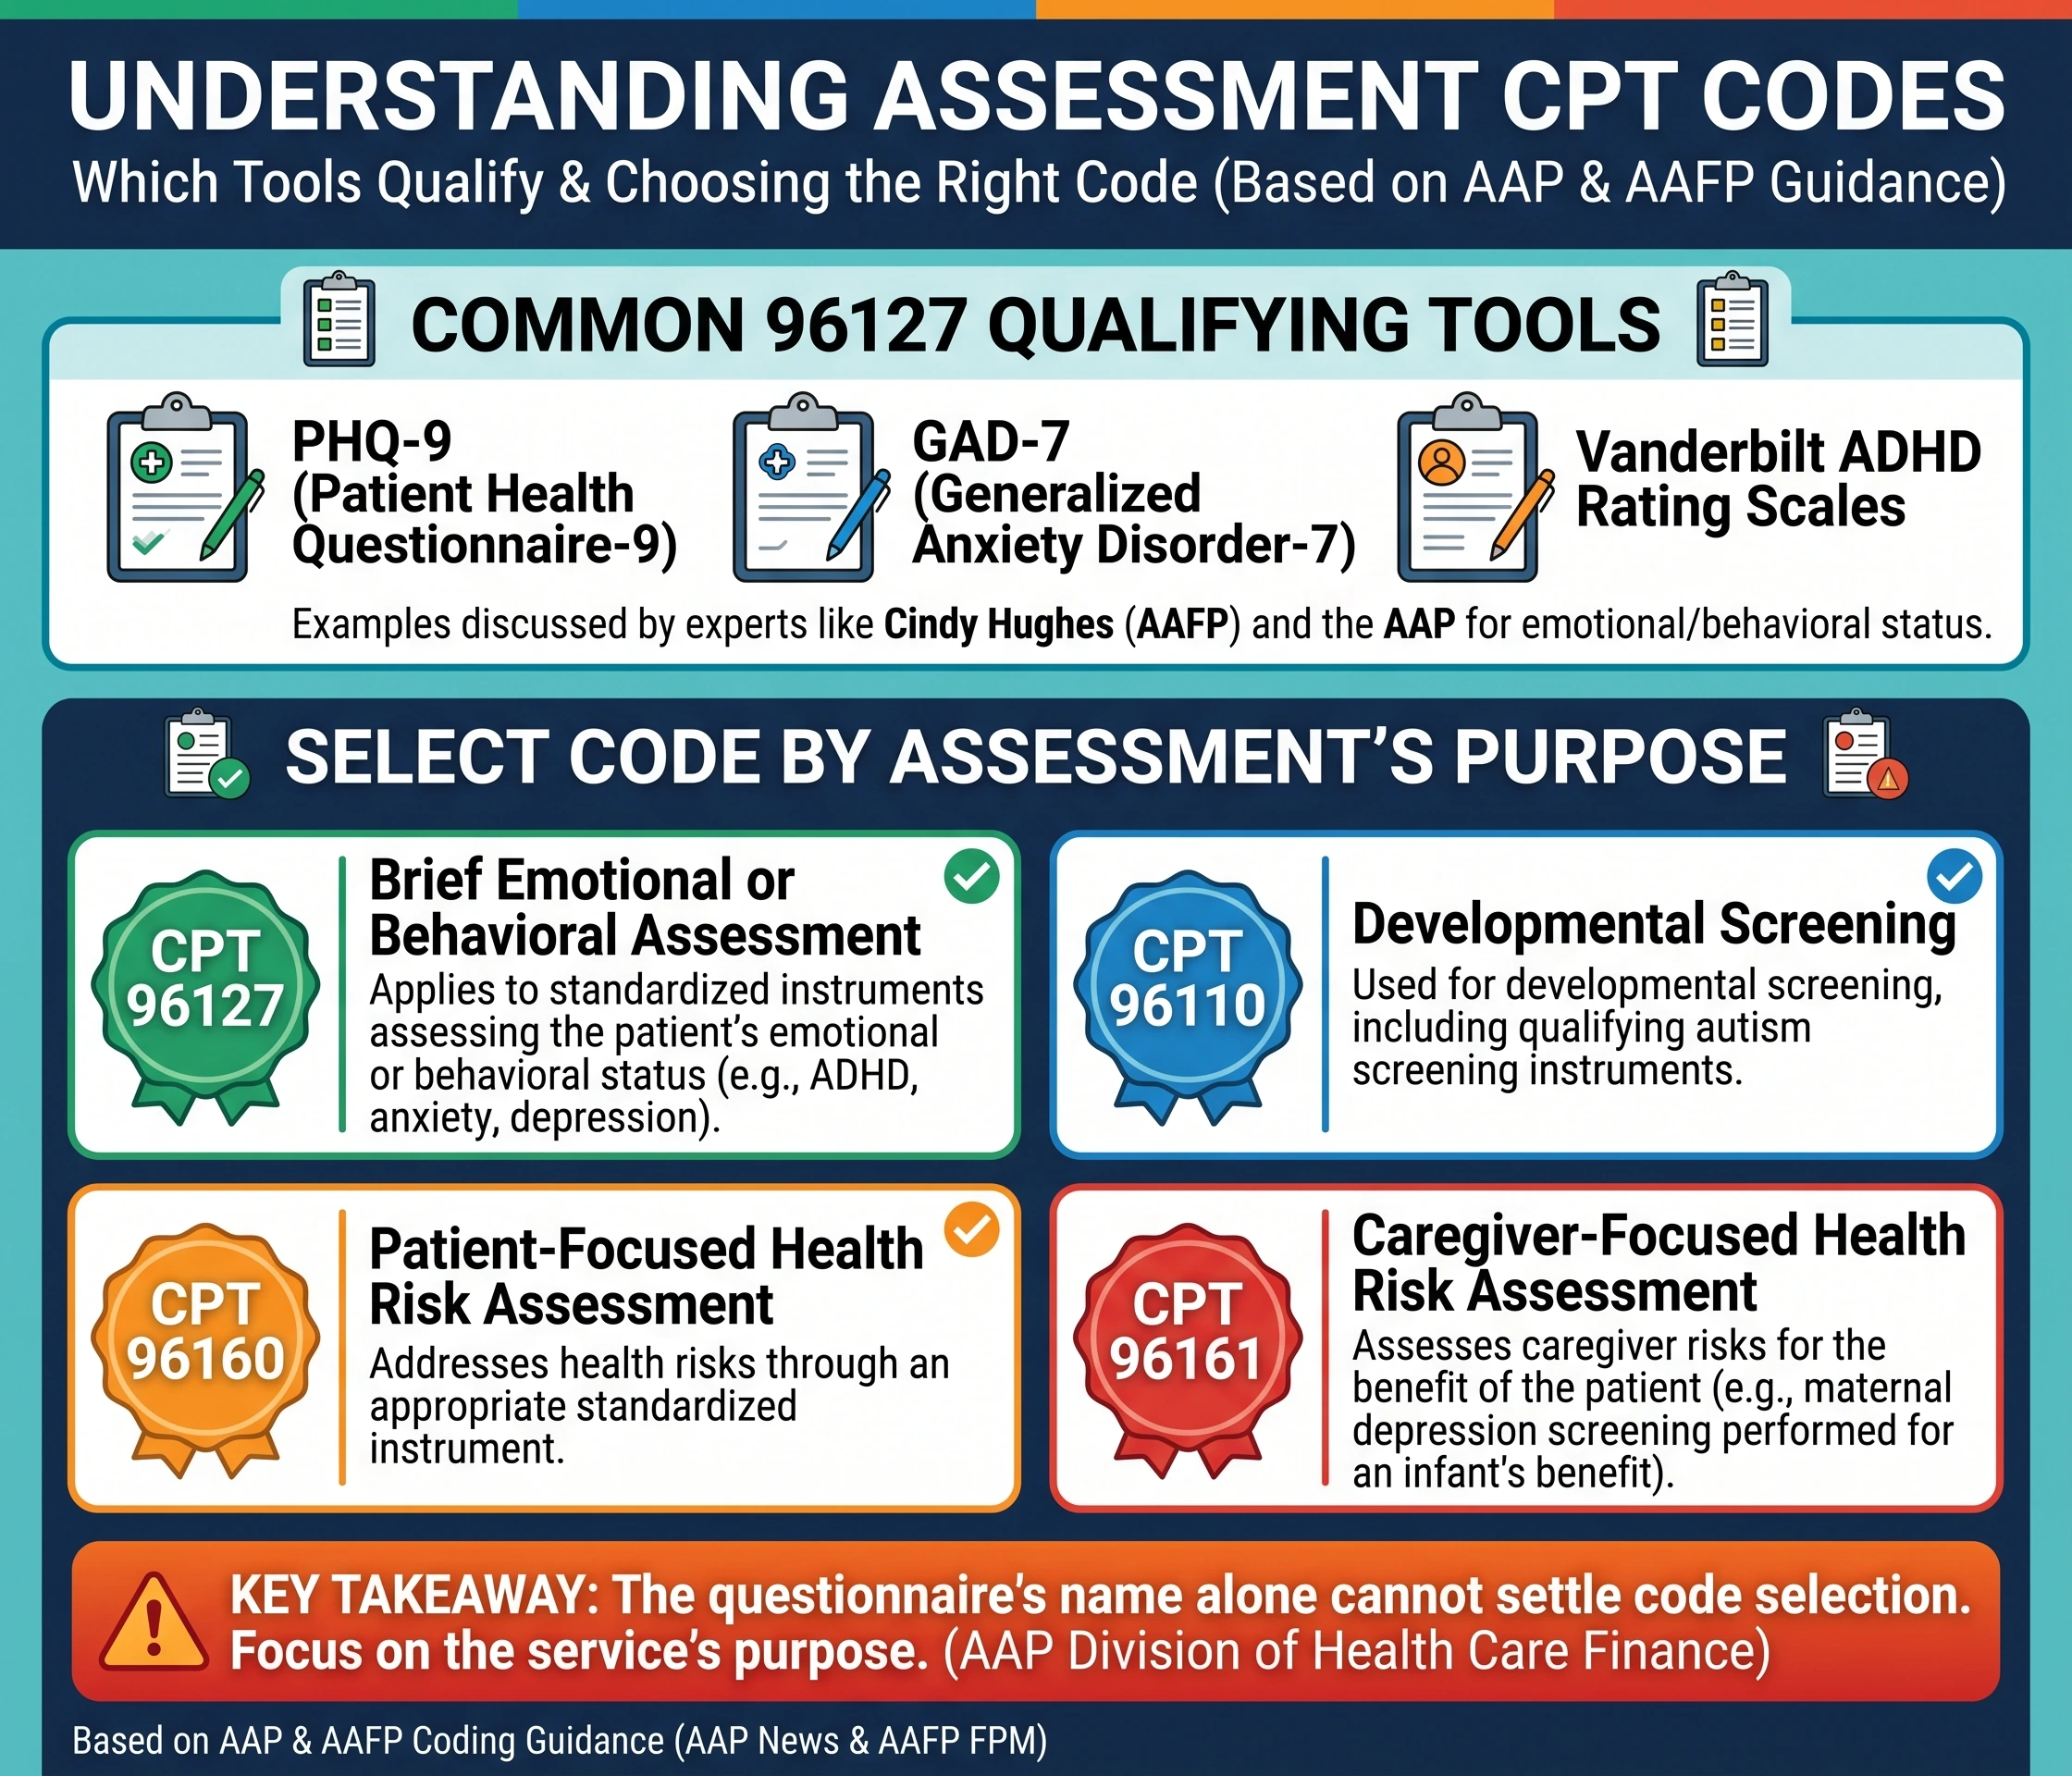
Common examples include the Patient Health Questionnaire-9 (PHQ-9), Generalized Anxiety Disorder-7 (GAD-7), and Vanderbilt ADHD rating scales. Cindy Hughes, CPC, CFPC, discusses PHQ-9 and GAD-7 reporting in the American Academy of Family Physicians’ (AAFP) May/June 2020 FPM “Coding & Documentation” column. The AAP also identifies Vanderbilt scales among instruments associated with 96127.
Select the code according to the assessment’s purpose:
Code | Service being reported | Practical distinction |
96127 | Brief emotional or behavioral assessment | Applies to standardized instruments assessing the patient’s emotional or behavioral status |
96110 | Developmental screening | Used for developmental screening, including qualifying autism screening instruments |
96160 | Patient-focused health risk assessment | Addresses health risks through an appropriate standardized instrument |
96161 | Caregiver-focused health risk assessment | Assesses caregiver risks for the benefit of the patient |
The AAP Division of Health Care Finance explains these distinctions in its November 4, 2016, AAP News coding guidance. For example, maternal depression screening performed for an infant’s benefit may fall under 96161. The questionnaire’s name alone cannot settle code selection.
Documentation that supports the service
In Getting Paid for Screening and Assessment Services, published in AAFP’s November/December 2017 FPM, Hughes identifies the information needed to document structured assessments.
A useful review checklist includes:
- Patient identification and service date.
- Instrument name.
- Informant’s identity and relationship to the patient, when applicable.
- Recorded score.
- Name and credentials of the person administering the instrument.
- Clinician review and discussion of results within the related evaluation and management documentation.
Hughes also notes that some payers require a separate report. Verify that requirement before treating an embedded EHR score as sufficient.
For internal review, keep the assessment information easy to locate. A reviewer should be able to connect the billed unit to a specific instrument and result without reconstructing the encounter from scattered entries.
An elevated score also needs clinical follow-through. The U.S. Preventive Services Task Force’s June 20, 2023, recommendation, Depression and Suicide Risk in Adults: Screening, states that positive screens require further diagnostic evaluation and appropriate care or referral. A positive screening result does not independently establish a diagnosis.
Units and frequency depend on the payer
One completed, scored instrument generally supports one unit of 96127. Two distinct instruments can support two units, subject to coverage and claim edits. Hughes’ 2020 FPM example applies this principle to PHQ-9 and GAD-7 assessments.
There is no single daily limit that can safely be applied across every insurance product:
- Nevada Medicaid’s Provider Type 14 Billing Guide, updated January 12, 2026, lists a limit of two units per day for 96127.
- UnitedHealthcare Community Plan’s Medically Unlikely Edits Policy, version updated October 4, 2026, lists a New Jersey exception limiting 96127 to one unit per day.
These are rules for the identified programs, not nationwide CPT limits.
Separate the number of instruments performed from the number payable. Also distinguish a daily unit limit from a repeat-assessment frequency restriction.
CMS defines medically unlikely edits (MUEs) around units reported for the same patient, provider, and service date under most circumstances. Its current MUE resources should be checked for the applicable claim type and effective quarter. Passing a unit edit does not resolve every coverage question.
Choose diagnosis codes according to the encounter
A screening diagnosis fits preventive screening of an asymptomatic patient. An assessment prompted by symptoms or used to monitor an established disorder requires diagnosis coding that reflects that documented purpose.
Examples discussed in Hughes’ 2020 FPM guidance include:
- Z13.31: Encounter for screening for depression.
- Z13.39: Encounter for screening examination for other mental health and behavioral disorders, including an appropriate anxiety screening encounter.
For symptom-driven assessments, select the supported symptom or established diagnosis instead of automatically applying a screening code.
Avoid an EHR rule that assigns a depression diagnosis whenever a score crosses a threshold. The clinician’s assessment must establish the diagnosis; the instrument supplies information for that evaluation.
Billing 96127 with an office visit
An assessment and a separately supported office evaluation and management (E/M) service may be reported during the same encounter. Review the payer’s rules for that combination.
Where modifier 25 is appropriate, it belongs on the E/M code, not 96127. The E/M work must be significant and separately identifiable. Andis Robeznieks explains this requirement in the American Medical Association’s August 17, 2023, article, Setting the Record Straight on Proper Use of Modifier 25.
For example, a clinician might evaluate worsening symptoms, assess treatment response, and modify the care plan while the practice separately administers a standardized instrument. The documentation must support the E/M service selected. Completing a questionnaire does not establish an office-visit level.
Check bundling before adding assessment charges to a larger behavioral health service. Nevada Medicaid’s January 2026 guide states that when screening forms part of a full assessment, only the full assessment is reimbursable under that program. A separate score in the chart does not override that payment rule.
Medicare depression screening: 96127 versus G0444
For Medicare’s covered annual preventive depression screening, evaluate G0444. Its descriptor specifies annual depression screening of 5 to 15 minutes.
Noridian Healthcare Solutions’ Depression Screening guidance, updated January 8, 2025, lists annual coverage in a primary care setting with staff-assisted support for diagnosis, treatment, and follow-up. It also identifies restrictions involving the initial annual wellness visit and the initial preventive physical examination.
A symptom-driven assessment requires a different analysis. Hughes’ September/October 2016 FPM “Coding & Documentation” column distinguishes preventive Medicare depression screening under G0444 from brief emotional or behavioral assessment prompted by symptoms under 96127. Payment still depends on the applicable rules.
CMS’s 2026 NCCI Policy Manual for Medicare Services, revised January 1, 2026, prohibits separately reporting G0444 when its work duplicates a related E/M, psychiatric diagnostic, or psychotherapy service. Therefore, do not add an annual screening charge simply because a PHQ-9 appears in a depression treatment encounter.
Reimbursement and denial review
A national payment figure cannot establish what every practice will receive. CMS’s PFS Look-up Tool Overview, updated February 9, 2026, explains that Medicare payment calculations incorporate geographic adjustments. Check the applicable year, locality, and payment information; use the contracted fee schedule for commercial claims.
A practical denial review should separate four questions: Was the service covered? Were the units permitted? Was the diagnosis appropriate? Was separate payment allowed?
This approach gives the reviewer a specific issue to investigate. For a unit denial, compare the instrument count with the applicable limit. For a bundling denial, examine the other services and the payer’s policy before changing modifiers.
A practical billing example
Consider this hypothetical encounter: a patient reports persistent worry and low mood. The practice administers and scores a PHQ-9 and GAD-7, and the clinician evaluates the symptoms and documents a treatment plan.
Two instruments were performed. Before submitting two units, the biller checks the plan’s unit allowance and same-day payment rules. Diagnosis coding follows the documented symptoms or diagnoses. Any E/M charge needs independent support, with modifier 25 used when appropriate.
CPT code 96127 represents a specific, documented assessment service. Accurate billing connects each instrument to its score, clinical purpose, diagnosis coding, and payer requirements. Keeping those elements aligned gives the practice a defensible claim and a clear basis for reviewing denials.