



90837 CPT Code Explained: Billing, Time Requirements & Documentation Guide
Mental health professionals rely on accurate Current Procedural Terminology (CPT) codes to receive reimbursement for their services. The 90837 CPT code designates a specific duration of individual psychotherapy. The American Medical Association (AMA) defines this code as psychotherapy with a patient (and family members if present) lasting 60 minutes.
Accurate coding requires more than selecting a procedure from a list. Medical billers, coders, and clinicians must understand the exact time thresholds, modifier requirements, and documentation standards mandated by both the Centers for Medicare and Medicaid Services (CMS) and private insurance carriers. This guide details the precise rules for using the 90837 CPT code, common reasons for claim denials, and steps to maintain compliance during payer audits.
What is the 90837 CPT code?
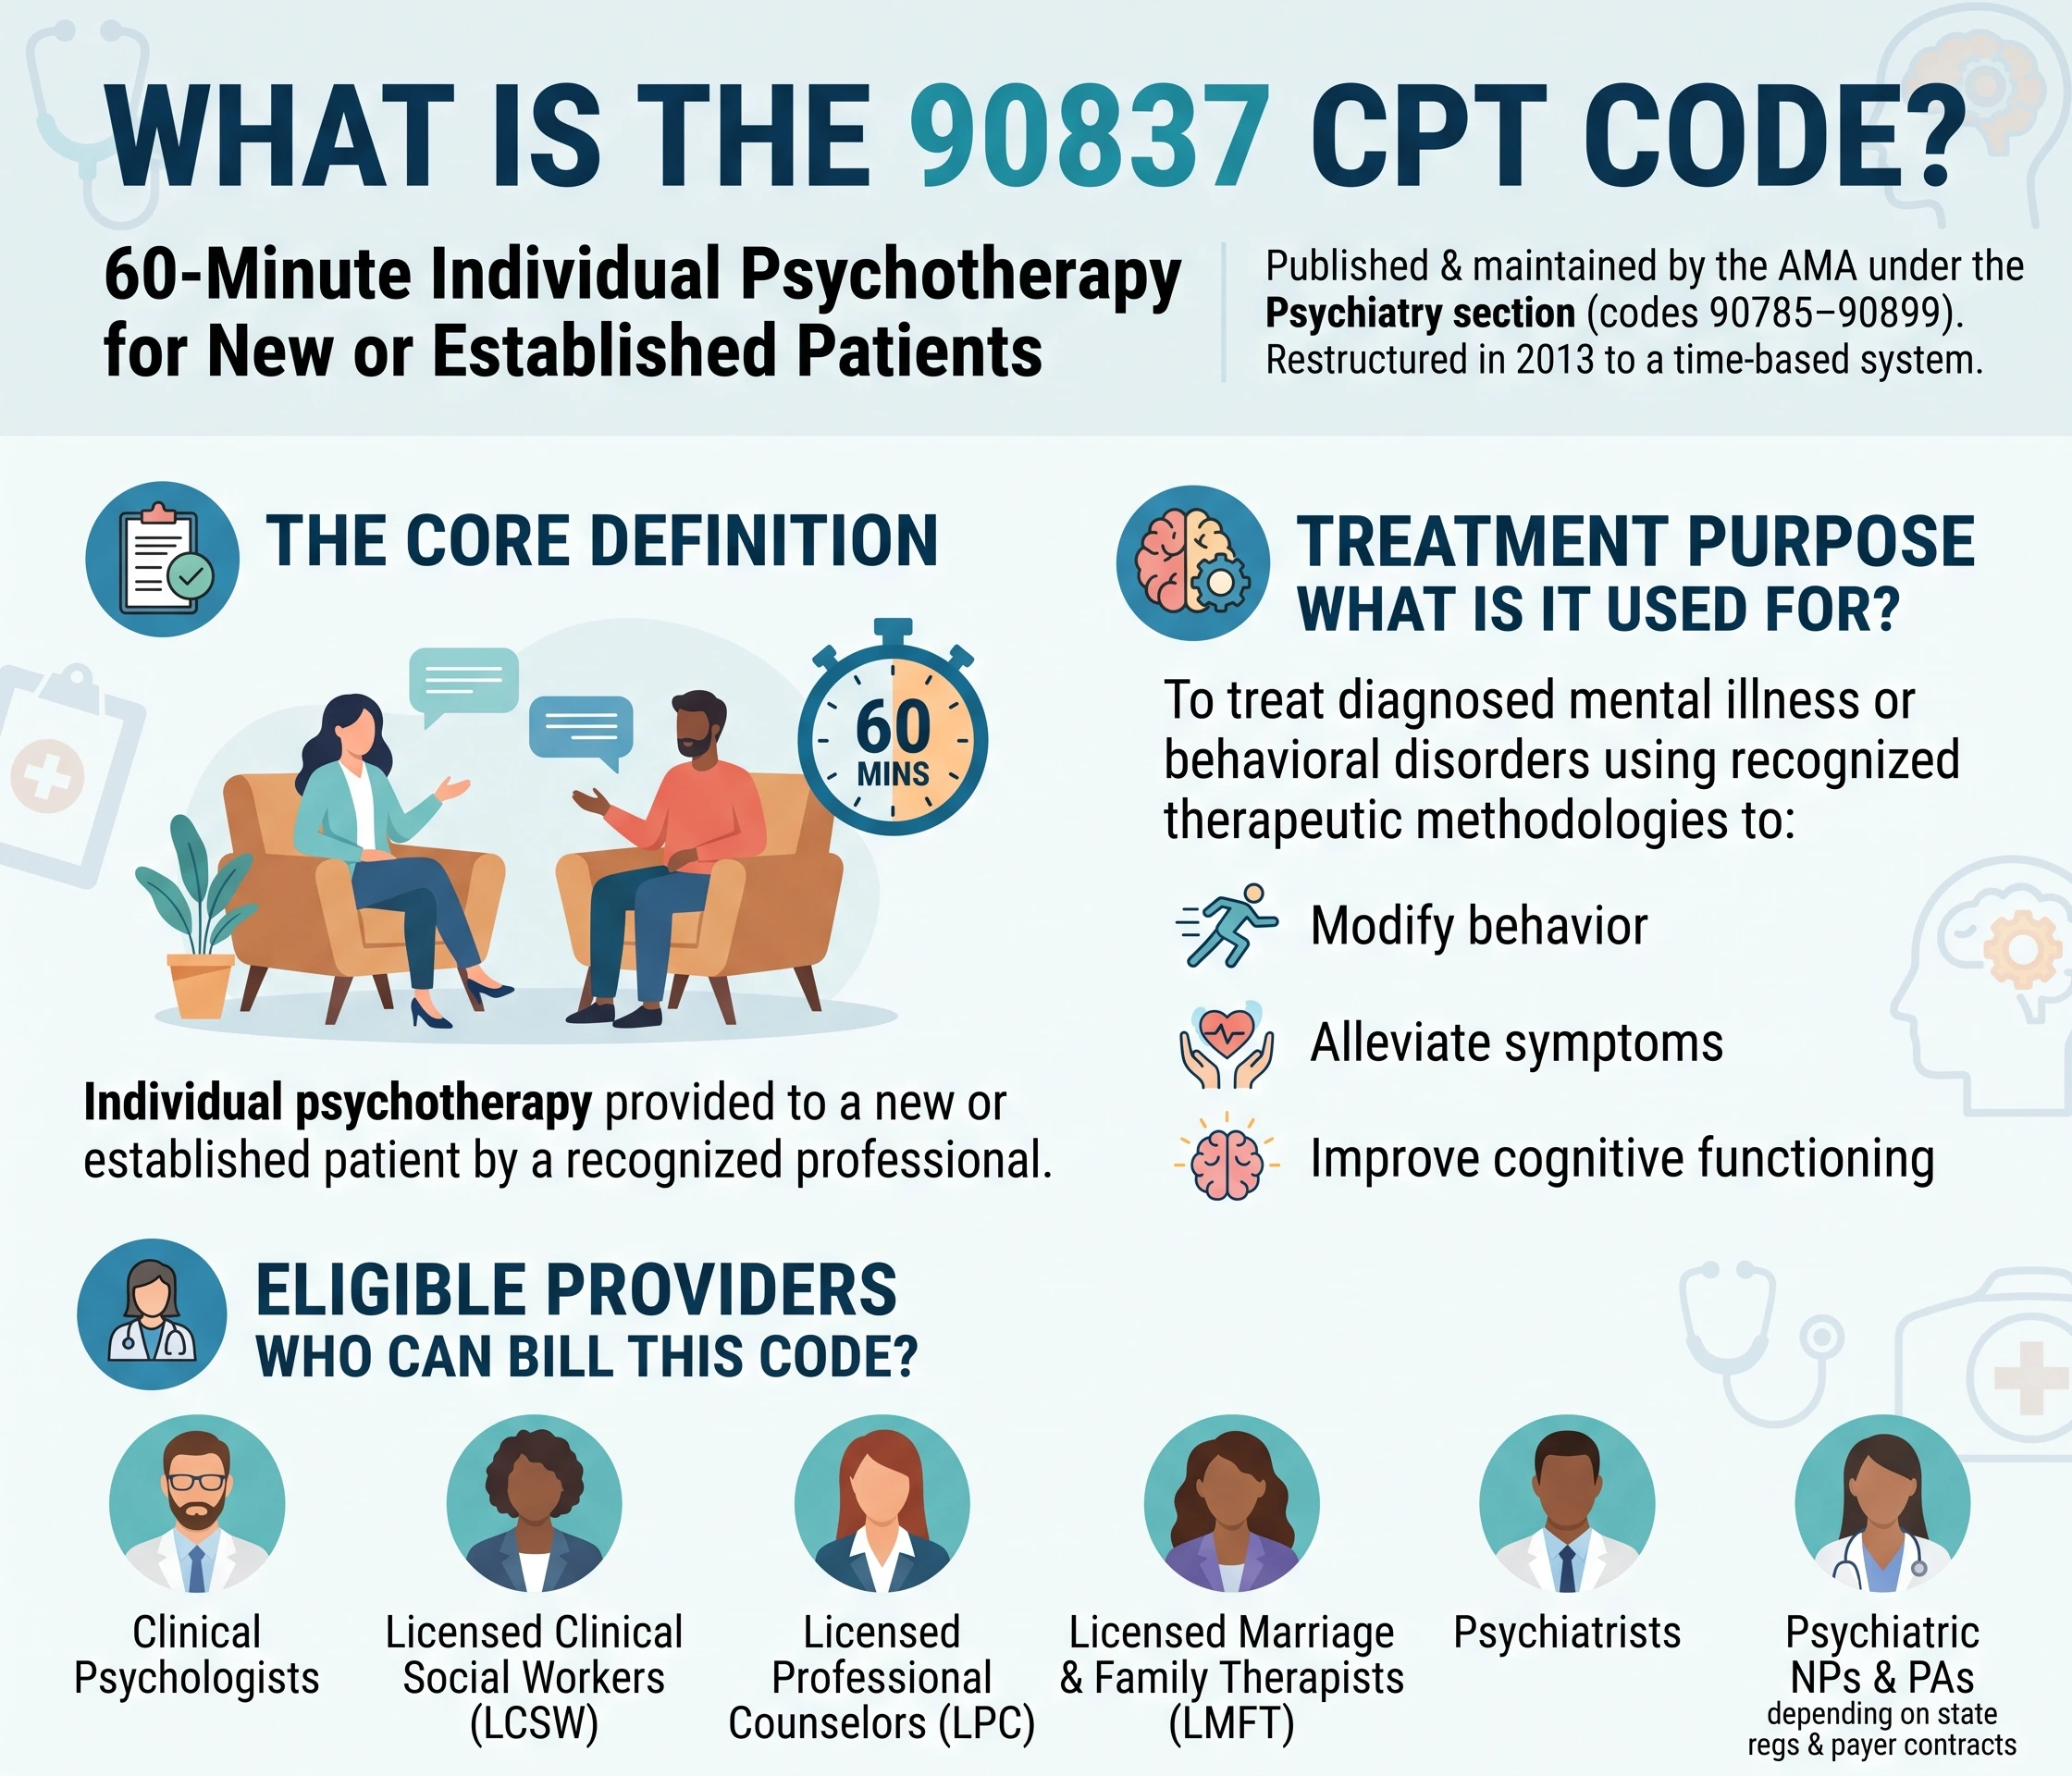
The AMA publishes and maintains the CPT code set. Within this manual, mental health services fall under the Psychiatry section (codes 90785 through 90899). The 90837 code specifically represents 60 minutes of individual psychotherapy provided to an established or new patient.
Therapists use this code when applying recognized therapeutic methodologies to treat a diagnosed mental illness or behavioral disorder. These interventions aim to modify behavior, alleviate symptoms, or improve the patient’s cognitive functioning.
The code applies to services provided by clinical psychologists, licensed clinical social workers, licensed professional counselors, licensed marriage and family therapists, and psychiatrists. Depending on state regulations and specific payer contracts, psychiatric nurse practitioners and physician assistants may also bill this code. The AMA completely restructured the psychotherapy codes in 2013, moving away from site-specific codes to the current time-based tiered system used today.
Time requirements for 90837
Psychotherapy codes are strictly time-based. The AMA specifies that the 90837 code targets a 60-minute session. The exact time spent with the patient, however, does not need to equal exactly 60 minutes to qualify for this billing category.
The CPT manual includes a specific time rule for psychotherapy services. A clinician can bill 90837 if the face-to-face time with the patient reaches at least 53 minutes. The upper limit for this code is generally considered 89 minutes. Sessions lasting longer than 90 minutes require prolonged services add-on codes.
If a session lasts 52 minutes or less, the provider cannot use 90837. They must downcode the session to the next appropriate time tier.
Billing personnel should note that time calculated for the 90837 code includes only the face-to-face therapeutic interaction with the patient or family members. It excludes administrative tasks. Time spent scheduling the next appointment, collecting copayments, or typing the clinical note after the patient leaves the office does not count toward the 53-minute minimum. If the patient leaves the room to use the restroom for five minutes, the clinician must subtract that time from the total face-to-face calculation.
Comparing 90837 to other psychotherapy codes
Selecting the correct code depends entirely on the duration of the clinical intervention. The AMA designates three primary codes for standard individual psychotherapy.
CPT Code | Target Time | Minimum Time Required | Maximum Time Allowed |
90832 | 30 minutes | 16 minutes | 37 minutes |
90834 | 45 minutes | 38 minutes | 52 minutes |
90837 | 60 minutes | 53 minutes | 89 minutes |
A standard therapy hour is typically scheduled for 60 minutes but actually involves 45 to 50 minutes of direct clinical care. In these standard scenarios, providers must bill 90834. The 90837 code is reserved for extended sessions where the direct therapeutic intervention exceeds the 52-minute threshold.
Documentation requirements for 90837
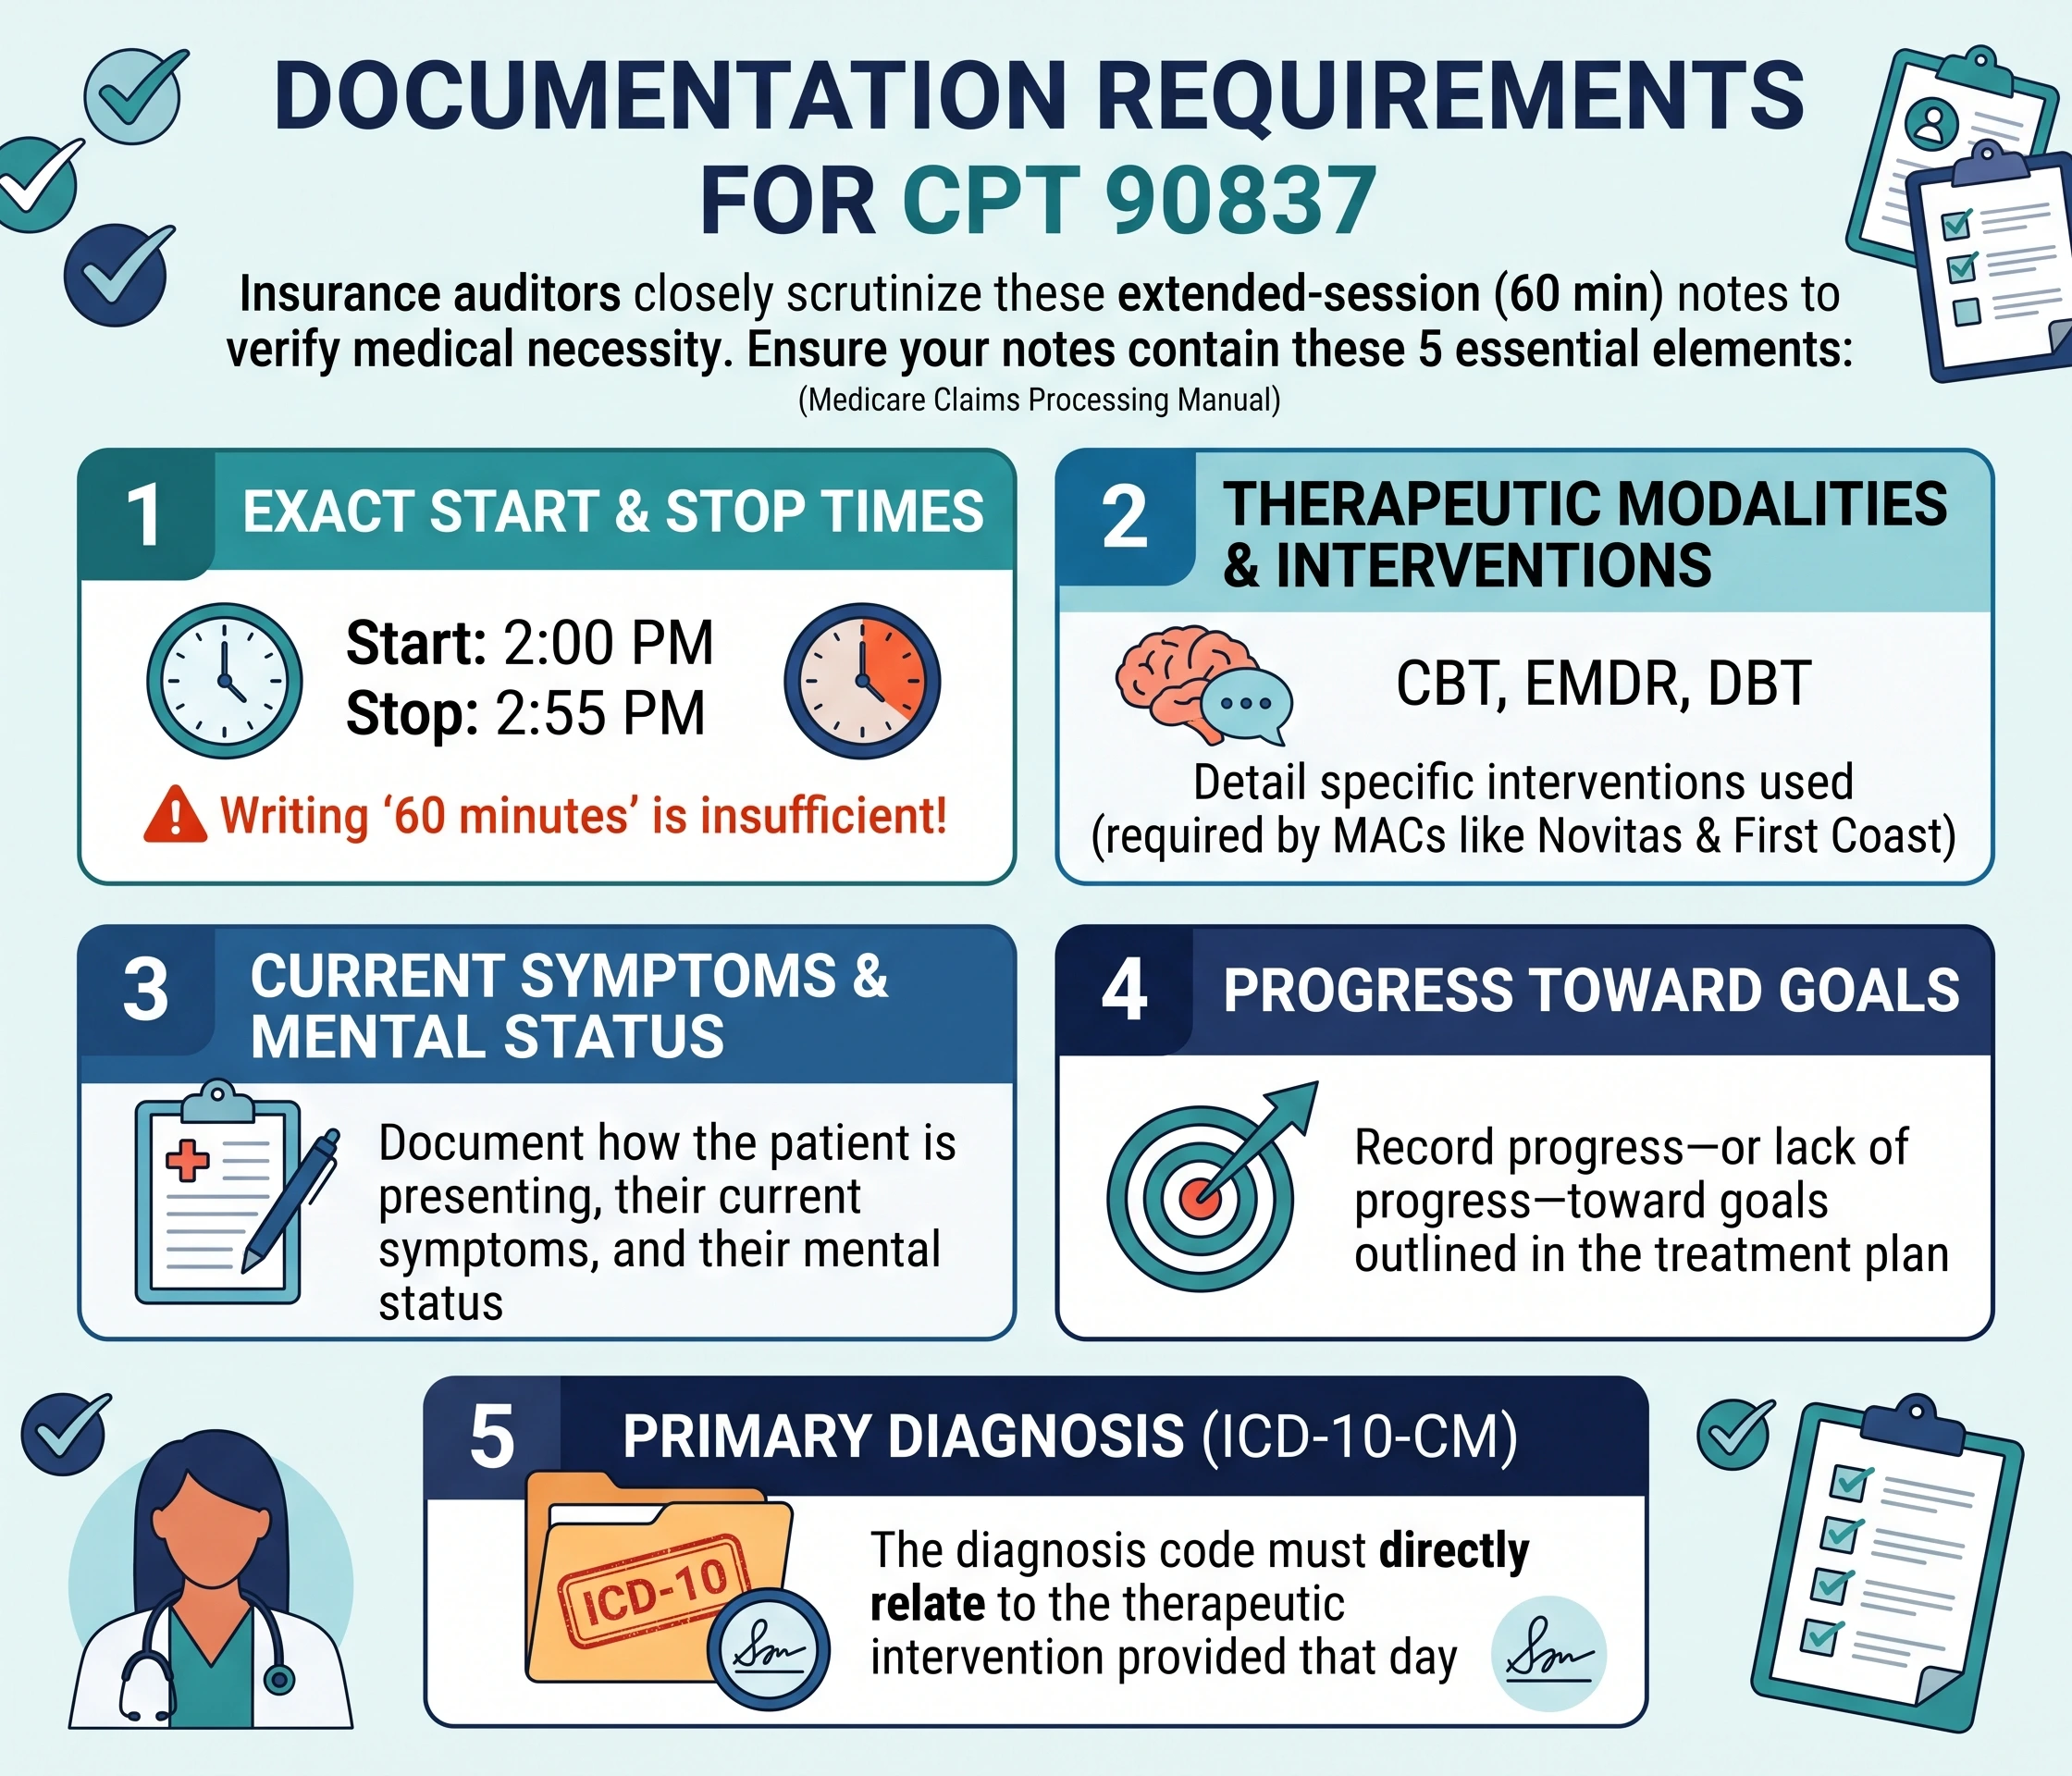
Insurance payers mandate specific elements within the clinical record to substantiate the billing of any behavioral health service. Because 90837 represents an extended session, auditors examine these notes closely to verify that the time spent was medically necessary.
According to the Medicare Claims Processing Manual (Chapter 12), a complete psychotherapy note must include several distinct pieces of information. The record must document the exact start and stop times of the session. Writing “60 minutes” is insufficient for most payers. The note should specify times, such as “Start: 2:00 PM, Stop: 2:55 PM.”
Medicare Administrative Contractors (MACs) such as Novitas Solutions and First Coast Service Options specify that the documentation must also list the therapeutic modalities and interventions utilized during the session. Examples include Cognitive Behavioral Therapy (CBT), Eye Movement Desensitization and Reprocessing (EMDR), or Dialectical Behavior Therapy (DBT).
The provider must record the patient’s current symptoms, mental status, and any progress or lack of progress toward the goals outlined in the original treatment plan. The primary diagnosis code (ICD-10-CM) must directly relate to the therapeutic intervention provided that day.
Establishing medical necessity for 60-minute sessions
Medical necessity dictates whether an insurance company will pay for a health care service. A payer will only reimburse the 90837 CPT code if the clinical documentation proves that a 60-minute session was clinically required to treat the patient’s condition.
Many private payers default to authorizing 45-minute sessions. Providers billing the 60-minute code frequently face pre-payment reviews or post-payment audits. To survive an audit, the clinical note must explain why a shorter session would have been inadequate.
Acceptable reasons for extended sessions vary by patient and diagnosis. High-risk patients presenting with severe symptoms, such as active suicidal ideation or acute panic attacks, require longer interventions for stabilization. Complex trauma processing protocols like EMDR naturally demand longer uninterrupted blocks of time to safely initiate and close a clinical sequence. The provider must explicitly state these clinical realities in the session note.
Using 90837 with evaluation and management codes
Psychiatrists and psychiatric nurse practitioners often provide both psychotherapy and medication management during the same encounter. The AMA designates separate codes to capture this combination of services.
When a provider performs an Evaluation and Management (E/M) service and individual psychotherapy during a single visit, they use an add-on code for the therapy portion. The E/M code (such as 99213 or 99214) serves as the primary procedure. The psychotherapy add-on code indicates the time spent on therapy independent of the medical management.
The add-on equivalent for a 60-minute psychotherapy session is 90838. A provider cannot bill 90837 concurrently with an E/M code. The documentation must clearly separate the time spent on the E/M components (like reviewing lab results or adjusting prescriptions) from the time spent on psychotherapy.
Adding interactive complexity (90785)
Certain clinical situations complicate the delivery of standard psychotherapy. The AMA created the interactive complexity add-on code (90785) to account for these challenges.
Providers can bill 90785 alongside 90837 when communication factors significantly complicate the delivery of care. According to CPT guidelines, this code applies in specific scenarios:
- The session requires the use of an interpreter or translator.
- The session involves the participation of third parties such as child welfare agencies or probation officers.
- The patient exhibits high reactivity, requiring the provider to use physical or play therapy interventions to manage acute behaviors.
- The patient lacks the ability to communicate directly due to cognitive impairment or severe developmental delays.
The clinical note must describe the exact communication barrier and how it impacted the delivery of the 60-minute therapy session.
Common modifiers applied to 90837
Modifiers are two-character codes appended to a primary CPT code. They provide payers with additional circumstances regarding the encounter without changing the definition of the primary service.
Telehealth services represent the most frequent reason to append a modifier to the 90837 code. Following the expansion of telehealth regulations, CMS and commercial payers require specific indicators when a session occurs via video or audio.
The 95 modifier indicates a synchronous telemedicine service rendered via a real-time interactive audio and video telecommunications system. Many commercial plans require this modifier for virtual therapy sessions.
The GT modifier previously served the same purpose and is still required by certain regional MACs or specific state Medicaid programs.
The 10 modifier is used by some payers to denote services provided via audio-only telecommunications. Coverage for audio-only psychotherapy varies widely by state and insurance plan. Billing staff must verify the specific modifier requirements of each patient’s insurance plan, as rules diverge significantly between Medicare, Medicaid, and commercial networks like Blue Cross Blue Shield or UnitedHealthcare.
Reasons for 90837 claim denials
Even with accurate time tracking, providers frequently experience claim denials when submitting the 90837 code. These rejections typically stem from specific administrative or clinical errors.
The primary reason for a 90837 denial is a failure to meet the 53-minute time threshold. If a payer requests records and the exact start and stop times are missing or total less than 53 minutes, they will deny the claim or demand a refund.
Frequency limits also trigger automatic rejections. Many commercial insurance policies limit patients to one psychotherapy session per day. If a provider bills a family therapy code (90847) and an individual psychotherapy code (90837) on the same date of service, the National Correct Coding Initiative (NCCI) edits will likely flag the second code as a duplicate or mutually exclusive service.
Authorization failures represent another common barrier. Some behavioral health carve-out networks require prior authorization for 60-minute sessions, even if 45-minute sessions are exempt from authorization requirements. If the provider fails to secure this authorization before the appointment, the payer will deny the claim and often hold the patient harmless, meaning the provider cannot bill the patient for the balance.
Audit risks and the Office of Inspector General
Federal agencies monitor billing patterns to identify potential Medicare fraud, waste, and abuse. The Department of Health and Human Services Office of Inspector General (OIG) periodically reviews the behavioral health sector.
The 90837 CPT code frequently attracts OIG scrutiny. Because the 60-minute code yields higher reimbursement than the 45-minute code, regulators watch for providers who bill 90837 exclusively. A billing pattern consisting entirely of 90837 claims flags a practice as an outlier compared to regional peers.
According to OIG Work Plan documents, auditors look for systematic overbilling. This occurs when a therapist routinely provides 45 minutes of face-to-face care but bills for 60 minutes. Practices protect themselves by conducting internal chart audits, ensuring all clinicians strictly adhere to the 53-minute minimum, and regularly using the 90834 code when sessions conclude early.
Accurate billing of the 90837 CPT code relies on precise time management and detailed clinical documentation. Providers must achieve a minimum of 53 minutes of face-to-face interaction to legally apply this code. The clinical note must record exact start and stop times, specify the therapeutic interventions used, and clearly demonstrate the medical necessity of an extended 60-minute session. By separating administrative time from clinical time and understanding specific payer policies regarding telehealth modifiers and prior authorizations, medical billers and healthcare providers can reduce claim denials and maintain compliance with federal billing standards.